NEET PG Coaching Archives - Page 2 of 8 -

Entropion: Causes, Symptoms, Diagnosis, and Treatment
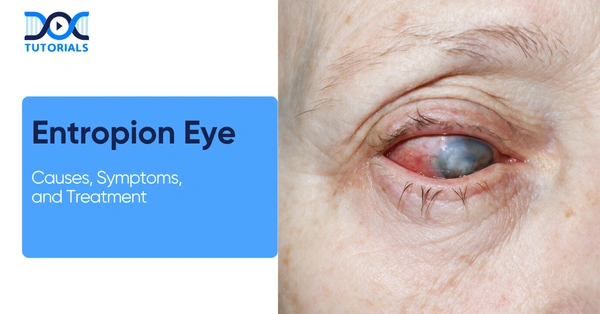
Entropion Eye

Entropion is an eye condition characterised by the abnormal inward turning of the eyelids, leading to friction with the skin. It is common among elderly patients with weak eyelid muscles and can also be caused by scarring, inflammatory reactions, eyelid muscle spasm, or congenital factors.

Failure to treat entropion may lead to corneal damage, infections, and poor vision. To avoid the above complication, it is necessary to recognise entropion early and provide adequate treatment. It is important to understand the symptoms and treatment options of entropion eye, which is crucial for NEET PG preparation. Keep reading to know more!

What is Entropion?

Entropion is the inversion of the lower lid margin, during which the eyelashes start to come into contact with the ocular surface, leading to irritation, watering, and pain. While most of the time, only the bottom eyelid is affected, the condition can appear in both eyes simultaneously.

Entropion is a condition in which the eyelid folds inwards towards the eyeball. This results in friction between the eyelid skin and eyelashes and the eyeball’s surface, causing pain and irritation of the cornea (the front part of the eyeball). It is different from ectropion, wherein the eyelid folds inwards.

Entropion typically affects the lower eyelid and can be unilateral (one-sided) or bilateral (both sides). Patients suffer from redness, tearing, grittiness, and irritation. Even though the symptoms might be mild at first, they will continue to progress until the patient gets treatment.

What are the Types of Entropion?

There are 4 types of entropion, each with distinct causes, symptoms, and possible complications. These include cicatricial, spastic, involutional, and congenital entropion. Identifying the correct type of disorder allows specialists to choose the appropriate treatment method to achieve positive outcomes for a patient.

Depending on the causes of entropion eye, there are 4 major types:

1. Congenital Entropion

Congenital entropion is a relatively uncommon condition that affects infants and young children. It is caused by the failure of the eyelid muscles to develop properly, resulting in entropion.

It commonly affects the lower eyelid. The symptoms may include watering, redness, and constant eye rubbing. In some cases, it becomes apparent only when the affected person squints. Sometimes the issue resolves itself, but when the child is suffering from progressive entropion, the surgical procedure is needed.

2. Involutional Entropion

Involutional entropion is the most frequent case of this disease. This type of entropion occurs when the muscles of the eyelids weaken as people age. As a result, the eyelid rolls inwards.

Patients experience irritation, tearing, redness, and a gritty sensation in the eye. During the early stages, patients experience periodic entropion that can be alleviated by the use of lubricating drops, but eventually needs to be corrected surgically.

3. Cicatricial Entropion

It is the type of entropion where eyelids are rolled inward due to the formation of scar tissue in the conjunctiva area. In some cases, it affects the upper or lower eyelids and can be induced by trauma, infections, inflammation, or surgery.

Treatment options for cicatricial entropion include surgical removal of scars or eyelid reconstruction, treatment of underlying causes, and prevention.

4. Spastic Entropion

Spastic entropion occurs due to muscle spasm around the eye caused by irritation, dryness, or inflammation of the eye area. Spastic entropion is prevalent among older patients because of weaker muscles supporting the eyelids.

The severity of the symptoms varies depending on the severity of the spasm. Usually, the removal of irritation helps patients to overcome this issue, but sometimes it requires more invasive treatment.

What are the Causes of Entropion?

Entropion occurs when the normal anatomy of the eyelids is altered, affecting how the eyelids function. Most often, this condition results from age-related muscle weakness; however, there are many other causes, including scarring, infections, inflammation, or congenital abnormalities.

Entropion may result from any of the following causes:

  • Weak Eye Muscles: Ageing weakens the muscles around the eyes while stretching the tendons. This is the most frequent cause of entropion.
  • Scar Tissue: Scarred tissues on the eyelid due to chemical burns, injury, or surgery cause irregularity on the eyelid surface.
  • Eye Infection: Trachoma, an eye infection, is prevalent in developing countries across Africa, Asia, Latin America, the Middle East, and the Pacific Islands and is another identified cause of entropion. It also causes eyelid scarring, entropion, and blindness.
  • Inflammatory Reaction: Eye irritation from dryness and inflammation may cause the urge to rub or squeeze the eyelids together for relief. Such action can cause eyelid muscle spasms and inward-turning of the eyelid margins against the cornea.
  • Genetic Problem: Congenital entropion, which has been present since birth, occurs due to an additional eyelid fold causing inward eyelashes.

What are the Risk Factors of Entropion?

Multiple risk factors might contribute to the development of entropion. Ageing is the most common cause, while environmental conditions that expose people to excessive dust and smoke may also cause eye discomfort.

There are certain conditions that can make one prone to entropion, especially when they affect the structure of the eyelids, their muscle strength, or the eyes. Here are the common risk factors of entropion eye:

  • Age: Age is one of the conditions that could make one suffer from entropion because, as one gets older, there would be weakness in the muscles surrounding the eyelid.
  • Gender: Women are said to be at risk of suffering from entropion more than men due to their anatomy.
  • Exposure to Environmental Conditions: When one lives in environments that contain dust, wind, and pollutants, their eyes could become irritated.
  • Health Condition: Some medical conditions include Bell’s palsy, infection, or eye surgery, which can increase one’s risk of suffering from entropion.

What are the Symptoms of Entropion?

Common symptoms of entropion include irritation of the affected eye(s), redness, tearing, sensitivity to light, and a gritty sensation in the eye, usually accompanied by tearing. If left untreated, symptoms may become severe and include eye pain, vision changes, swelling, and discharge.

Signs and symptoms of Entropion may be mild or severe initially and include:

  • Irritation: Sensation of irritation in your eyes all the time in your eyes.
  • Redness: Your eye may be red and swollen due to irritation caused by lashes rubbing on your cornea.
  • Tears: Excess tearing due to irritation.
  • Sensitivity to Light:  Photophobia, or sensitivity to light, may occur.
  • Visual Effects: Visual problems may arise when irritation is severe.

Some symptoms are more serious due to a prolonged condition and require prompt medical care. These are:

  • Pain: Intense eye pain despite taking pain medication.
  • Vision Problems: Sudden vision problems or loss of vision.
  • Swelling: Rapidly increasing redness and swelling.
  • Discharge: Unusual secretion or discharge from the eyes.

What is the Diagnosis of Entropion?

The diagnosis of entropion is made by a thorough eye examination by a specialist. Although it is easy to identify entropion during an eye exam in clear cases, intermittent cases may require additional tests. The most commonly used examinations include the snap-back test, eyelid distraction test, orbicularis override test, and eyelid digital eversion test.

Diagnosis of entropion involves careful examination of the eye. Abnormal eyelid margin positioning can be seen in some cases, whereas intermittent entropion requires more careful inspection, as it does not occur at rest.

Tests used to examine and establish the diagnosis include the following:

  • Snap Back Test: This test assesses the eyelid’s ability to return to its original position when pulled downward.
  • Eyelid Distraction Test: This tests the looseness of the eyelid by pulling it out from its usual position.
  • Orbicularis Override Test: This test assesses eyelid position during a forceful blink, revealing muscle override of the eyelid.
  • Digital Eversion Test: This test assesses eyelid stability and identifies different types of entropion, such as cicatricial or involutional.

The table below shows the findings of the severity type of entropion, guiding appropriate treatment decisions:

TestNegative (Normal)MildModerateSevere / Positive
Snap-back TestEyelid returns quickly (<2 sec) to normal position.Returns slowly (>2 sec) before blink.Returns only after blink.Does not return even after blinking.
Eyelid Distraction TestThe eyelid can be pulled only 2–3 mm from the globe.Eyelid can be pulled ≥7 mm (laxity).
Orbicularis Override TestNormal alignment, even with forced blink.Lid margin turns inward on forced blink.
Digital Eversion TestNormal alignment at rest and on pulling.Entropion at rest, normal on gentle pull (involutional).Entropion persists when pulled (cicatricial).

What is the Treatment for Entropion?

The treatment of entropion is intended to relieve irritation and correct the abnormal placement of the eyelid. The type of approach to the problem should depend on the severity of the condition and the reasons for its development.

Treatment approaches for entropion focus on minimising irritation and fixing the inverted eyelid. This depends on factors such as the severity of the condition, the underlying cause, and whether it is temporary or permanent.

Non-surgical methods include temporary options or mild cases:

  • Eye Lubrication with Drops and Ointments: This keeps the eyes moisturised and minimises irritation from friction between the eyelids and the eyes. However, these cannot fix eyelid inversion.
  • Contact Lenses: Special contact lenses can serve as an external barrier to protect the cornea from irritation caused by lashes.
  • Use of Skin Adhesive: The eyelid is held in place by adhesive skin tape to ensure it moves outwards. This method is temporary and mostly used as a stopgap measure before definitive treatment.
  • Temporary Suturing: The eyelid is surgically stitched into a more favourable position. The stitches can also lead to scarring that maintains the position of the eyelid outside the eyeball for a few months.
  • Botox Treatment: This involves injecting small amounts of Botox into the muscles pulling the eyelid inward. This temporarily reduces the effect of these muscles.
  • Eyelash Removal (Epilation): This option entails the removal of misdirected eyelashes that irritate the cornea. They tend to regrow in their former positions.

Although non-surgical options can alleviate the symptoms, surgery is necessary for permanent correction. Surgical methods are performed under local anaesthesia with sedation, and patients can return home on the same day.

  • Tarsal Strip (Lateral Tarsal Strip Surgery): In this procedure, the eyelid is shortened and tightened.
  • Reinsertion of Retractors: It aims to strengthen the muscles involved in eyelid movement.
  • Debulking of Orbicularis Oculi: This weakens the muscle pulling the eyelid inward.
  • Eyelid Reconstruction: This is recommended in cases of traumatic damage or disease. Techniques like electrocautery or cryosurgery are used to permanently change lash direction.

What are the Complications of Entropion?

Untreated cases of entropion may result in serious consequences, such as worsening of symptoms, eye problems that are difficult to cure, or loss of vision. In this case, frequent friction of the eyelashes leads to corneal scratches and subsequent infection and corneal scarring, thus causing further difficulties and complications.

Entropion can cause serious eye damage over time due to persistent friction between the eyelashes and the cornea. Several complications can arise:

  • Corneal Scratches: The constant rubbing against the cornea causes scratch marks on the eye that can cause eye pain, light sensitivity, and loss of vision.
  • Eye Infections: The continual irritation makes the eyes vulnerable to infections by bacteria that can damage the eye.
  • Scarring: Persistent irritation can scar the cornea or eyelids, which can affect vision and complicate treatment.

What are the Prevention Strategies for Entropion?

Although not all cases of entropion are preventable, implementing eye care techniques can help reduce risk and preserve overall eye health. Thus, protecting your eyes from irritants, maintaining proper eyelid hygiene, following a balanced diet, and attending your eye appointments regularly will be crucial to avoiding complications.

Even though entropion is not fully preventable, some precautions will help in minimising its occurrence and maintaining eye wellness:

  • Eye Protection: Use sunglasses or goggles in dusty, windy, and polluted surroundings to avoid irritating and damaging your eyes.
  • Proper Eye Care: Cleanliness of the eyelids and maintenance of a clean surrounding of the eyes will prevent eye infections and inflammations.
  • Nutritious Diet: Eating a nutritious diet that contains vitamins and antioxidants ensures optimal eye wellness and healthy tissue.
  • Routine Eye Checkups: Periodic eye checks will ensure the early diagnosis of eyelid alterations, thus preventing complications.

Practising these simple measures will help you prevent entropion.

FAQs about Entropion

1. What is entropion of the eye?

Entropion is an ocular condition in which the eyelid folds itself inside, resulting in the eyelashes and skin rubbing on the surface of the eye. This leads to irritation, redness, watering, and pain. Over time, entropion can damage the cornea and affect a person’s vision.

2. What causes entropion?

Entropion occurs as a result of ageing and associated weakening of the eyelid muscles. It may also develop because of scars, infections, inflammation, muscle spasm, and congenital problems in rare cases.

3. Is entropion a serious condition?

Yes, this ocular condition can become quite severe if it is not treated appropriately. Friction may lead to the formation of abrasions, make the patient more prone to infections, and result in vision loss in certain cases.

4. What are the first symptoms of entropion?

First symptoms that might occur in the case of entropion are redness, watering, irritation, a feeling of grittiness or a foreign body presence, light sensitivity, and blurry vision, should the latter happen due to damage to the cornea.

5. Will the health condition of entropion go away without treatment?

Yes, entropion may go away spontaneously in certain cases, including mild ones associated with irritation or occurring in children. However, it is usually better to treat this problem with surgery since other solutions may bring only temporary relief.

6. How is entropion diagnosed?

The diagnosis of this condition requires performing a complete eye examination during which eyelid movement and eyelid laxity will be assessed, and a slit lamp test will be conducted.

7. What is the best treatment option for entropion?

Surgery remains the best treatment option since it is able to solve the problem on a fundamental level, unlike taping, injection of a chemical into the eyelid, or the application of eye drops.

8. Are eye drops capable of curing this entropion condition?

No, this ocular condition cannot be cured by using eye drops. In fact, these medications only help to relieve irritating symptoms by lubricating the eye.

9. Is entropion surgery dangerous?

No, this procedure is rather safe and common. The doctor uses local anaesthesia, which does not take too much time, and the patient recovers rapidly after it.

10. How to avoid the entropion eye condition?

To prevent the development of entropion, one should protect their eyes from dust and windy weather, maintain proper hygiene of the eyelid area, avoid infections, and have their eyes regularly checked.

Conclusion

The entropion eye may seem progressive, but with proper diagnosis and management, it can be treated effectively. The first step is to identify the symptoms and determine the underlying cause. Once the causative factor is identified, selecting the right treatment, whether non-surgical or surgical, can effectively prevent future complications.

For NEET-PG aspirants and students who wish to learn about entropion in depth for their board exams, DocTutorials can be your study partner in this journey.

We offer crisp videos, clinical Qbank, exam-focused notes, flashcards, and mind maps to ensure aspirants are well prepared and gain complete clarity on complex NEET PG concepts. Join DocTutorials today and explore our NEET PG course to excel in your medical career!

NEET PG Online Live Power Pack
DocTutorials App Download Now

Latest Blogs

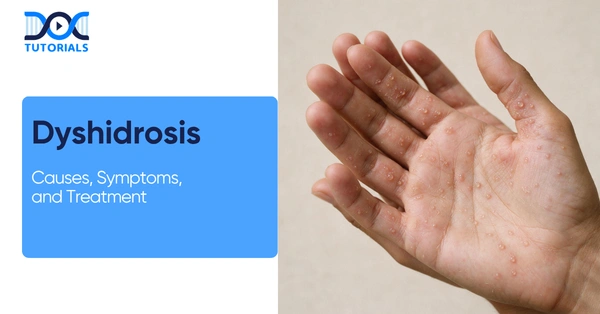
Dyshidrosis: Symptoms, Treatment, and Prevention

Dyshidrosis Causes, Symptoms, and Treatment

Dyshidrosis is a recurrent skin condition that can cause uncomfortable flare-ups affecting the hands and feet, often interfering with daily activities. This condition is generally caused by factors such as stress, environmental triggers, and individual susceptibility.

Among individuals with hand eczema, 5% to 20% have dyshidrotic eczema, underscoring its clinical importance. For medical students, particularly in Dermatology and Venereology, understanding the causes, symptoms, and management of dyshidrosis is crucial for both exams and clinical practice. Keep reading to know more.

What is Dyshidrosis?

Dyshidrotic eczema (pompholyx) is a skin condition that causes intensely itchy, small, fluid-filled blisters on the fingers, palms, and feet. When these blisters dry, the skin often becomes flaky, cracked, and uncomfortable.

Dyshidrotic eczema, also known as dyshidrosis or pompholyx, is a condition in which the affected person develops itchy blisters and scaly skin. The condition typically develops on the webbed parts of the fingers, palms, and feet.

Blisters caused by this skin condition appear to be tiny beads filled with fluid. They range from 1 to 2 millimetres across, approximately the diameter of a pinhead. In some cases, the blisters may merge together to create one big blister. Once the blisters dry up, the affected skin becomes flaky and cracked.

What are the Clinical Features of Dyshidrotic Eczema?

Dyshidrotic eczema presents with itchy, fluid-filled blisters on the sides of the palms and soles, appearing symmetrically and with minimal redness. They typically heal over 2–3 weeks with peeling and may occur alongside other types of hand dermatitis.

Dyshidrotic eczema (pompholyx) is a long-term skin condition that is characterised by small, fluid-filled blisters (vesicles) located on the edges of the palms and soles of the feet. These vesicles are small, round in shape, and are generally symmetrical.

They do not have associated redness, and do not exist on any other parts of the body. The following are the clinical features of dyshidrosis:

  • The vesicles are usually very itchy.
  • Vesicles usually heal within two to three weeks following a peeling stage.
  • Vesicles can also occur with other forms of hand dermatitis.

What are the Causes of Dyshidrosis?

The main cause of dyshidrosis is unknown, but it is likely due to a mix of genetic and environmental factors. Common triggers include allergens, fungal infections, sweating or humidity, seasonal changes, and stress.

The exact cause of dyshidrotic eczema is not yet known. Although scientific evidences propose that genetics and the environment are likely to be the common cause of this skin condition.

It is not infectious, which means you cannot catch dyshidrotic eczema from another person, nor can it be transmitted by touch. These are some of the potential dyshidrotic eczema triggers, including but not limited to:

  • Exposure to Allergens/Irritants: Substances in your surroundings, such as nickel, personal care products, and certain foods, can be allergens or irritants.
  • Fungal Infections: One common example of a fungal infection that can trigger the condition is athlete’s foot, which can cause dyshidrosis of the feet.
  • Humidity: The excessive presence of moisture in the skin caused by constant washing of hands or prolonged use of gloves at work, sweaty feet and hands, and highly humid conditions can cause dyshidrosis flare-ups.
  • Changes in the Seasons: Warmer temperatures and seasonal allergies can worsen dyshidrotic eczema symptoms, while colder temperatures can alleviate them.
  • Stress: Physical and psychological stress are known to worsen symptoms of dyshidrotic eczema significantly.

What are the Risk Factors of Dyshidrosis?

Dyshidrosis can affect anyone, but it is more common in people with sensitive skin, high stress, or existing eczema. People with frequent exposure to metals such as nickel or cobalt also increase their risk.

Dyshidrotic eczema can affect anyone, although it is most common in the following:

  • People with Sensitive Skin

If you have sensitive skin, you are at increased risk of getting dyshidrotic eczema. More specifically, if you get a rash on your skin, the risk of that rash developing into dyshidrotic eczema is high.

  • People who Experience High Stress

When you experience any kind of physical or emotional stress, the probability of developing dyshidrotic eczema increases. If you tend to get stressed easily, this means that you’re vulnerable to dyshidrotic eczema.

  • Exposure to Metal

The chances of developing dyshidrotic eczema become high if you work in an industrial environment, where exposure to metals such as nickel or cobalt is common.

  • People with Atopic Dermatitis

Atopic dermatitis (also known as eczema) is an itchy, inflamed skin condition. This means that if you’re already suffering from atopic dermatitis, you have an increased risk of developing dyshidrotic eczema.

What are the Signs and Symptoms of Dyshidrosis?

Symptoms of dyshidrosis include small itchy blisters on the hands, along with pain, peeling, dryness, and cracking as they heal. Sometimes, larger blisters can form, but the condition usually remains limited to the hands.

Having dyshidrotic eczema means that your symptoms appear and disappear over time, but can last for a long period, like several weeks. The typical dyshidrosis symptoms are usually produced on the skin:

  • Small, firm blisters on hands
  • Pain or soreness
  • Itching
  • Peeling or scaling
  • Changes in color
  • Extra sweating
  • Dryness and cracking (after blisters go away)

Some of the rare but most serious symptoms associated with dyshidrotic eczema are large blisters that may develop on the back of the fingers and hands. However, there is no risk of having any blisters develop on any other part of the body.

What is the Diagnosis of Dyshidrosis?

Diagnosis of dyshidrosis involves a doctor examining the skin and reviewing your medical history to find out possible triggers. Tests such as allergy tests, fungal tests, or skin sampling may be performed to rule out other conditions and confirm the diagnosis.

In order for this disease to be diagnosed properly, a dermatologist consultation is crucial, as its symptoms may appear similar to other skin conditions like fungal infection, contact dermatitis, and psoriasis.

Diagnosing dyshidrosis involves the following methods:

  • Physical Exam: The doctor examines the skin on the affected like hands and feet, to check the density and appearance of the blisters, including their size.
  • Medical History: To find out the triggers of these blisters, the doctor may ask about the patient’s medical history to gather information about their past allergies, lifestyle choices, stress levels, and their environment.

The following tests for diagnosing dyshidrosis help determine the actual cause of the symptoms and develop an accurate treatment plan:

  • Allergy Test: This test detects sensitivity to allergens such as nickel, cobalt, fragrances, preservatives, and detergents. These findings help the patients to adjust themselves according to their surroundings to prevent flare-ups of dyshidrosis in the future.
  • Fungal Culture: In this test, a small skin sample is obtained and examined in the laboratory to assess the possibility of fungal infections, such as hand fungus or athlete’s foot, that may resemble dyshidrotic eczema.
  • Patch Test: In a patch test, a specific chemical is applied to small skin samples to detect possible triggers of eczema. Based on the patch test, a doctor can prescribe an appropriate treatment to avoid future flare-ups.
  • Skin Scraping/Biopsy: In some cases, the doctor performs this procedure to determine whether the condition is dyshidrosis or some other skin infections like tinea, psoriasis, or autoimmune disorders.

What are the Treatment Options for Dyshidrosis?

Treatment of dyshidrosis depends on severity and may include creams, medicines, or therapies to reduce itching and heal blisters. In some cases, phototherapy, antihistamines, or injections may be used to improve control.

After considering the symptoms and the seriousness of dyshidrotic eczema, your doctor will provide the right treatment option for you. There are various treatments available for dyshidrotic eczema, and they include:

  • Corticosteroids

The application of corticosteroid cream and ointment may be effective in reducing the visibility of blisters. After applying the corticosteroid cream, the affected area should be covered with plastic wrap or a clean, compressed cloth to speed up the healing process. Oral corticosteroids may be prescribed in cases of severe dyshidrotic eczema.

  • Immune Suppressant Ointment

When patients prefer a reduction in steroid use, immunosuppressants can be recommended by the doctor. The medication contains pimecrolimus and tacrolimus, which help in the healing of blisters.

  • Phototherapy

As an alternative, phototherapy can be recommended if other methods do not respond to treatment. This technique involves combining medication with ultraviolet (UV) rays.

  • Botulinum Toxin Injections

The treatment of severe cases of dyshidrotic eczema involves botulinum toxin injections.

  • Antihistamines

In mild cases of dyshidrotic eczema, antihistamines may also be prescribed by your doctor.

What are the Complications of Dyshidrosis?

Untreated dyshidrosis can lead to skin infections, thickened or cracked skin, and ongoing pain or discomfort. It can affect daily activities and cause nail changes and emotional stress due to its appearance and symptoms.

When the condition is left untreated or becomes a frequent cause of flare-ups, several complications may arise, affecting both the physical and psychological well-being of an individual. Frequent flare-ups of the condition typically impair the skin’s natural barrier, making one prone to irritation, infection, and sensitivity.

Additionally, the condition may impair the performance of everyday tasks such as typing, bathing, or walking, depending on whether it affects hands or feet. Possible complications of dyshidrosis include:

  • Development of secondary infections (most likely Staphylococcus aureus), thickening, and fissure formation due to chronic inflammation, as well as psychological discomfort from the appearance of lesions and pain associated with the condition.
  • Thickening of the skin and/or cracks due to frequent drying and blistering, followed by healing of the skin.
  • Chronic pain or discomfort, especially during flare-ups and periods of open lesions.
  • Nail abnormalities such as ridges, pitting, or thickening are due to the extension of eczema into the area beneath the nails.
  • Psychological discomfort and anxiety as a result of the appearance of blisters or itching.

What are the Prevention Strategies for Dyshidrosis?

Managing dyshidrosis focuses on habits like gentle skin care, regular moisturising, and avoiding over-washing. Staying away from triggers, protecting your hands, and keeping stress under control can help prevent flare-ups.

Despite having various methods of treating dyshidrotic eczema, there is no definitive treatment for the disease. The following lifestyle changes and practices can assist you in controlling your symptoms and stopping flare-ups:

  • Keep your Skin Clean and Moisturised

Cleanse and dry your hands and feet carefully, and apply moisturiser (emollient) regularly and each time after washing your hands.

  • Wash Your Hands Properly

Before washing your hands, take off your rings and other pieces of jewellery that may deposit soap and water over your skin, which will lead to irritation.

Wash your hands in warm rather than hot water without soap, to prevent dryness of the skin. Avoid washing your hands too often because excessive hand washing can irritate the skin as well.

  • Find Out Your Triggers and Avoid Them

Coming into contact with irritants and allergens directly leads to flare-ups. Avoid touching such substances and use gloves to prevent their contact.

  • Protect Your Hands by Wearing Gloves

Wear cotton gloves under waterproof gloves while doing laundry and protective gloves when cooking, gardening, cleaning, or when it is cold outdoors.

  • Control Your Stress Levels

Emotional stress is one of the most common factors that cause flare-ups. Engage yourself in activities like exercise, meditation, and breathing exercises, and opt for therapy consultations if required.

FAQs about Dyshidrosis

1. What is dyshidrosis?

It is a recurring skin disorder characterised by small blisters filled with fluid that affect the palm surface and the sides of the finger pads. They are usually very itchy and develop further into peeling or cracking of the affected areas.

2. What causes dyshidrosis?

Although no particular cause is evident, the triggers of dyshidrosis are assumed to be multifactorial. Emotional stress, allergic reactions (specifically to metals such as nickel and cobalt), hyperhidrosis, and irritants such as soap, detergents, and chemicals are among the common causes.

3. Who is susceptible to dyshidrosis?

People who have atopic dermatitis, allergies, or hypersensitive skin have a higher chance of having this disease. The presence of hyperhidrosis, exposure to frequent moisture, and a stressful environment can also contribute to developing this condition.

4. Is dyshidrosis contagious?

No, dyshidrosis is not an infectious skin ailment that transmits from person to person through physical contact, sharing of personal things, and exposure to an infected area.

5. What are the usual signs of dyshidrosis?

The typical symptom of dyshidrosis is a severe itching or burning sensation of the palms, which is later followed by vesicles. The development of small blisters may eventually form scales or peel off the skin. There could be painful fissures of the skin in some cases.

6. How do doctors diagnose dyshidrosis?

Diagnosing dyshidrosis is primarily based on visual identification and the history of patients’ experiences. When uncertainty occurs, patch testing for possible allergens or biopsy examination for ruling out fungal infection is performed.

7. How should dyshidrosis be treated?

Topical corticosteroids are commonly applied to the affected area to prevent inflammation and swelling. Emollients are used for restoring the integrity of the skin.

Antihistamines relieve itching. Other treatments may involve systemic drugs, phototherapy, and immunosuppressant medications.

8. Can dyshidrosis disappear spontaneously?

Yes, mild cases can naturally disappear in a few weeks. However, this skin condition is a recurring problem, so if left untreated, it can easily relapse.

9. How can dyshidrosis be prevented?

Avoiding triggers and irritants, keeping the affected area moist while maintaining the skin clean and dry, wearing gloves, and eliminating stressful situations are some preventive measures that can prevent dyshidrosis from occurring.

10. What are the complications of dyshidrosis?

Untreated dyshidrosis can cause a secondary infection caused by bacteria because of skin breakdown. Lichenification or thickening of the skin can occur, and chronic irritation or discomfort may develop.

Conclusion

Dyshidrotic eczema is a chronic but manageable skin condition that can be effectively controlled when diagnosed at an early stage, together with an appropriate treatment option. NEET-PG requires candidates to know everything related to dyshidrosis. For added guidance, DocTutorials can be your study partner.

We offer crisp videos, clinical Qbank, exam-focused notes, flashcards, and mindmaps to ensure aspirants are well-prepared and gain complete clarity over complex NEET PG concepts.

Join DocTutorials today and explore our NEET PG course to excel in your medical career!

NEET PG Online Live Power Pack
DocTutorials App Download Now

Latest Blogs

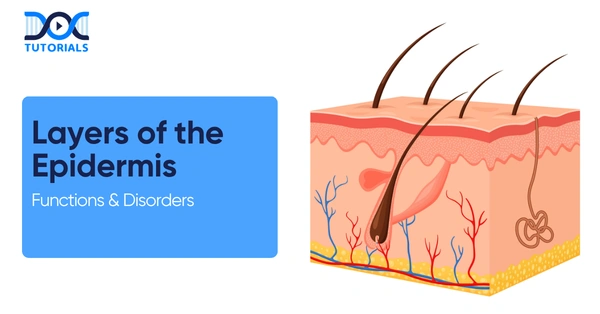
Layers of the Epidermis: Structure, Functions, and Disorders

layers of the Epidermis

Meningitis is the swelling of the membranes (meninges) that surround the brain and the spinal cord. It is a severe disorder which may develop quickly and has to be treated immediately. It can be triggered by different organisms (bacteria, viruses, fungi, parasites) or noninfectious factors (drugs, autoimmune processes).

Acute bacterial meningitis is life-threatening, but viral meningitis is typically mild. Treatment involves a rapid diagnosis (physical examination and CSF culture) and appropriate therapy (antibiotics, antivirals, steroids). This guide addresses the aetiology and pathophysiology of meningitis relevant to NEET-PG aspirants. Keep reading to know more.

What is the Pathophysiology of Meningitis?

Meningitis is characterised by the inflammation of the subarachnoid space. Bacterial infection causes a neutrophil-rich exudate, leading to brain oedema, raised intracranial pressure, and tissue damage. Viral meningitis presents a mild lymphocytic inflammation. Cases that are not treated can cause infarction, herniation or hydrocephalus.

In bacterial meningitis, the pathogens penetrate the meninges via the bloodstream or by direct spread. They multiply in the CSF, leading to a neutrophilic reaction with purulent exudates and oedema. This causes increased intracranial pressure and disorders such as infarction, herniation and subsequent hydrocephalus.

Viral meningitis is less severe and is characterised by lymphocytic inflammation. It leads to cytokine release and mild neuronal irritation, and minimal or no pus. The course is typically subacute, with good recovery, but some viruses, such as Herpes Simplex Virus (HSV), can lead to meningoencephalitis and require specific treatment.

Fungal meningitis and tuberculosis progress gradually. Cryptococcus is prevalent in immunocompromised individuals, and tuberculosis leads to basal exudates, vasculitis, and other complications such as hydrocephalus. CSF is usually characterised by elevated leukocytes, elevated protein, and low glucose.

What are the Causes of Meningitis?

There are various causes of meningitis. Types of infections are bacterial, viral, fungal, parasitic, and tubercular. Noninfectious causes include drugs, autoimmune disorders, and cancer. Identifying the cause is key to proper treatment and prevention.

Meningitis is caused by a broad spectrum of infectious and non-infectious agents, which may vary in severity, progression, and management. The cause of meningitis varies according to region and age.

Major causes include bacterial, viral, fungal, tubercular, parasitic, and non-infectious causes, each with its own clinical and pathological characteristics. Here are the causes of meningitis:

  • Bacterial Meningitis (Acute and Life-threatening): Streptococcus pneumoniae is the most prevalent, although Neisseria meningitidis is a source of outbreaks in the youth. Vaccination has reduced Hib cases.

Listeria affects all newborns, the older generation, and those with frail immune systems, whereas Group Bacillus, Streptococcus, and Escherichia coli are prevalent among newborns. Other bacteria (such as Staphylococcus aureus and Pseudomonas) can occur after injury or surgery.

  • Viral (Aseptic) Meningitis: Mainly caused by enteroviruses. HSV (particularly HSV-2) may lead to recurrent disease. Other causes include varicella-zoster, mumps, measles, HIV, and arboviruses. Usually milder with a lymphocytic response.
  • Fungal Meningitis: Uncommon in healthy people. Cryptococcus neoformans thrives most among immunodeficient patients. Others (Histoplasma, Coccidioides, Candida) cause chronic or subacute meningitis with high protein and lymphocytes.
  • Tubercular Meningitis: As a result of Mycobacterium tuberculosis. Slow onset with basal exudates, granulomas, and infarcts. CSF shows lymphocytes, very low glucose, and high protein. Common in India; needs specific therapy.
  • Parasitic and Other Causes: Parasites (e.g. Angiostrongylus, Gnathostoma) cause eosinophilic meningitis. Naegleria fowleri causes an acute, fatal infection. Others (cysticercosis, malaria) may involve the meninges. The non- infectious causes are malignancy, autoimmune disease, drugs and sarcoidosis.

Risk Factors of Meningitis

Poor housing hygiene increases the risk of meningococcal meningitis (a bacterial infection transmitted through respiratory droplets). Risk is increased by a lack of vaccination (pneumococcal, Hib, meningococcal). Immunosuppression (HIV, chemotherapy, and splenectomy) predisposes to many forms.

Ear/sinus infections, skull fractures or neurosurgery can directly introduce bacteria into the meninges. Infants inherit risk through maternal infection (GBS, E. coli). Pregnancy predisposes to Listeria.

What are the Symptoms and Signs of Meningitis?

Meningitis is usually characterised by fever, neck stiffness and headache. Other aspects are the altered mental status, photophobia, nausea/vomiting and rash. Infants might exhibit non-specific symptoms (irritability, bulging fontanelle). 

Meningitis results in a mixture of systemic and neurological manifestations. Symptoms can build up very quickly in acute cases, but can be mild or slow in some populations, such as infants or those with chronic infections.

Typical signs and red flags must be identified early to enable prompt diagnosis and treatment:

  • Patients typically experience rapid-onset fever and severe headache.
  • Neck stiffness (nuchal rigidity) is the typical feature: patients have difficulty flexing the neck.
  • Photophobia (sensitivity to light) is frequent.
  • Meningeal irritation also causes positive Kernig’s sign (pain on extending the knee when the hip is flexed) and Brudzinski’s sign (hip/knee flexion when the neck is flexed).
  • In addition to meningitis, neurological symptoms present can be confusion, drowsiness, or coma when encephalitis is present. In the severe cases, there may be seizures.
  • A typical rash (petechial or purpuric) indicates Neisseria meningitidis.
  • Headache and photophobia are prominent in adults.
  • In children and infants, presentation is more variable: children may reject feeds, become fussy or sleepy, develop a bulging fontanelle, or cry inconsolably.
  • Fever may even be absent in neonates. Among the red flags are a sudden increase in fever, an intense headache, neck soreness, and a change in consciousness. (“Classic triad: fever, headache, neck stiffness)

Systemic signs include:

  • Tachycardia
  • Hypotension
  • Septic meningitis may be accompanied by shock.

Rapid progression, rash, and Disseminated Intravascular Coagulation (DIC) are observed in meningococcemia. Chronic or tubercular meningitis can have a subacute onset with progressive confusion, cranial nerve palsies (Most IV nerve inducing vision in both eyes), and hydrocephalus (nausea/vomiting due to increased ICP).

What is the Diagnosis of Meningitis?

Diagnosis is based on clinical features and lab tests. Suspected cases should be urgently tested by history, exam, and lumbar puncture (CSF analysis), the gold standard. Treatment should not be withheld in possible cases of bacterial meningitis.

Suspected meningitis presents with fever and signs of meningitis (stiff neck, photophobia, altered mentation). Imaging and lumbar puncture are a part of the evaluation.

In cases of focal deficits, seizures, or changes in consciousness, a CT/MRI (computed tomography/magnetic resonance imaging) scan must be performed initially to exclude increased intracranial pressure or mass lesions.

  • Lumbar Puncture (LP)

Take CSF of cell count, chemistry (protein, glucose), Gram stain, and culture. Other tests can include PCR of viruses (enterovirus, HSV), Tuberculosis Polymerase Chain Reaction (TB PCR) or acid-fast stain (in the event of suspicion of TB), and fungal antigen (cryptococcal) in immunocompromised patients.

Laboratories will then perform specific tests with CSF or blood to identify the organism. An overview of typical CSF results is as follows:

CSF ParameterBacterial MeningitisViral MeningitisTubercular Meningitis
WBC (cells/µL)100–10,000 (mostly neutrophils)<100 (mostly lymphocytes)<100 (lymphocytes 50–1000)
Neutrophils (%)Predominant (>50%)It may seem (particularly early)Predominant early (50–1000 total)
Protein>1.0 g/L0.4–1.0 g/L1.0–5.0 g/L
Glucose (ratio CSF: serum)<0.4Normal (>0.6)<0.3
Lactate (mmol/L)>2.0 (often >4.0)<2.0>2.0
Gram stain/CultureFrequently positive for bacteria.Negative (PCR for viruses)May be negative (AFB stain, culture can take weeks)

Additional tests include:

  • Blood cultures must be taken. 
  • Brain imaging (CT/MRI) can demonstrate meningeal enhancement or exclude an abscess.

Other supportive tests:

  • Complete blood count (typically presents with leukocytosis), 
  • Inflammatory markers (CRP, procalcitonin),
  • Serum chemistry (to measure dehydration, organ functionality).

Polymerase chain reaction (PCR) tests (e.g. BioFire panel) can quickly detect bacterial and viral DNA (deoxyribonucleic acid) in CSF. Nonetheless, empirical therapy should not be delayed due to PCR results.

What is the Treatment for Meningitis?

The course of treatment is based on the cause. Bacterial meningitis is a medical emergency: administer high-dose IV antibiotics and usually IV corticosteroids. Viral meningitis is largely supportive; antivirals are administered in cases of suspected herpes. Fungal meningitis is treated using suitable antifungals. In every case, supportive care is essential.

Meningitis management necessitates cause-specific urgent treatment and supportive care to minimise mortality and complications. Since delays—especially in bacterial meningitis—can be life-threatening, therapy is often started empirically based on clinical suspicion and patient factors such as age and immune status.

After the underlying cause is diagnosed, treatment is customised accordingly, with efforts to reduce inflammation, prevent complications, and support essential functions. The treatment depends on the aetiology, but in any case, the main focus is to prevent complications and minimise mortality.

  • Bacterial Meningitis: Needs broad-spectrum IV antibiotics immediately, regardless of test results, depending on age and risk factors.

The therapy is then streamlined based on culture and sensitivity reports. Close contacts of Meningococcal cases require chemoprophylaxis.

  • Role of Steroids: Corticosteroids are also administered as an adjunct to minimise inflammation and neurological destruction, especially in bacterial or tubercular meningitis. They are best initiated at an early age.
  • Viral Meningitis: Usually mild and self-limiting. The treatment is primarily supportive, and antivirals are only used in certain infections,s such as herpes viruses.
  • Tubercular Meningitis: Managed with prolonged multi-drug anti-tubercular therapy along with steroids. It is vital to initiate early treatment to avoid long-term complications.
  • Fungal Meningitis: Needs long-term antifungal treatment, usually in stages (induction and maintenance). Immunocompromised people have a more intensive management.
  • Supportive and Adjunctive Care: Involves fluid and oxygen therapies, and surveillance for seizures and complications, such as elevated intracranial pressure or hydrocephalus. In some cases, surgical operations might be necessary.

Here is a table for key treatment modalities:

Type of MeningitisImmediate ManagementDefinitive / Targeted Therapy
BacterialUrgent empiric IV antibiotics (ceftriaxone/cefotaxime + vancomycin +/- ampicillin), administer dexamethasone, fluids, and observe closely.
Adjust antibiotics in accordance with culture susceptibility (e.g. penicillin, ceftriaxone, ampicillin).Time depends on the organism (7-21 days). The close contact chemoprophylaxis in meningococcal cases.
ViralSupportive care: hydration, antipyretics, observation; hospitalise for severe and uncertain diagnosis.Antivirals only if indicated (e.g. acyclovir for HSV/VZV). The majority of cases do not require special treatment.
TubercularEarly anti-TB therapy initiation using corticosteroids; treatment of elevated ICP and complications.
Long-term ATT regimen (HRZE → HR for 12 months). Steroids were maintained during the first weeks to minimise complications.
FungalBegin antifungal treatment immediately; control intracranial pressure (e.g. repeated LPs when necessary).Amphotericin B + flucytosine as induction and fluconazole as maintenance. Long-term treatment according to immune status.
Parasitic / OtherSupportive care and stabilisation; prompt diagnosis of the underlying cause.Antiparasitic drugs, when available (e.g. miltefosine), steroids in inflammatory forms, and underlying disease (autoimmune, malignancy, etc.).

What are the Major Complications of Meningitis?

Meningitis can lead to serious, sometimes permanent complications such as hearing loss, seizures, memory and concentration problems, limb amputations (after severe sepsis), and even death. Bacterial meningitis carries the highest risk, with up to 1 in 5 survivors experiencing long-term effects.

Here are some of the key complications of meningitis based on neurological, physical and systemic classification:

Neurological Complications

  • Hearing Loss (Partial or Total): One of the most common long-term effects.
  • Vision Loss: Damage to the optic nerves or brain pathways.
  • Seizures (Epilepsy): Recurrent episodes due to brain irritation.
  • Cognitive Problems: Memory loss, poor concentration, and learning difficulties.
  • Movement and Balance Issues: Coordination problems, muscle weakness.
  • Behavioural Changes: Personality shifts, emotional instability, or developmental delays in children.

Physical Complications

  • Limb Loss/Amputation: Especially in meningococcal meningitis, where sepsis damages tissues.
  • Bone and Joint Problems: Arthritis or chronic pain due to infection spreading.
  • Kidney Damage: From septicemia or complications of treatment.

Systemic Complications

  • Sepsis: Widespread infection in the bloodstream, often fatal if untreated.
  • Increased Intracranial Pressure: Swelling of the brain leading to coma or death.
  • Hydrocephalus: Buildup of cerebrospinal fluid in the brain.
  • Blood Vessel Damage: Stroke or reduced blood supply to parts of the brain.

What is the Prevention for Meningitis?

Prevention is crucial, especially when there are complications of meningitis. The most important measures are vaccination (Hib, pneumococcal, meningococcal), prophylactic antibiotics among close contacts, and good hygiene. Avoid sharing drinks, cover coughs, and ensure proper sanitation. To minimise the risk of listeria, pregnant women must avoid unpasteurised foods.

The prevention of meningitis aims to minimise exposure to infectious agents and enhance immunity, particularly against vaccine-preventable pathogens.

The combination of immunisation, timely prophylaxis, hygiene measures, and lifestyle measures is important in reducing the risk of infection and managing outbreaks.

  • Vaccination: Hib and Streptococcus pneumoniae conjugate vaccines are commonly administered to children. At-risk groups are vaccinated against Neisseria meningitidis. These greatly reduce the incidence of bacterial meningitis.
  • Antibiotic Prophylaxis: Antibiotics (rifampin, ciprofloxacin, or ceftriaxone) should be administered to close contacts of meningococcal cases. Unvaccinated people may need prophylaxis with Hib exposure; this is not standard with pneumococcus.
  • General Hygiene: Handwashing, using separate utensils/drinks, covering coughs, and maintaining space will reduce the transmission. Masks or avoiding crowds may be advised during outbreaks.
  • Safe Food Practices: To prevent listeria, avoid unpasteurised dairy and cook meats properly, particularly in pregnant or immunocompromised people.
  • Vector Control: Prevention of some viral meningitides (arboviruses) may occur through avoidance of mosquito/tick bites, i.e., the use of insect repellent and protective clothing.

FAQs about Meningitis

  1. How quickly can meningitis become dangerous?

Bacterial meningitis may deteriorate in a matter of hours and cause serious complications or death. It is important to have early medical attention.

  1. Can meningitis spread from person to person?

Some types, particularly meningococcal meningitis, are transmitted via respiratory droplets (coughing, sneezing, close contact).

  1. Who is at the highest risk of meningitis?

People at risk are infants, elderly people, immunocompromised patients, and those who live in crowded environments.

  1. Can meningitis occur without fever?

Yes, particularly in neonates, elderly patients or immunocompromised patients where the symptoms can be atypical.

  1. Why is a lumbar puncture important in meningitis?

Lumbar puncture in meningitis assists in the diagnosis and determining the exact cause through analysis of cerebrospinal fluid.

  1. Can meningitis cause long-term disability?

Yes, survivors can have complications such as hearing loss, learning disabilities or neurological impairments.

  1. Is meningitis always contagious?

No, not every form is contagious, fungal, tubercular, or non-infectious; they do not normally pass on between individuals.

  1. What is the role of imaging in meningitis?

In some cases, CT or MRI is performed before lumbar puncture to eliminate elevated intracranial pressure or brain lesions.

  1. Can meningitis recur?

Yes, meningitis can also possibly have recurrent episodes, particularly with some viral infections or immune defects.

  1. Why is early treatment started before confirmation?

Delays in treatment, particularly in bacterial meningitis, may lead to high mortality and morbidity.

Conclusion

Meningitis is a severe disorder that entails inflammation of the meninges and has diverse etiologies. Bacterial forms result in neutrophilic exudates, and viral forms present lymphocytic inflammation. It is important to identify the symptoms early and analyse the CSF as soon as possible. Early intervention and therapy are life-saving.

For NEET-PG students, a clear understanding of the pathology and management of meningitis is crucial not only for exam preparation but also for future clinical practice. For additional guidance, DocTutorials can be your study companion. We offer crisp videos, clinical Qbank, exam-focused notes, flashcards, and mind maps. This helps ensure aspirants gain complete clarity over complex medical topics.

Join DocTutorials today and explore our NEET PG course to excel in your medical career!

NEET PG Online Live Power Pack
DocTutorials App Download Now

Latest Blogs

Meningitis: Causes, Symptoms, Diagnosis, and Treatment

Meningitis

Meningitis is the swelling of the membranes (meninges) that surround the brain and the spinal cord. It is a severe disorder which may develop quickly and has to be treated immediately. It can be triggered by different organisms (bacteria, viruses, fungi, parasites) or noninfectious factors (drugs, autoimmune processes).

Acute bacterial meningitis is life-threatening, but viral meningitis is typically mild. Treatment involves a rapid diagnosis (physical examination and CSF culture) and appropriate therapy (antibiotics, antivirals, steroids). This guide addresses the aetiology and pathophysiology of meningitis relevant to NEET-PG aspirants. Keep reading to know more.

What is the Pathophysiology of Meningitis?

Meningitis is characterised by the inflammation of the subarachnoid space. Bacterial infection causes a neutrophil-rich exudate, leading to brain oedema, raised intracranial pressure, and tissue damage. Viral meningitis presents a mild lymphocytic inflammation. Cases that are not treated can cause infarction, herniation or hydrocephalus.

In bacterial meningitis, the pathogens penetrate the meninges via the bloodstream or by direct spread. They multiply in the CSF, leading to a neutrophilic reaction with purulent exudates and oedema. This causes increased intracranial pressure and disorders such as infarction, herniation and subsequent hydrocephalus.

Viral meningitis is less severe and is characterised by lymphocytic inflammation. It leads to cytokine release and mild neuronal irritation, and minimal or no pus. The course is typically subacute, with good recovery, but some viruses, such as Herpes Simplex Virus (HSV), can lead to meningoencephalitis and require specific treatment.

Fungal meningitis and tuberculosis progress gradually. Cryptococcus is prevalent in immunocompromised individuals, and tuberculosis leads to basal exudates, vasculitis, and other complications such as hydrocephalus. CSF is usually characterised by elevated leukocytes, elevated protein, and low glucose.

What are the Causes of Meningitis?

There are various causes of meningitis. Types of infections are bacterial, viral, fungal, parasitic, and tubercular. Noninfectious causes include drugs, autoimmune disorders, and cancer. Identifying the cause is key to proper treatment and prevention.

Meningitis is caused by a broad spectrum of infectious and non-infectious agents, which may vary in severity, progression, and management. The cause of meningitis varies according to region and age.

Major causes include bacterial, viral, fungal, tubercular, parasitic, and non-infectious causes, each with its own clinical and pathological characteristics. Here are the causes of meningitis:

  • Bacterial Meningitis (Acute and Life-threatening): Streptococcus pneumoniae is the most prevalent, although Neisseria meningitidis is a source of outbreaks in the youth. Vaccination has reduced Hib cases.

Listeria affects all newborns, the older generation, and those with frail immune systems, whereas Group Bacillus, Streptococcus, and Escherichia coli are prevalent among newborns. Other bacteria (such as Staphylococcus aureus and Pseudomonas) can occur after injury or surgery.

  • Viral (Aseptic) Meningitis: Mainly caused by enteroviruses. HSV (particularly HSV-2) may lead to recurrent disease. Other causes include varicella-zoster, mumps, measles, HIV, and arboviruses. Usually milder with a lymphocytic response.
  • Fungal Meningitis: Uncommon in healthy people. Cryptococcus neoformans thrives most among immunodeficient patients. Others (Histoplasma, Coccidioides, Candida) cause chronic or subacute meningitis with high protein and lymphocytes.
  • Tubercular Meningitis: As a result of Mycobacterium tuberculosis. Slow onset with basal exudates, granulomas, and infarcts. CSF shows lymphocytes, very low glucose, and high protein. Common in India; needs specific therapy.
  • Parasitic and Other Causes: Parasites (e.g. Angiostrongylus, Gnathostoma) cause eosinophilic meningitis. Naegleria fowleri causes an acute, fatal infection. Others (cysticercosis, malaria) may involve the meninges. The non- infectious causes are malignancy, autoimmune disease, drugs and sarcoidosis.

Risk Factors of Meningitis

Poor housing hygiene increases the risk of meningococcal meningitis (a bacterial infection transmitted through respiratory droplets). Risk is increased by a lack of vaccination (pneumococcal, Hib, meningococcal). Immunosuppression (HIV, chemotherapy, and splenectomy) predisposes to many forms.

Ear/sinus infections, skull fractures or neurosurgery can directly introduce bacteria into the meninges. Infants inherit risk through maternal infection (GBS, E. coli). Pregnancy predisposes to Listeria.

What are the Symptoms and Signs of Meningitis?

Meningitis is usually characterised by fever, neck stiffness and headache. Other aspects are the altered mental status, photophobia, nausea/vomiting and rash. Infants might exhibit non-specific symptoms (irritability, bulging fontanelle). 

Meningitis results in a mixture of systemic and neurological manifestations. Symptoms can build up very quickly in acute cases, but can be mild or slow in some populations, such as infants or those with chronic infections.

Typical signs and red flags must be identified early to enable prompt diagnosis and treatment:

  • Patients typically experience rapid-onset fever and severe headache.
  • Neck stiffness (nuchal rigidity) is the typical feature: patients have difficulty flexing the neck.
  • Photophobia (sensitivity to light) is frequent.
  • Meningeal irritation also causes positive Kernig’s sign (pain on extending the knee when the hip is flexed) and Brudzinski’s sign (hip/knee flexion when the neck is flexed).
  • In addition to meningitis, neurological symptoms present can be confusion, drowsiness, or coma when encephalitis is present. In the severe cases, there may be seizures.
  • A typical rash (petechial or purpuric) indicates Neisseria meningitidis.
  • Headache and photophobia are prominent in adults.
  • In children and infants, presentation is more variable: children may reject feeds, become fussy or sleepy, develop a bulging fontanelle, or cry inconsolably.
  • Fever may even be absent in neonates. Among the red flags are a sudden increase in fever, an intense headache, neck soreness, and a change in consciousness. (“Classic triad: fever, headache, neck stiffness)

Systemic signs include:

  • Tachycardia
  • Hypotension
  • Septic meningitis may be accompanied by shock.

Rapid progression, rash, and Disseminated Intravascular Coagulation (DIC) are observed in meningococcemia. Chronic or tubercular meningitis can have a subacute onset with progressive confusion, cranial nerve palsies (Most IV nerve inducing vision in both eyes), and hydrocephalus (nausea/vomiting due to increased ICP).

What is the Diagnosis of Meningitis?

Diagnosis is based on clinical features and lab tests. Suspected cases should be urgently tested by history, exam, and lumbar puncture (CSF analysis), the gold standard. Treatment should not be withheld in possible cases of bacterial meningitis.

Suspected meningitis presents with fever and signs of meningitis (stiff neck, photophobia, altered mentation). Imaging and lumbar puncture are a part of the evaluation.

In cases of focal deficits, seizures, or changes in consciousness, a CT/MRI (computed tomography/magnetic resonance imaging) scan must be performed initially to exclude increased intracranial pressure or mass lesions.

  • Lumbar Puncture (LP)

Take CSF of cell count, chemistry (protein, glucose), Gram stain, and culture. Other tests can include PCR of viruses (enterovirus, HSV), Tuberculosis Polymerase Chain Reaction (TB PCR) or acid-fast stain (in the event of suspicion of TB), and fungal antigen (cryptococcal) in immunocompromised patients.

Laboratories will then perform specific tests with CSF or blood to identify the organism. An overview of typical CSF results is as follows:

CSF ParameterBacterial MeningitisViral MeningitisTubercular Meningitis
WBC (cells/µL)100–10,000 (mostly neutrophils)<100 (mostly lymphocytes)<100 (lymphocytes 50–1000)
Neutrophils (%)Predominant (>50%)It may seem (particularly early)Predominant early (50–1000 total)
Protein>1.0 g/L0.4–1.0 g/L1.0–5.0 g/L
Glucose (ratio CSF: serum)<0.4Normal (>0.6)<0.3
Lactate (mmol/L)>2.0 (often >4.0)<2.0>2.0
Gram stain/CultureFrequently positive for bacteria.Negative (PCR for viruses)May be negative (AFB stain, culture can take weeks)

Additional tests include:

  • Blood cultures must be taken. 
  • Brain imaging (CT/MRI) can demonstrate meningeal enhancement or exclude an abscess.

Other supportive tests:

  • Complete blood count (typically presents with leukocytosis), 
  • Inflammatory markers (CRP, procalcitonin),
  • Serum chemistry (to measure dehydration, organ functionality).

Polymerase chain reaction (PCR) tests (e.g. BioFire panel) can quickly detect bacterial and viral DNA (deoxyribonucleic acid) in CSF. Nonetheless, empirical therapy should not be delayed due to PCR results.

What is the Treatment for Meningitis?

The course of treatment is based on the cause. Bacterial meningitis is a medical emergency: administer high-dose IV antibiotics and usually IV corticosteroids. Viral meningitis is largely supportive; antivirals are administered in cases of suspected herpes. Fungal meningitis is treated using suitable antifungals. In every case, supportive care is essential.

Meningitis management necessitates cause-specific urgent treatment and supportive care to minimise mortality and complications. Since delays—especially in bacterial meningitis—can be life-threatening, therapy is often started empirically based on clinical suspicion and patient factors such as age and immune status.

After the underlying cause is diagnosed, treatment is customised accordingly, with efforts to reduce inflammation, prevent complications, and support essential functions. The treatment depends on the aetiology, but in any case, the main focus is to prevent complications and minimise mortality.

  • Bacterial Meningitis: Needs broad-spectrum IV antibiotics immediately, regardless of test results, depending on age and risk factors.

The therapy is then streamlined based on culture and sensitivity reports. Close contacts of Meningococcal cases require chemoprophylaxis.

  • Role of Steroids: Corticosteroids are also administered as an adjunct to minimise inflammation and neurological destruction, especially in bacterial or tubercular meningitis. They are best initiated at an early age.
  • Viral Meningitis: Usually mild and self-limiting. The treatment is primarily supportive, and antivirals are only used in certain infections,s such as herpes viruses.
  • Tubercular Meningitis: Managed with prolonged multi-drug anti-tubercular therapy along with steroids. It is vital to initiate early treatment to avoid long-term complications.
  • Fungal Meningitis: Needs long-term antifungal treatment, usually in stages (induction and maintenance). Immunocompromised people have a more intensive management.
  • Supportive and Adjunctive Care: Involves fluid and oxygen therapies, and surveillance for seizures and complications, such as elevated intracranial pressure or hydrocephalus. In some cases, surgical operations might be necessary.

Here is a table for key treatment modalities:

Type of MeningitisImmediate ManagementDefinitive / Targeted Therapy
BacterialUrgent empiric IV antibiotics (ceftriaxone/cefotaxime + vancomycin +/- ampicillin), administer dexamethasone, fluids, and observe closely.
Adjust antibiotics in accordance with culture susceptibility (e.g. penicillin, ceftriaxone, ampicillin).Time depends on the organism (7-21 days). The close contact chemoprophylaxis in meningococcal cases.
ViralSupportive care: hydration, antipyretics, observation; hospitalise for severe and uncertain diagnosis.Antivirals only if indicated (e.g. acyclovir for HSV/VZV). The majority of cases do not require special treatment.
TubercularEarly anti-TB therapy initiation using corticosteroids; treatment of elevated ICP and complications.
Long-term ATT regimen (HRZE → HR for 12 months). Steroids were maintained during the first weeks to minimise complications.
FungalBegin antifungal treatment immediately; control intracranial pressure (e.g. repeated LPs when necessary).Amphotericin B + flucytosine as induction and fluconazole as maintenance. Long-term treatment according to immune status.
Parasitic / OtherSupportive care and stabilisation; prompt diagnosis of the underlying cause.Antiparasitic drugs, when available (e.g. miltefosine), steroids in inflammatory forms, and underlying disease (autoimmune, malignancy, etc.).

What are the Major Complications of Meningitis?

Meningitis can lead to serious, sometimes permanent complications such as hearing loss, seizures, memory and concentration problems, limb amputations (after severe sepsis), and even death. Bacterial meningitis carries the highest risk, with up to 1 in 5 survivors experiencing long-term effects.

Here are some of the key complications of meningitis based on neurological, physical and systemic classification:

Neurological Complications

  • Hearing Loss (Partial or Total): One of the most common long-term effects.
  • Vision Loss: Damage to the optic nerves or brain pathways.
  • Seizures (Epilepsy): Recurrent episodes due to brain irritation.
  • Cognitive Problems: Memory loss, poor concentration, and learning difficulties.
  • Movement and Balance Issues: Coordination problems, muscle weakness.
  • Behavioural Changes: Personality shifts, emotional instability, or developmental delays in children.

Physical Complications

  • Limb Loss/Amputation: Especially in meningococcal meningitis, where sepsis damages tissues.
  • Bone and Joint Problems: Arthritis or chronic pain due to infection spreading.
  • Kidney Damage: From septicemia or complications of treatment.

Systemic Complications

  • Sepsis: Widespread infection in the bloodstream, often fatal if untreated.
  • Increased Intracranial Pressure: Swelling of the brain leading to coma or death.
  • Hydrocephalus: Buildup of cerebrospinal fluid in the brain.
  • Blood Vessel Damage: Stroke or reduced blood supply to parts of the brain.

What is the Prevention for Meningitis?

Prevention is crucial, especially when there are complications of meningitis. The most important measures are vaccination (Hib, pneumococcal, meningococcal), prophylactic antibiotics among close contacts, and good hygiene. Avoid sharing drinks, cover coughs, and ensure proper sanitation. To minimise the risk of listeria, pregnant women must avoid unpasteurised foods.

The prevention of meningitis aims to minimise exposure to infectious agents and enhance immunity, particularly against vaccine-preventable pathogens.

The combination of immunisation, timely prophylaxis, hygiene measures, and lifestyle measures is important in reducing the risk of infection and managing outbreaks.

  • Vaccination: Hib and Streptococcus pneumoniae conjugate vaccines are commonly administered to children. At-risk groups are vaccinated against Neisseria meningitidis. These greatly reduce the incidence of bacterial meningitis.
  • Antibiotic Prophylaxis: Antibiotics (rifampin, ciprofloxacin, or ceftriaxone) should be administered to close contacts of meningococcal cases. Unvaccinated people may need prophylaxis with Hib exposure; this is not standard with pneumococcus.
  • General Hygiene: Handwashing, using separate utensils/drinks, covering coughs, and maintaining space will reduce the transmission. Masks or avoiding crowds may be advised during outbreaks.
  • Safe Food Practices: To prevent listeria, avoid unpasteurised dairy and cook meats properly, particularly in pregnant or immunocompromised people.
  • Vector Control: Prevention of some viral meningitides (arboviruses) may occur through avoidance of mosquito/tick bites, i.e., the use of insect repellent and protective clothing.

FAQs about Meningitis

  1. How quickly can meningitis become dangerous?

Bacterial meningitis may deteriorate in a matter of hours and cause serious complications or death. It is important to have early medical attention.

  1. Can meningitis spread from person to person?

Some types, particularly meningococcal meningitis, are transmitted via respiratory droplets (coughing, sneezing, close contact).

  1. Who is at the highest risk of meningitis?

People at risk are infants, elderly people, immunocompromised patients, and those who live in crowded environments.

  1. Can meningitis occur without fever?

Yes, particularly in neonates, elderly patients or immunocompromised patients where the symptoms can be atypical.

  1. Why is a lumbar puncture important in meningitis?

Lumbar puncture in meningitis assists in the diagnosis and determining the exact cause through analysis of cerebrospinal fluid.

  1. Can meningitis cause long-term disability?

Yes, survivors can have complications such as hearing loss, learning disabilities or neurological impairments.

  1. Is meningitis always contagious?

No, not every form is contagious, fungal, tubercular, or non-infectious; they do not normally pass on between individuals.

  1. What is the role of imaging in meningitis?

In some cases, CT or MRI is performed before lumbar puncture to eliminate elevated intracranial pressure or brain lesions.

  1. Can meningitis recur?

Yes, meningitis can also possibly have recurrent episodes, particularly with some viral infections or immune defects.

  1. Why is early treatment started before confirmation?

Delays in treatment, particularly in bacterial meningitis, may lead to high mortality and morbidity.

Conclusion

Meningitis is a severe disorder that entails inflammation of the meninges and has diverse etiologies. Bacterial forms result in neutrophilic exudates, and viral forms present lymphocytic inflammation. It is important to identify the symptoms early and analyse the CSF as soon as possible. Early intervention and therapy are life-saving.

For NEET-PG students, a clear understanding of the pathology and management of meningitis is crucial not only for exam preparation but also for future clinical practice. For additional guidance, DocTutorials can be your study companion. We offer crisp videos, clinical Qbank, exam-focused notes, flashcards, and mind maps. This helps ensure aspirants gain complete clarity over complex medical topics.

Join DocTutorials today and explore our NEET PG course to excel in your medical career!

NEET PG Online Live Power Pack
DocTutorials App Download Now

Latest Blogs

Bleeding Disorders: Causes, Symptoms, and Treatment

Bleeding Disorders

Bleeding disorders (a category of blood disorders) are a group of conditions caused by abnormalities in the body’s ability to form blood clots, leading to excessive or prolonged bleeding. These disorders can be genetic, caused by a deficiency of clotting proteins, by underlying medical conditions, or by taking certain medications.

For medical students and aspirants, bleeding disorders represent an important topic that connects theoretical knowledge with practical clinical application. Having a proper understanding of its causes, diagnostic approach, and treatment strategies is essential for effective patient management. Read on to learn about bleeding disorders in detail.

What are Blood Disorders?

Blood disorders are conditions affecting red blood cells, white blood cells, or platelets that disrupt normal blood functions and may be inherited or acquired, ranging from mild to life-threatening.

Blood disorders are medical conditions that affect the normal functioning of different components of blood, preventing them from carrying out their essential physiological roles effectively:

  • Your red blood cells are responsible for transporting oxygen from the lungs to all parts of the body.
  • White blood cells are important in the body as they help defend the body against infections by attacking harmful pathogens.
  • Your platelets are responsible for blood clotting, which helps prevent excessive bleeding after injury.

Blood disorders are broadly classified as noncancerous or cancerous. This discussion is specific to non-cancerous blood disorders. A person may either be born with a non-cancerous blood disorder due to genetic factors or develop it later in life due to underlying medical conditions that interfere with normal blood function.

Other blood disorders can be asymptomatic and may not need active treatment, whereas others can be chronic and require lifelong medical care, but do not impact life expectancy significantly.

But some blood disorders may be severe, progressive, and even life-threatening unless diagnosed and treated accordingly. Treatment of blood disorders is carried out by healthcare providers, emphasising symptom management, complication prevention, and, where feasible, treatment of the underlying cause.

What are the Various Types of Bleeding Disorders?

Bleeding disorders include haemophilia, von Willebrand disease, thrombocytopenia, platelet function disorders, DIC (Disseminated Intravascular Coagulation), factor deficiencies, and acquired haemophilia, all affecting normal blood clotting mechanisms.

There are several important types of bleeding disorders, including:

  1. Haemophilia: Haemophilia is a hereditary bleeding disorder that is mostly seen in males. It arises from a lack or complete absence of clotting factors IX and VIII, which are critical to the normal process of blood clotting. Even small injuries may result in extensive bleeding among affected individuals.
  2. Von Willebrand Disease: Von Willebrand disease is a genetic disease that occurs in both males and females. It is caused by a deficiency or dysfunction of von Willebrand factor, a major protein that helps platelets adhere to one another and form stable blood clots to prevent bleeding.
  3. Thrombocytopenia: Thrombocytopenia is a condition characterised by an abnormally low platelet count in the blood. Platelets play a crucial role in clot formation; therefore, their depletion increases the risk of easy bruising and prolonged bleeding.
  4. Platelet Function Disorders: These disorders occur when the platelet count is normal, but platelet function is defective. The impairment can be hereditary or acquired, like specific medications that influence platelet activity.
  5. Disseminated Intravascular Coagulation (DIC): DIC is a serious and life-threatening medical condition that typically occurs as a complication of infection, trauma, or other serious diseases. It is characterised by uncontrolled clot formation throughout the body, followed by excessive bleeding due to depletion of clotting factors.
  6. Factor Deficiencies: Factor deficiencies occur when the body is unable to produce adequate amounts of specific clotting factors required for normal coagulation. Such deficiencies can be either hereditary or the result of medications or underlying illnesses.
  7. Acquired Haemophilia: Acquired haemophilia is a rare autoimmune disorder in which the body produces antibodies that attack and neutralise blood-clotting factors, resulting in spontaneous and uncontrollable bleeding.

What are the Causes of Bleeding Disorders?

Bleeding disorders could be caused by either genetic mutations, liver diseases, medications such as blood thinners, autoimmune diseases, infections, blood cancers, or physical injury. These factors interfere with clotting factor production, platelet function, or normal blood coagulation pathways.

Bleeding disorders may be caused by a number of underlying factors, including:

  • Genetic Mutations: Inherited genetic defects cause conditions such as haemophilia and von Willebrand disease. This impairs the synthesis, structure, or function of clotting factors and associated proteins that are critical to normal hemostasis.
  • Medications: There are some drugs which act to prevent blood clots by interfering with the natural process, making one bleed excessively, even in cases of minor injury, such as anti-clotting drugs and anti-platelet medications.
  • Liver Disease: The liver plays a central role in the production of most clotting factors. Any hepatic injury or chronic liver disease may decrease their production, causing defective coagulation and excessive bleeding.
  • Autoimmune Disorders: Some autoimmune disorders, including systemic lupus erythematosus and rheumatoid arthritis, can lead to abnormal bleeding patterns by attacking blood vessels or clotting factors.
  • Cancer: Blood cancers such as leukaemia and lymphoma can affect bone marrow function, reducing platelet and clotting factor production, thereby increasing the risk of bleeding disorders.
  • Infections: Chronic infections like hepatitis C and HIV (Human Immunodeficiency Virus) may harm the liver or suppress the immune system, which can lead to weakened clotting mechanisms and complications of bleeding.
  • Trauma: Intensive physical trauma or surgery may interfere with the normal processes of blood clotting, causing excessive or uncontrolled bleeding, depending on the severity of the damage to the tissue.

What are Common Blood Disorder Symptoms?

Blood disorder symptoms vary based on the affected blood component and may include fatigue, weakness, pallor, and breathlessness in anaemia. Bleeding disorders commonly present with excessive bleeding, bruising, heavy periods, and signs of internal bleeding or clot formation.

Symptoms of a blood disorder depend on which blood component is affected and the degree to which normal blood function is compromised. Different blood components, including red blood cells, white blood cells, and platelets, can be affected, leading to a diverse range of clinical presentations.

For example, in anaemia, a common blood disorder, patients may experience any of the following:

  • Fatigue and generalised weakness.
  • Dizziness and lightheadedness.
  • Pale or reduced skin colouration compared to normal.
  • Increased heart rate (palpitations).
  • Shortness of breath, especially on exertion.

Bleeding Disorder Symptoms

The most common symptom of bleeding disorders includes unexplained, profuse, or extended bleeding. People with any of the following symptoms need medical advice:

  • Nosebleeds: Recurring nosebleeds that last longer than 10 minutes or more than five times a year.
  • Unusual Bleeding: Wounds that won’t stop bleeding even after 10 minutes.
  • Internal Bleeding: Could be characterised by joint pain, swelling, and stiffness due to blood leaking into joints.
  • Bruising Easily: Bruises without any cause or after experiencing a mild physical injury.
  • Bleeding after Surgery: Any surgical procedure, including dental procedures, that leads to unusual or prolonged bleeding.
  • Excessively Heavy Menstrual Bleeding: Menstrual periods that are unexplained, require regular changing of tampons/pads (every hour) and continue for more than seven days.
  • Postpartum Bleeding: Severe bleeding that persists even after delivery/miscarriage.
  • Blood in Stool: Presence of blood in stool or bleeding during defecation, which may also indicate other underlying conditions and should be evaluated by a healthcare provider.
  • Blood in Urine (Hematuria): Visible blood in urine, especially when associated with urinary urgency or discomfort, requires medical evaluation.

Blood Clotting Disorder Symptoms

People who have blood-clotting disorders may develop an unusual amount of clots in their blood vessels. These clots may form in the veins, lungs, heart, or brain. Some common symptoms include the following:

  • Swelling, pain, and tenderness of the legs: symptoms that may mean deep vein thrombosis (DVT).
  • Shortness of breath combined with chest pain, which may indicate pulmonary embolism.
  • Heart attack symptoms.
  • The symptoms of a stroke.

How are Bleeding Disorders Diagnosed?

Bleeding disorders are diagnosed using blood tests such as CBC, PT, aPTT, mixing studies, clotting factor assays, and genetic testing. These investigations help identify platelet abnormalities, clotting factor deficiencies, and underlying inherited or acquired causes.

Clinical examination, combined with special tests, is used to determine whether a person has an inherited or acquired bleeding disorder. Doctors will prescribe the following tests:

  • Complete Blood Count (CBC): This test evaluates different components of blood, including platelets. If there are few platelets in the blood, a person probably has a platelet disorder rather than a deficiency of clotting factors.
  • Partial Thromboplastin Time (PTT) / Activated PTT (aPTT): This test measures the time required for blood to clot through the intrinsic pathway and helps identify deficiencies in specific clotting factors.
  • Prothrombin Time (PT): This test measures the extrinsic clotting pathway and assesses clotting factors not measured by the PTT test, which helps in general coagulation testing.
  • Mixing Test: This test is used to identify bleeding as due to a deficiency of clotting factors or to the presence of inhibitors, such as antibodies, that disrupt the action of clotting factors.
  • Von Willebrand Factor (vWF) Tests: The tests assess the amount and activity of von Willebrand factor and are used to diagnose various forms of von Willebrand disease.
  • Tests for Clotting Factors: These tests measure the levels of certain clotting factors and may show a deficiency. Low levels of factor VIII might indicate haemophilia A.
  • Bethesda Test: The Bethesda test is performed to detect inhibitors of clotting factors, such as VIII and IX.
  • Tests for Factor XIII: The antigen and activity tests are used to check for a deficiency in Factor XIII that leads to bleeding.
  • Genetic Tests: Genetic testing allows for the diagnosis of inherited mutations that lead to bleeding disorders. In addition, patients might be referred to a genetic specialist to carry out a comprehensive investigation.

How are Bleeding Disorders Treated?

Treatment for bleeding disorders depends on the type and severity and includes iron supplements, blood transfusions, and clotting factor replacement therapy. Additional management options, like plasma transfusions or topical treatments, help control bleeding and prevent complications.

Treatment options depend on the type of bleeding disorder, its underlying cause, and the severity of symptoms. While most bleeding disorders cannot be completely cured, appropriate treatment can effectively control symptoms, prevent complications, and improve quality of life.

Here are the common treatment options:

1. Iron Supplementation

In some situations involving excessive or prolonged blood loss, doctors can prescribe iron supplements to replenish iron stores. Iron deficiency anaemia may result from low iron levels and may produce symptoms such as fatigue, weakness, dizziness, and poor physical performance.

In extreme cases, a blood transfusion might be necessary to replenish normal blood parameters when iron supplementation is inadequate.

2. Blood Transfusion

This treatment consists of replacing lost or deficient blood components with donated blood. To prevent serious blood transfusion reactions, donor blood should match the patient’s blood type. Typically, it is administered in a hospital setting under constant medical supervision.

3. Other Treatments

Depending on the type of disorder, some other forms of treatment can be employed. Localised bleeding in some bleeding disorders can be treated with topically applied agents or nasal sprays.

Other disorders like haemophilia are managed with replacement therapy, by which the lacking clotting factors are directly infused into the bloodstream to prevent or manage episodes of bleeding.

In certain cases, fresh frozen plasma transfusions are used when specific clotting factors are deficient. Fresh-frozen plasma contains important clotting factors, including factors V and VIII, which play key roles in normal blood coagulation. These transfusions are usually performed in a hospital to ensure safety and proper monitoring.

FAQs about Bleeding Disorders

  1. What are bleeding disorders?

Bleeding disorders are conditions associated with the inability of blood to clot normally due to deficiencies in clotting factors, platelets, and clotting mechanisms. People with bleeding disorders experience symptoms such as excessive bleeding, uncontrolled bleeding following an injury, or spontaneous bleeding.

  1. What are the main types of bleeding disorders?

Some common types of bleeding disorders include haemophilia, von Willebrand disease, thrombocytopenia, platelet function disorder, and clotting factor deficiencies.

  1. What are the causes of bleeding disorders?

Common causes of bleeding disorders include genetic disorders (haemophilia is an inherited disorder), low levels of platelets, liver disease, autoimmune disorders, infections, or medications such as anticoagulants.

  1. What are the symptoms of bleeding disorders?

Some common symptoms include frequent nosebleeds, easy and unexplained bruising, bleeding for a prolonged period after an injury or surgery, bleeding excessively during menstruation, bleeding gums, and even internal bleeding, which causes joint pain or swelling in severe cases.

  1. How are bleeding disorders diagnosed?

Diagnosis is done using blood investigations such as complete blood count (CBC), prothrombin time (PT), activated partial thromboplastin time (aPTT), clotting factor assays, and sometimes genetic testing to identify inherited disorders.

  1. Can bleeding disorders be cured?

Most bleeding disorders are incurable, particularly genetic ones, such as haemophilia. However, they can be effectively controlled and managed with long-term treatment and preventive care to reduce bleeding episodes.

  1. What is the treatment for bleeding disorders?

Treatment varies depending on the condition and may include clotting factor replacement therapy, iron supplements for anaemia, blood or plasma transfusions, and medications to manage bleeding. Some cases may also require preventive long-term therapy.

  1. Is haemophilia a common bleeding disorder?

Haemophilia is one of the most well-known inherited bleeding disorders, caused by a deficiency of clotting factors VIII or IX. It mostly happens in males and may cause prolonged bleeding following minor injuries.

  1. Are bleeding disorders dangerous?

Yes, there are bleeding disorders that may be serious or life-threatening, particularly when there is uncontrolled internal bleeding, significant trauma, or postoperative complications. At an early stage, it is necessary to detect and treat the disease to avoid complications.

  1. When should a person see a doctor for bleeding problems?

One should consult a doctor when experiencing frequent unexplained bleeding, bleeding longer than usual, heavy menstrual bleeding, and frequent bruising without injury because these may be signs of an underlying bleeding disorder.

Conclusion

In conclusion, bleeding disorders represent a category of diseases affecting the body’s normal mechanism of clot formation, leading to excessive bleeding, prolonged bleeding, or easy bruising. They are inherited or acquired disorders that vary in severity depending on their cause.

For NEET PG students, having a clear understanding of bleeding disorder is paramount to strengthening knowledge of clinical concepts. For additional guidance, DocTutorials can be your study companion. We offer crisp videos, clinical Qbank, exam-focused notes, flashcards, and mind maps. This helps ensure aspirants gain complete clarity over complex medical topics.

Join DocTutorials today and explore our NEET PG course to excel in your medical career!

NEET PG Online Live Power Pack
DocTutorials App Download Now

Latest Blogs

Bed Wetting: Causes, Symptoms, Diagnosis, and Treatment

Bed wetting

Bed wetting (nocturnal enuresis) is a typical disorder that is characterised by involuntary urination during sleep in a child at the age of 5 years or older. Although this is usually a normal stage of development, it can be a sign of an underlying health problem if it persists into adulthood.

Children develop bladder control skills when they are aged 2-4. Beyond the age of 5, chronic bedwetting is referred to as enuresis and should be assessed. Approximately 15% of children aged 5 continue to wet the bed, decreasing to 10% at age 7 and 5% at age 10. Keep reading to know more.

Classification of Bed Wetting

Bed-wetting, or Enuresis, refers to urinary incontinence during sleep in children older than 5 years. It is categorised by timing (nocturnal vs diurnal), symptomatology (monosymptomatic vs non-monosymptomatic), and history (primary vs secondary).

Pediatric guidelines define enuresis as the involuntary intermittent urination in a child ≥ 5 years. Until the age of 5, it is not regarded as abnormal. Enuresis can be categorised as:

  1. Nocturnal Enuresis (Bed wetting): Nighttime wetting. It is the most prevalent type.
  2. Diurnal Enuresis: Waking up with urinary incontinence.

Further classifications include:

  1. Primary vs Secondary Enuresis

Primary enuresis refers to a child who has not attained a dry period of at least 6 months. Secondary enuresis develops when a child, who has been dry at night for 6 months or more, begins to wet their bed. Secondary enuresis can usually be linked to a developing health or psychological concern (e.g., urinary tract infection, diabetes, or stress).

  1. Monosymptomatic vs Non-monosymptomatic

Monosymptomatic enuresis (MSE) is bedwetting in the absence of lower urinary tract symptoms (LUTS) in daytime. Children with MSE do not have urgency, frequency, or incontinence during the day.

Non-monosymptomatic enuresis (NMSE) is associated with nocturnal enuresis that includes other urine symptoms (daytime incontinence, urgency, frequency, voiding postponement, etc.). NMSE usually necessitates assessment of preexisting bladder or bowel issues.

Causes and Risk Factors of Bed Wetting

There are various factors that contribute to bed wetting. Common causes include genetic predisposition, slowed maturation of the bladder, deep sleep patterns and polyuria at night. Psychosocial stress and medical conditions (UTIs, diabetes, sleep apnea) can also contribute.

The aetiology of pediatric nocturnal enuresis is multifactorial with a significant genetic component, and the overall risk is approximately 44% in the presence of one affected parent and up to 77% in the presence of both affected parents.

Family history is highly penetrant, as are environmental and physiological factors. Here are the other factors:

  • Delayed Bladder Maturation: Nighttime bladder control is often delayed in many children because the bladder (detrusor muscle) and sphincter have not developed well-coordinated responses during sleep.
  • Nocturnal Polyuria: Children with enuresis have abnormal ADH (Antidiuretic Hormone) secretion, resulting in excessive urine production at night. The result is bladder overfilling during sleep without getting up to void.
  • Small Functional Bladder Capacity: A small bladder fills quickly at night, and with profound sleep or an inability to wake up, it leads to bedwetting. Capacity <65% of expected (≈30 + age × 30 mL) indicates a small bladder size.
  • Overactive Bladder/Detrusor Overactivity: Other children experience involuntary bladder contractions that result in urgency and incontinence, both day and night. In NMSE, overactive bladder can be the only problem or a component of the dysfunctional voiding.
  • Sleep Disorders: Sleep disorders such as obstructive sleep apnea predispose the risk of enuresis because they result in excessive urine and poor arousal. Children with the disorder of deep sleep cannot wake up even when the bladder is full.
  • Psychosocial Stress: Enuresis is typically an effect of stress rather than a cause, though significant life events may exacerbate symptoms or lead to secondary bedwetting.
  • Medical Comorbidities: Several health conditions may trigger or aggravate enuresis:
    • Urinary Tract Infection (UTI): Irritates the bladder, leading to urgency and accidents.
    • Diabetes Mellitus: An overload of glucose leads to polyuria (urine volume) that can fill up the bladder at night.
    • Constipation/Faecal Incontinence: A rectum that is loaded can compress the bladder, resulting in both day and night wetting. Treatment of constipation tends to lower enuresis.
    • Neurologic Disorders: The bladder control can be compromised by spina bifida, tethered cord, cerebral palsy, or other neurodegenerative diseases. A disordered stream or daytime symptoms imply a neurogenic or obstructive disorder, requiring specialist evaluation.
    • Pinworm Infection: Enterobius vermicularis can cause perianal irritation, which may result in reflex bladder contractions and enuresis (rare).
  • Deep Sleep Arousal Difficulty: Even without OSA (Obstructive Sleep Apnea), just having really good sleep can cause a child to fail to wake to bladder signals.

Signs and Symptoms of Bed Wetting

Bed wetting, or nocturnal enuresis, is characterised by involuntary urination at night, which is often unrealised by the child. It can be linked with daytime urgency or frequency (in NMSE) and psychological outcomes such as embarrassment or low self-esteem.

Nocturnal enuresis is involuntary urination at night in children who are supposed to have control over their bladders. It is often self-limiting and benign, but it can have emotional consequences, which is why early detection is crucial.

Here are the main symptoms:

  • Nighttime Incontinence: The most noticeable sign is waking up with wet pyjamas or bed linens. Frequent wet nights are commonly reported by parents without any daytime problems. The child never wakes up at the time of the episode and notices it in the morning.
  • Daytime Bladder Symptoms: Normal in monosymptomatic cases. Urgency, frequency and daytime incontinence can occur in children in NMSE. Voiding ≥ 8 times/day or <3 times/day suggests dysfunction, along with signs like squatting, leg crossing, or hesitancy.

Other associated signs and symptoms include:

  • Urinary Tract Infection (UTI) Symptoms: Painful or burning urine, hazy or bloody urine, foul smell, fever indicates UTI or other organic origin and should be evaluated immediately.
  • Faecal Soiling or Constipation: Enuresis may be accompanied by large, hard stools or faecal accidents due to pressure on the bladder caused by rectal factors.
  • Behavioural/Psychological Impact: Symptoms of anxiety, embarrassment, social withdrawal (aversion to sleepovers), and low self-esteem may be observed in a child with bedwetting. Parents and peers should be informed that enuresis is involuntary and not the fault of the child.
  • Frequency & Patterns: Frequent, daily, or intermittent (e.g., 23 nights/week). The diagnosis threshold is generally: 2 or more episodes/week over 3 months. Cases of sporadic (less than 2/month) are usually within the period of normal maturation.

Diagnosis of Bed Wetting

Pediatric enuresis is mostly diagnosed clinically. It includes ensuring the enuresis criteria (age ≥ 5, frequency ≥ 2/week for 3 months) and ruling out other causes through history, physical examination, and simple tests. The tools include a bladder diary and urinalysis.

Pediatric enuresis diagnosis is predominantly clinical and requires confirmation of meeting the criteria and ruling out underlying causes. An organised history, examination, urinalysis, and a bladder diary are most likely adequate. Here’s how the diagnosis goes:

1. Initial Assessment and History

  • Confirm Diagnostic Criteria: Make sure the child is at least 5 years old and has persistent involuntary bedwetting (at least 2 times a week) for at least 3 months.
  • Fluid Intake & Voiding Diary: Monitor fluid timing, volume and voiding patterns to determine bladder patterns, particularly evening intake and last void.
  • Family History: Ask about enuresis in the family history; also, check for a family history of diabetes, polyuria, and kidney disease.

2. Medical History and Comorbidities

  • UTI history: Dysuria, fever, frequency; recurrent UTIs can cause secondary enuresis.
  • Constipation: History of hard stools, infrequent bowel movements, or encopresis. Bladder outlet obstruction (functional) can be caused by severe constipation.
  • Diabetes Symptoms: Polydipsia (excessive thirst), polyphagia (excessive hunger), weight loss, or nocturia (getting up at night to use the restroom) should prompt a check of blood sugar levels.
  • Neurologic Symptoms: Gait abnormalities, lower-limb weakness, or spinal problems indicate neural involvement (e.g., tethered cord).
  • Psychosocial Factors: Recent stressors, behavioural issues like ADHD (Attention-Deficit/Hyperactivity Disorder), and autism that could be associated.
  • Sleep History: Snoring, sleep restlessness, daytime drowsiness, or observed apnea indicates sleep apnea.
  • Drug History: Some medications (e.g., diuretics, stimulant medications) may cause polyuria or worsen enuresis.

3. Physical Examination

  • General Exam: Growth parameters, signs of chronic illness. Check for external stigmata of spina bifida (tuft of hair, dimple) on the lower back.
  • Abdominal Exam: Palpate bladder (for retention), assess for constipation (palpable stool in colon).
  • Genitourinary Exam: Inspect for phimosis, labial adhesions, and anatomic abnormalities (e.g., ectopic ureter). Percuss the kidneys if suspicion of reflux.
  • Neurologic Exam: Strength of lower limbs, reflexes; perineal sensation, anal wink to check tethered cord or neuropathy.

4. Investigations

Most children with isolated nocturnal enuresis require only minimal testing. Key investigations include:

  • Urinalysis: Essential first step to exclude hematuria, infection (nitrites, leukocyte esterase), glucose (diabetes), or protein. Repeat if symptoms warrant.
  • Urine Culture: In case of suspected UTI (fever, dysuria, very frequent voiding) or pyuria on urinalysis, obtain a culture and treat the infection.
  • Blood Tests: Not routine, but consider blood glucose in polyuria-polydipsia; potentially renal function in a structural malady.
  • Bladder Diary/Voiding Chart: Record time and volume of each void daily within a few days. This can aid in differentiating polyuria (very large voids) and frequency (small volumes, numerous voids).

5. Imaging

  • Renal/Bladder Ultrasound: Indicated if there are recurrent UTIs, daytime incontinence, abnormal stream, or suspicion of anatomic abnormality (e.g. hydronephrosis, ureterocele).
  • VCUG (Voiding Cystourethrogram): Consider if ultrasound shows reflux or if bladder outlet obstruction is suspected.

Management and Treatment for Bed Wetting

Treatment of bedwetting in children includes education, behavioural measures, and, if needed, alarms or medications. Conservative first-line treatment includes positive reinforcement, fluid management, and treating constipation, and alarms and desmopressin are implemented in case of inadequate positive responses.

A combination of behavioural therapy and a bedwetting alarm is the most effective and safe long-term treatment. Pharmacotherapy (particularly desmopressin) can be effective to enhance the quality of life (dry nights) but often requires repetition/continuation to achieve long-term effect.

Here’s how the bedwetting treatment and management work:

1. General Principles

  • Reassurance and Education: Educate the family that enuresis is normal, mostly self-limiting, and not the child’s fault. Set realistic expectations, as treatment may take months and relapses can occur, and emphasise support over punishment.

2. Behavioural Strategies

  • Fluid Management: Limit evening fluids (particularly 12 hrs before sleep) and avoid caffeine/sodas. Encourage drinking earlier in the day.
  • Timed Voiding: Create an urge to urinate at regular times (after 2-3 hours) in the daytime and right before sleep. Other parents put reward charts for going to the bathroom prior to sleep.
  • Double Voiding: Instruct the child to urinate twice before bedtime (void, then try again a few minutes later) to ensure the bladder empties fully.
  • Constipation Management: Ensure soft bowel movements. Manage constipation (fibre, stool softeners) because a full rectum may initiate bladder contractions.
  • Protect Bedding: Use mattress protectors and easily washable bed linens. Have an extra pair of pyjamas in case of stress around accidents.

3. Lifestyle and Support

  • Engaging the child in problem-solving (seek their ideas). Provide stickers or praise for dry nights and helpful actions (changing bed clothes).
  • Avoid blaming or shaming. Do not wake children aggressively to empty (it has no benefit); use alarms to condition awakening.
  • If school concerns arise (e.g., daytime wetting), communicate with school nursing staff about toilet breaks or discreet pull-up garments, if needed.

4. Pharmacologic Therapy

Medication is reserved for when behavioural methods alone fail or for short-term situations (sleepovers, camps). Options include:

  • Desmopressin (DDAVP): A synthetic analogue of vasopressin (antidiuretic hormone). It decreases nocturnal urine production.
    • Use: First-line medication in monosymptomatic enuresis. It can be taken before going to sleep via nasal spray or oral pills.
    • Efficacy: Reduces nighttime urine output and increases the likelihood of a dry night by about 50% on average. Nevertheless, its effect subsides with discontinuation, hence it is typically intermittent or short-lasting. Not curative, but useful to manage special occasions.
    • Caveat: Risk of water intoxication and hyponatremia if too much fluid is consumed; fluid restriction (no drinking 1 hour before and after dose) is important.
  • Tricyclic Antidepressants (e.g., Imipramine): Previously used widely, now second-line because of safety issues.
    • Use: May be considered if alarms and desmopressin fail. Mechanism includes increased ADH and bladder relaxation.
    • Efficacy: Can increase dry nights by around 1 per week.
    • Caution: Risk of overdose is severe (cardiotoxicity, seizures). Contra-indicated in families where there is a risk of overdose. The use is standard with ECG before use, dose-limited, and short courses.
  • Anticholinergic Agents (e.g., Oxybutynin, Tolterodine): Indicated when symptoms of overactive bladder during the day are observed or when a small capacity of the bladder is reported. They relax the detrusor muscle.
    • Use: If the child has daytime urgency or frequency, or if an ultrasound shows a small bladder. May be added to desmopressin in refractory cases.
    • Side Effects: Dry mouth, constipation, blurred vision; should be used cautiously in children.

Prevention and Home Care for Bed Wetting

Whereas the prevention (in the sense of preventing it before it occurs) of bedwetting is somewhat constrained, since it is basically a matter of developmental timing, home care is about promoting the child’s maturation and preventing triggers.

Prevention of bedwetting is not always possible because it is a developmental complication, but with the support of home care, it can be reduced, and the control of the bladder can be improved.

Some of the important measures include:

  • Habit Training: Educate young children about proper toilet habits early (e.g., sitting posture, completing void).
  • Family Awareness: Discuss family stress and provide a supportive environment (do not make fun of the child about wetting).
  • Bowel Management: Avoid constipation by means of a high-fibre diet. A hard stool should be avoided, as it is a contributor to bladder dysfunction.
  • Sleep Hygiene: Sleep well and still; maintain good bedtime habits (use the bathroom before going to sleep; do not go to sleep right after heavy fluid consumption).
  • When to Seek Help: A medical examination is advised when bedwetting is regular, when the child is concerned about it, or when there are concerns (UTI, daytime wetting, systemic illness).

FAQs about Bed Wetting

  1. At what age is bedwetting considered normal?

Bedwetting most often occurs among younger children and is mostly normal through the age of approximately 5 years. When a child who is 5 years or over experiences frequent episodes (at least twice a week during 3 months), it is diagnosed as enuresis.

  1. What is the difference between primary and secondary enuresis?

Primary enuresis is when a child has never attained a dry spell of at least six months. Secondary enuresis is the reappearance of bedwetting in children who have been dry for six months or more.

  1. How is bedwetting diagnosed?

Clinical diagnosis of bedwetting is made on the basis of age, frequency of wetting, medical history and simple tests like urinalysis to eliminate other causes.

  1. What are the first-line treatments for enuresis?

Some of the initial treatment interventions are lifestyle and behavioural factors, which involve reducing evening fluid intake, scheduling voidings, constipation, and reward systems.

  1. When should alarm therapy be used?

Alarm therapy is recommended if initial measures do not work. It is especially effective among children and families who are eager to adhere to the regimen.

  1. What medications are used for nocturnal enuresis treatment?

The most widely used medication is desmopressin. In certain circumstances, other alternatives, such as imipramine or oxybutynin, nin can be looked into.

  1.  Which is more effective: alarms or medication?

Long-term alarm therapy is better as it trains the child, whereas drugs give short-term relief and are linked with relapse after discontinuation.

  1. Is enuresis a psychological problem?

Enuresis is more of a developmental issue, rather than a psychological disorder, though it can result in emotional distress or conditions like ADHD.

  1. Can bedwetting be prevented?

There is no guaranteed way to prevent bedwetting, but good toilet training, curing the constipation and avoiding taking fluids at night could help minimise the need to consult a doctor.

  1. When should a doctor be consulted?

Consultation with the doctor is required when the child is 5 years old or above and has frequent bedwetting, or in case of other symptoms, namely, daytime wetting, pain, or recurrence after dry days.

Conclusion

Bed wetting (pediatric enuresis) refers to a highly prevalent involuntary urination in sleep. For NEET PG, concentrate on classification, causes, and diagnosis. Behavioural measures, alarms, and medications are part of management; most children outgrow them.

 For additional guidance, DocTutorials can be your study companion. We offer crisp videos, clinical Qbank, exam-focused notes, flashcards, and mind maps. We help ensure aspirants gain complete clarity over every complex medical concept.

Join DocTutorials today and explore our NEET PG course to excel in your medical career!

NEET PG Online Live Power Pack
DocTutorials App Download Now

Latest Blogs

Perineal Tears: Symptoms, Causes, and Treatment

Perineal Tears

Not all childbirth-related complications are widely understood or openly discussed. One such condition is perineal tears. It is a type of injury that affects the area between the vagina and the rectum, commonly occurring during vaginal delivery.

A perineal tear can range in severity from minor skin involvement to deeper tissue damage and is classified into four grades. Sometimes, a surgical intervention known as an episiotomy can be performed to create a controlled opening and assist with the delivery process. Keep reading to learn about its types, causes, and treatment to improve care and recovery for the mother.

What are Perineal Tears?

Perineal tears are injuries to the area between the vagina and anus that commonly occur during vaginal childbirth. They can range from mild skin tears to deeper tissue damage. 

A perineal tear or vaginal tear is a type of injury that may occur during birth. Also referred to as a perineal laceration, it involves a tear in the tissues surrounding the vagina and the perineum. The perineal region, commonly called the perineum, is the area located between the vaginal opening and the anus.

During a vaginal birth, the skin around the vagina naturally thickens and becomes more flexible. This process helps the baby’s head and body pass through more easily. Despite this natural adaptation, tearing is quite common. In fact, up to 90% of women who have a vaginal delivery experience some degree of tearing.

However, several factors can increase the likelihood of a vaginal tear. These include:

  • A larger-than-average baby
  • An early birth that does not give the skin time to stretch adequately
  • The use of instruments such as forceps during delivery

What are the Various Types of Perineal Tears?

Perineal tears are classified into 4 degrees: first-degree (minor skin tear), second-degree (involves skin and muscles), third-degree (extends to the anal sphincter), and fourth-degree (reaches the rectum).

Vaginal tears can be categorised into 4 grades according to severity. The size of the tear defines its type. Here are the various types of vaginal tears:

  1. First-degree Tear: This is the mildest form of tearing. It only infects the external skin around the vagina and perineum and is usually self-healing and does not require stitches.
  2. Second-degree Tear: This is the most frequently occurring type. The tear goes deeper, affecting both the skin and the underlying muscles of the vagina and perineum. Stitches are usually required for proper healing.
  3. Third-degree Tear: This type of tear extends further, reaching from the vaginal area to the anus. It involves damage not only to the skin and perineal muscles but also to the anal sphincter muscles, which control bowel movements. Stitches are necessary for recovery.
  4. Fourth-degree Tear: This is the most severe and least common form of tearing during childbirth. It extends from the vagina through the perineum, affecting the anal sphincter muscles and reaching into the rectum.

In such cases, the healthcare provider may need to perform the repair in an operating room instead of the delivery room.

What are the Causes of Perineal Tears?

Perineal tears can be caused by childbirth, sexual intercourse, shaving, waxing, vaginal dryness, and other conditions that make the skin weak and vulnerable to any type of injury. Other factors that cause perineal tears include having a large baby, quick labour, vaginal birth for the first time, or decreased skin elasticity.

Most of the cuts or tears in the vagina are commonly linked to activities such as sexual intercourse, shaving, or waxing. However, there are many other cases in which someone ends up developing a tear in and around the vagina, including pre-existing skin problems or giving birth.

Here are the primary causes involved:

  • Sexual Intercourse

Sexual intercourse is one of the common reasons why some women develop perineal tears. Lack of proper vaginal lubrication might lead to such an injury. Intense sexual activity and using sex toys might also contribute to tearing the vaginal area.

  • Shaving and Waxing Pubic Hair

Shaving and waxing pubic hair are also common factors that result in cuts on the vulva. According to research conducted in 2017, about 25.6% of those who groomed their pubic hair sustained cuts, most of which were vulvar cuts in women. In some cases, these injuries required medical treatment, such as antibiotics or even minor surgery.

  • Childbirth

About 80% of women experience perineal tearing during childbirth. A perineal tear refers to damage to the skin or muscles of the perineum, which is located between the vagina and the anus. In some cases, the tear could affect the vagina and even the anal sphincter that controls bowel movements.

Women who are giving birth for the first time are generally at a higher risk of experiencing perineal tears compared to those who have previously had a vaginal delivery.

  • Skin Conditions

Certain skin conditions can make the vaginal or vulvar area more prone to cuts and irritation. These include:

  • Eczema is a skin condition characterised by red, inflamed, and itchy skin. Symptoms of eczema include fluid exudation, crusting, and itching in the vagina and vulva.
  • Lichen Planus is an inflammatory disease that causes itchiness, burning, or a feeling of raw skin in the vulva. If the disease affects the vagina, there will be yellowish sticky discharges and tissue destruction.
  • Psoriasis, a common skin condition that is characterised by itchy and dry scales. However, in the vulvar region, Psoriasis manifests as smooth, pink spots with well-defined edges.
  • Lichen Sclerosus, an inflammatory skin disease that primarily affects the genitalia. The affected skin is easily torn or develops fissures.
  • Vulvovaginal atrophy (atrophic vaginitis), a condition that causes the vaginal tissues to become thinner, drier, and less elastic, making tears more likely.
  • Vaginal scarring or tissue damage, which may result from prior surgeries or radiation treatments in the pelvic region.
  • Vulvovaginitis, commonly caused by Candida albicans (also known as thrush), may irritate the tissues and predispose them to cuts.
  • Genital herpes (herpes simplex infection), which may develop clusters of fluid-filled blisters that may rupture and leave tiny open sores that look like cuts.
  • Other Causes

Other factors that may contribute to the formation of vaginal or vulvar cuts include:

  • Foreign body insertion into the vagina
  • Tampon insertion or extraction errors
  • Vaginal dryness
  • Vaginismus
  • Thinning of the vaginal tissue due to age
  • Steroid medication usage

What are the Symptoms of Perineal Tears?

The perineal tear symptoms typically involve pain, burning, swelling, tenderness and discomfort in the vaginal or perineal region, particularly during sitting, walking or during urination. In more serious instances, one might experience bowel or bladder control problems, emotional distress, and pain that impact daily activities and postpartum recovery.

In case of a perineal tear, a variety of symptoms can occur that disrupt everyday comfort and normal activities. It is essential to identify these symptoms to obtain the necessary treatment and aid recovery in a timely manner.

Physical symptoms may include:

  • Perineal pain or discomfort immediately after the tear, which is usually sharp, burning, or tender, particularly during motions or during use of the toilet.
  • Inability to sit, stand, or walk comfortably, which may cause problems in performing routine tasks or taking care of a newborn.
  • Bladder or bowel changes, including difficulty urinating or urgency, especially with more severe tears.

Emotional and functional effects may include:

  • Feelings of anxiety related to healing or concerns about resuming intimacy
  • Difficulty managing daily activities, including maintaining hygiene or caring for a baby
  • Uncertainty about which physical activities are safe during the recovery phase

How are Perineal Tears Diagnosed?

Perineal tears are determined by a careful physical examination whereby the medical practitioner examines the vaginal and perineal tissues to determine the extent of the injury. Reviewing the patient’s symptoms and medical history also helps identify whether the tear is new, recurring, or associated with other underlying conditions.

A healthcare provider usually conducts a physical examination and analyses your medical history to diagnose a vaginal or vulvar cut. This procedure helps them understand your symptoms and identify any underlying conditions or contributing factors that might have caused the injury.

They can also question you about the symptoms, whether they are new or recurrent, to find out whether you have had a history of similar problems. When the cuts are tiny or barely visible, the provider may use a colposcope, a specialised instrument with a bright light, to closely examine and magnify the affected area during the assessment.

Diagnostic Tests

In most situations, additional tests are not necessary to diagnose or manage vaginal or vulvar cuts, especially when the cause is clear and the injury appears minor without signs of infection.

In contrast, tests may be necessary when it is critical to establish whether there are any underlying conditions that might contribute to the injury. Tests that might be required include:

  • Culture: A sample of vaginal discharge is collected by swab and brought to the lab to determine infections such as bacterial vaginosis, yeast infections, or sexually transmitted diseases.
  • Biopsy: A small tissue sample is collected from the tear site for microscopic evaluation to determine the underlying causes of repetitive or persistent tears of the vagina.

What is a Perineal Tear Treated?

Perineal tears are treated based on their severity: mild tears usually heal on their own, whereas moderate to severe tears are treated with dissolvable stitches to repair the damaged tissue. Recovery is supported by pain-relief methods, proper hygiene, hydration, stool softeners, and cooling pads to reduce discomfort and promote faster healing.

The strategy for dealing with a vaginal or perineal tear varies according to the severity of the tear. First-degree tears do not require stitches because they can heal on their own. Second-, third-, and fourth-degree tears require stitches to repair the injured tissues and ensure proper healing.

Dissolvable sutures are used to sew these tears, and the stitches dissolve on their own after six weeks. In the case of the anal sphincter, the medical practitioner may opt for a more complex repair using dissolvable sutures. Some discomfort is expected as the tear heals.

There are some measures that you can take to ease the discomfort and promote rapid healing of the tear:

  • Thoroughly cleanse the area after going to the bathroom.
  • Pat the area dry gently using toilet paper without rubbing or wiping.
  • Maintain adequate hydration to prevent constipation, and, if necessary, use stool softeners.
  • To avoid any pain or irritation of the tear, healthcare providers can advise using cooling pads and sanitary pads after delivery.

FAQs about Perineal Tears

  1. How long does it take for a vaginal tear to heal?

Most women begin to notice relief from the discomfort caused by a vaginal tear within about two weeks. If stitches are required, they generally dissolve on their own within approximately six weeks.

In most cases, there is no need for a follow-up visit to remove stitches or for additional treatment, as healing occurs naturally.

  1. Can a woman have a vaginal delivery in a second pregnancy if she had a vaginal tear previously?

In most situations, having a tear during a previous delivery does not mean it will happen again in future childbirths. Small tears normally heal well, and they do not disrupt subsequent vaginal births.

However, if a woman has experienced a third- or fourth-degree tear before, there may be a slightly increased risk of tearing in subsequent vaginal births.

  1. When should I start pelvic floor physical therapy after experiencing a perineal tear?

Individuals may recover at an individual rate, but most people can start gentle pelvic floor therapy at 6 to 8 weeks after delivery, provided that their healthcare provider approves it.

It can also be helpful to schedule an earlier consultation to discuss recovery strategies and receive guidance on the healing process.

  1. What can I do to prepare my perineum for childbirth and potentially minimise tearing?

Preparation can typically start during the third trimester. Techniques such as perineal massage, specific strengthening exercises, and learning optimal birthing positions may help reduce the likelihood of tearing.

A trained professional can guide you through safe and effective, evidence-based methods tailored to your body’s needs.

  1. Will scar tissue from perineal tearing cause long-term problems?

Scar tissue is a normal part of the body’s healing process. With appropriate care, including physical therapy, it is usually possible to maintain flexibility and prevent tightness or discomfort, ensuring normal function over time.

  1. What are the risks of untreated severe perineal tears?

Unless properly treated, third- or fourth-degree tears can lead to complications like infection, persistent pain, urinary or faecal incontinence, and discomfort during sex. Immediate treatment and correct follow-up are important in the prevention of chronic complications.

  1. How can I manage pain after a perineal tear?

A combination of prescribed drugs, cold compresses or cooling pads, and proper hygiene can be used to manage pain. A sitz bath can also be helpful. Strain should be avoided when passing stool, loose-fitting garments should be used, and sufficient rest should be taken to aid healing.

  1. When is it safe to resume sexual activity after a perineal tear?

The majority of healthcare practitioners recommend waiting until the tear has completely healed before engaging in sexual activity, which is about six weeks following childbirth.

However, this timeline may vary depending on the severity of the tear and individual recovery, so it is best to consult your doctor before restarting sexual activity.

  1. Can perineal tears affect future pregnancies or deliveries?

In general, minor tears do not have any significant impact on future pregnancies or childbirth. Nevertheless, females with more severe tears (third and fourth degrees) might be at an increased risk during subsequent births.

Depending on your medical history, your healthcare provider will assist in identifying the safest delivery option.

  1. Are there any warning signs of infection during healing?

Yes, some symptoms can indicate an infection. These include pain, swelling, redness, abnormal or foul-smelling discharge, fever, or delayed recovery. If any of these signs appear, it is important to seek medical attention promptly to avoid further complications.

Conclusion

Perineal tears are a common childbirth condition that usually heals in a few weeks under good care. While most cases recover completely within 6 weeks of delivery, the severity can vary depending on the degree of the tear. Seeking guidance from a healthcare expert ensures better healing and reduces the risk of complications.

For additional guidance, DocTutorials can be your study companion. We provide clear videos, clinical Qbank, exam-oriented notes, and flashcards. This helps ensure aspirants gain complete clarity over complex medical topics.

Join DocTutorials today and explore our NEET PG course to excel in your medical career!

NEET PG Online Live Power Pack
DocTutorials App Download Now

Latest Blogs

Thermal Injury: Causes, Symptoms, and Treatment

Thermal injury types and cause

Thermal injuries (burns) are tissue damage caused by external heat sources, e.g., flame, hot liquids, steam, chemicals, electricity, or long-term radiation. These injuries are either superficial, first-degree burns, or deep full-thickness (third- or fourth-degree) burns, including those that affect more than one organ system when extensive.

In forensic medicine, the study of burn injuries is important in determining the cause and mode of injury or death. Keep reading to know more about its types, causes, diagnosis and treatment.

Classification of Thermal Injuries

There are 3 types of thermal injuries, classified by depth and mechanism. The depth of burns is superficial to full-thickness and deeper. Mechanisms include scalds, flame burns, contact burns, electrical burns, chemical burns, and radiation burns.

Thermal injuries are classified by the mechanism of injury and the depth (degree) of skin damage. The following table summarises the burn depth and features:

Burn DegreeSkin Layers InvolvedKey FeaturesHealing Time
First (Superficial)Epidermis onlyRed, dry, painful, no blisters; blanches on touch~5–10 days; heals without scarring
Second (Partial)Epidermis + part of dermisRed/moist with intact or ruptured blisters; very painful; blanches2–3 weeks; may scar
Third (Full)Epidermis + dermis + subcutaneousLeathery, white/brown/charred; painless (nerve loss); does not blanch>8 weeks; requires surgery

Fourth-degree burns (deep burns) penetrate all layers of the skin into muscle, bone or organs and result in charring. These are life-threatening and must always be surgically treated.

By mechanism, thermal injuries include:

  • Scalds: Caused by hot liquids or steam (common in children).
  • Flame Burns: Due to open-fire or clothing ignition.
  • Contact Burns: Through contact with hot things (e.g., metal, irons).
  • Electrical Burns: From AC (alternating current) or DC (direct current), producing serious thermal damage along the current path.
  • Chemical Burns: Caused by acids or alkalis; they chemically generate heat on tissue contact.
  • Radiation Burns: As a result of long UV (ultraviolet) exposure (sunburn) or ionising radiation.

Proper classification assists in estimating the total area burned and the treatment area. For example, the “Rule of Nines” divides the body into regions of 9% TBSA (total body surface area) each (e.g. head 9%, each arm 9%).

In children, the “Lund-Browder” chart adjusts for proportion changes. The severity of the burns is also graded (minor, moderate, major) according to TBSA, depth, age, and location.

Pathophysiology of Thermal Burns

Thermal injury causes protein denaturation and forms three zones: coagulation (necrosis), stasis (at risk), and hyperemia (reversible). Major burns cause fluid loss, shock, inflammation, and such complications as infection, respiratory damage, and organ failure.

Cellular damage from thermal energy includes protein denaturation and membrane destruction. Burns leave a characteristic three-zone pattern in the skin. They are:

  1. Zone of Coagulation: Central, irreversibly necrotic tissue.
  2. Zone of Stasis: Surrounding ischemic tissue that may survive or progress to necrosis.
  3. Zone of Hyperemia: Outer area with reversible injury.

Burns are dynamic, meaning the initial injury can worsen over a few hours or days (e.g., the stasis zone worsening). Larger size burns (>20% of body surface) result in a systemic inflammation response. It increases capillary permeability, resulting in excessive fluid loss (burn shock) and intravascular volume depletion. 

Hypotension and hypoperfusion follow if not corrected. Exposure to superheated air or combustion products may also damage the airways and lungs, leading to respiratory failure. Tissue necrosis from burns also impairs the skin’s functions: infection barrier, temperature regulation, and fluid retention.

Loss of these functions leads to a high risk of infection, hypothermia, electrolyte imbalance, and organ dysfunction. Systemically, severe burns can cause hypermetabolism and release of inflammatory mediators (cytokines, prostaglandins), which, in turn, may result in the systemic inflammatory response syndrome (SIRS) and multi-organ failure.

In forensics, extensive burns may also result in poisonous exposures: carbon monoxide (in smoke) and cyanide (in plastics) intoxication are frequent causes of death.

Causes and Risk Factors of Thermal Injury

The burn definition medical professionals use describes the injury as damage to bodily tissues caused by hot liquids, flames, hot objects, electricity, lightning, chemicals and sunlight. The risk is high with the extremes of age, work-related exposures, and substance use, as well as unsafe homes. Burn patterns are used in forensic practice to determine the cause and manner of injury, such as possible abuse or homicide.

Thermal burns arise from many sources of excessive heat. Common causes include:

  • Scalding liquids (hot water, steam, oil).
  • Open flames (house fires, explosives).
  • Hot objects (steam irons, stoves), and sunlight (ultraviolet).

Electrical injury or joule burn produces heat within the body when current passes through tissues, and there are usually entry and exit wounds. However, during a lightning strike, a filigree burns (also known as a Lichtenberg figure, arborescent burn, or feathering) is a distinctive, fern-like pattern on the skin

. Chemical burns (strong acids or alkalis) cause thermal-like injury via exothermic reactions.

Risk Factors

Certain conditions predispose to burns:

  • Age Extremes: Young children and the elderly have thinner skin and slower reflexes to avoid hot sources.
  • Occupational Hazards: Firefighters, industrial workers handling hot materials, and kitchen staff are at greater risk of exposure to flames.
  • Substance Use: The effect of intoxication by alcohol or drugs compromises judgment near fire and hot materials.
  • Domestic Risks: Lack of smoke detectors, unsafe stoves or heaters, and poor supervision of children.

The pattern and distribution of burns are also indicative of a cause in forensic practice. For example, “forced immersion” scalds (symmetrical burns on buttocks and extremities with distinct scald lines) raise suspicion of abuse in children or vulnerable adults.

Necklacing (homicidal burning method using a tyre) is a classic forensic burn scenario. The identification of these patterns aids forensic professionals in determining whether the injuries were deliberate, unintentional, or caused by others.

Clinical Features and Symptoms of Thermal Injury

Thermal burns are characterised by redness, blisters, swelling, charring, and eschar, whereas inhalation injury is characterised by facial burns, soot, and respiratory distress. Severe burns may result in oedema and renal failure.

Thermal burns have varying symptoms based on depth and extent. In partial-thickness (nerve endings are exposed) burns, pain is intense, but in full-thickness burns (nerve destruction), pain can be surprisingly weak. Common signs include:

  • Redness (erythema)
  • Blistering
  • Swelling
  • Charring
  • Eschar formation

In inhalation injuries, one may see:

  • Facial burns
  • Singed nasal hairs
  • Soot in the mouth or sputum
  • Hoarseness
  • Respiratory distress

Fluid shifts cause generalised oedema and often oliguric renal failure in severe cases. In forensic examination of a burned body, several findings distinguish antemortem from postmortem burns:

FeatureAntemortem BurnPostmortem Burn
Skin rednessPresent (due to vasodilation)Absent (no circulation)
BlistersPresent: fluid rich in albumin and chlorideMay occur; contain air/thin fluid
Soot in airwaysCarbon particles in the trachea/lungsAbsent
Carboxyhemoglobin (CO-Hb)Elevated (>10%) from smoke inhalationNormal
Haemorrhage at the injury sitePresent (capillaries intact)Absent (no vital reaction)
Curling’s ulcer (duodenum)Common in fatal burns (stress ulcers)Absent

Other notable forensic findings include “pugilistic attitude” – a flexed posture of burned bodies due to muscle contraction at >60°C – and heat fractures of bones (bones split due to dehydration, often with a distinctive pattern that does not cross suture lines).

Burned bodies also exhibit thermolysis of soft tissues and “parchment” skin. The cause of death in fire victims is often inhalation injury (asphyxia from smoke, CO or cyanide poisoning) rather than cutaneous burns.

Findings in forensic reports can include lung weight, cherry-red tissue discolouration (CO poisoning), and cyanide atomic absorption.

Medical Diagnosis of Thermal Injury

Medical diagnosis of thermal injury involves both forensic and clinical evaluation. Forensic methods help determine the cause, severity, and identity, while clinicians assess burn size, depth, and related complications, such as inhalation injury.

Forensic-medical diagnosis of thermal injuries involves thorough external and internal examination. Investigations may include:

  • Autopsy: Close dissection to determine depth of burns, internal organ injuries, and smoke inhalation.
  • Toxicology: Determining the quantity of carboxyhemoglobin, cyanide, and other poisonous gases formed during combustion is essential.
  • Histopathology: Skin biopsies can confirm the vitality of burns (e.g. neutrophils, red blood cells), extravasation in antemortem burns, and estimate the age of lesions.
  • Imaging: Post-mortem CT (computed tomography) scans of the body could reveal heat fractures or retained foreign material.
  • Forensic Odontology/Anthropology: Dental or skeletal analysis can help identify severely burned remains.

In clinical diagnosis, the healthcare practitioners measure the size and depth of the burns. The “Rule of Nines” or Lund-Browder chart quantifies TBSA. The depth is assessed by appearance, capillary refill (blanching), pain, and sensation. Patients with burns should be evaluated for associated injuries (inhalation, trauma) and for burn severity.

Management and Treatment of Thermal Injury

Thermal injuries are initially managed using the ABC principles (immediately after injury): airway protection, fluid resuscitation using the Parkland formula, and analgesics. Proper wound care, infection prevention, and tetanus prophylaxis are essential. Severe burns are surgically managed and strictly supported, with nutrition and observation of complications.

Initial management of thermal injuries follows trauma protocols (ABCs). Key steps include:

  • Airway and Breathing: Check for inhalation injury. Early intubation in case of respiratory distress or facial burns.
  • Circulation: Start large-bore IV access promptly. Remove constricting clothing/jewellery.
  • Fluid Resuscitation: For major burns, aggressive IV fluid resuscitation is required. The Parkland formula is a standard guideline:

4 mL × body weight (kg) × % TBSA (second/third-degree only) of lactated Ringer’s over 24 hours, with half in the first 8 hours. Adjust fluid to maintain urine output (0.5–1 mL/kg/h in adults).

  • Pain Control: Give analgesics (when necessary- opioids) as burns are painful.
  • Burn Care: Cool the burn with lukewarm (not ice-cold) water to limit depth. Gently clean and debride wounds. Use topical antimicrobials (e.g. silver sulfadiazine) to avoid infection. Cover with a sterile dressing.
  • Tetanus Prophylaxis: Update tetanus immunisation, as burns are prone to tetanus.
  • Wound Management: Superficial burns heal spontaneously. Partially-thickness burns can need debridement and specialised dressings. Full-thickness burns require surgical treatment (excision and grafting).
  • Supportive Care: Monitor for shock (IV fluids, hemodynamic monitoring), provide nutritional support (high-calorie diet), and prevent hypothermia (warm ambient temperature).

Admit to a burn centre if criteria are met (e.g. >20% TBSA, face/hands/genitals, electrical/chemical burns).

Rehabilitative therapy, scar management (pressure garments), and reconstructive surgery are treatment options that may be used on a long-term basis.

Prevention of Thermal Injury

Thermal injury prevention involves fire control, safe kitchen operations, controlled water temperature, and workplace safety precautions. Social consciousness and safety laws help reduce the incidence of burns, although forensic vigilance is important for identifying abuse or arson.

Preventing thermal injuries is critical, especially in high-risk settings. Safety measures include:

  • Fire Safety: Install working smoke detectors and keep fire extinguishers accessible. Practice fire escape plans.
  • Kitchen Safety: Use hot liquids with caution; handle pot handles carefully; be cautious around stoves. Never leave cooking unattended.
  • Water Temperature: Set water heaters to less than 120 F (49 C) to avoid scalds; check bath water temperature.
  • Workplace Precautions: Use protective equipment (gloves, face shields) when handling hot materials or chemicals. Follow electrical safety protocols.
  • Education: Educate children on fire safety, do not play with matches, lighters or fireworks.
  • Sun Protection: Wear sunscreen and protect yourself to avoid radiation burns (sunburn).

FAQs about Thermal Injuries

  1. How are burns classified by degree?

Burns can be categorised as deep: first-degree (epidermis, only, red, painful), second-degree (partial-thickness, blisters, very painful), and third-degree (full, charred, often painless). The fourth-degree burns extend to muscle or bone.

  1. What is the Rule of Nines?

The Rule of Nines is a quick method to estimate burn surface area. In adults: head/neck = 9%, each arm = 9%, anterior trunk = 18%, posterior trunk = 18%, each leg = 18%, perineum = 1%.

  1. How can you tell if burns occurred before death?

Antemortem burns show vital reactions – redness, blisters with protein fluid, haemorrhage at edges, and soot in airways. Blood tests reveal high carboxyhemoglobin and cyanide. Postmortem burns do not have these signs (there is no inflammation or inhaled soot).

  1. What is “pugilistic attitude”?

It is a typical flexed posture of a burned body due to muscle shrinkage in heat (> 60 °C). It resembles a boxing stance and results from heat-stiffened muscles.

  1. How are burns managed initially?

Follow trauma ABCs: secure airway (intubate if needed), support breathing, then start IV fluids. Cool the burn, provide analgesics, clean/debride wounds and place sterile dressings. Use formulas such as the Parkland formula (4 mL × kg × % TBSA) to guide fluid resuscitation.

  1. What is the Parkland formula?

A guideline for fluid resuscitation in major burns: 4 mL per kg of body weight per cent of TBSA burned (2nd/3rd-degree burns) of lactated Ringer’s in the first 24 hours. Half of that volume is given in the first 8 hours after the burn.

  1. Can electric injuries be considered thermal burns?

Electrical injuries cause serious thermal damage along current paths, but they also cause internal organ injury (arrhythmias, muscle damage). When providing a forensic classification, an electrical burn is frequently mentioned in contrast to a thermal burn.

  1. How do chemical burns differ from thermal burns?

Chemical burns occur due to an exothermic reaction with acid or alkali and can extend the damage to tissue until the agent is eliminated. They are treated by copious irrigation and neutralisation, unlike simple cooling for thermal burns.

  1. Why is burn depth painful initially but not in full-thickness burns?

Partial thickness burns reveal nerve ends, resulting in severe pain. Full-thickness burns destroy the nerves within the affected area; the victim might not experience any pain within the burnt area.

  1. What are some key forensic signs of burn-related death?

In addition to vital reactions, there is soot in the airways (from inhalation), thermal fractures of the bone, black lung (from inhaled carbon), and internal signs of systemic poisoning (e.g., cardiac carbonisation, cerebral infarcts due to hypoxia).

Conclusion

Burns can be thermal, chemical, radiation-induced, or electrical, each with distinct forensic and medical consequences. Medical students and forensic trainees must be able to understand burn classification, pathophysiology, and related factors.

In NEET PG forensic medicine, the Rule of Nines, burn depth features, and vital reactions in burns are high-yield topics. For additional guidance, DocTutorials can be your study companion. We offer crisp videos, clinical Qbank, exam-focused notes, flashcards, and mind maps.

Join DocTutorials today and explore our NEET PG course to excel in your medical career!

NEET PG Online Live Power Pack
DocTutorials App Download Now

Latest Blogs

Sarcoidosis: Causes, Symptoms, Diagnosis, and Treatment

sarcoidosis.

Sarcoidosis is a systemic inflammatory disease which is characterised by the formation of noncaseating granulomas in various organs. Typical presentations are bilateral hilar lymphadenopathy and changes in the interstitial lung, although sarcoidosis may occur in the skin, eyes, heart, and other organs.

This NEET-PG pathology review covers sarcoidosis aetiology, clinical features, diagnostic criteria, management, and complications, emphasising information relevant for medical students. Keep reading to know more.

What are the Causes of Sarcoidosis?

The exact cause of sarcoidosis is unknown. It is thought to have an exaggerated response of the immune system to unknown antigens. Risk is genetically predisposed, affected by race and environment.

There is no single known cause of sarcoidosis, and its formation is associated with a mixture of genetic and environmental factors, as well as immune-related factors:

  • Unknown Aetiology: No specific trigger is found. Sarcoidosis is likely an autoimmune response (primarily Th1-mediated) to microbial or environmental antigens. Exposures (beryllium, insecticides, mould), infections (mycobacteria, Propionibacterium acnes) are investigated, but none of them can explain all the cases.
  • Genetic Factors: Genetic predisposition is indicated by familial clustering and HLA (Human Leukocyte Antigen). There are also specific HLA-DR alleles and ACE (Angiotensin-Converting Enzyme) gene variants associated with susceptibility, which point to heritable immune hyperreactivity.
  • Demographics: Most prevalent among adults between 20 and 40 years. It occurs more in African Americans than in whites, and the morbidity among African American females is the highest. Women tend to experience extrapulmonary disease, whereas men tend to exhibit cardiac involvement.
  • Geographic/Seasonal Factors: Seen worldwide but more common in northern latitudes and urban areas. There is some seasonal variation, but there are no definite prevention measures.
  • Immune Factors: Patients have an exaggerated cellular immune response at disease sites, characterised by CD4+ T-helper cell accumulation and inverted CD4/CD8 ratios in affected tissues.

High concentrations of cytokines (IL-2, IL-6, TNF-α, IFN-γ) favour the development of granuloma. These are immunologic pathways which play a central role in the pathogenesis of sarcoidosis.

Pathogenesis and Histopathology of Sarcoidosis

The pathology of sarcoidosis is characterised by an over-response of the immune system, which results in the production of compact noncaseating granuloma in tissues. Granulomas are composed of epithelioid histiocytes and giant cells.

The pathology of sarcoidosis is characterised by the dysregulated immune response, resulting in the appearance of distinct noncaseating granulomas, which are the key features of the disease and may be localised to various organs.

  • Granuloma Formation: The characteristic lesion is the noncaseating epithelioid granuloma, with tight clusters of activated macrophages and Langhans-type giant cells. These do not have central necrosis, although there may be rare fibrinoid necrosis.

The presence of surrounding lymphocytes (primarily CD4+ T cells) and fibroblasts may ultimately result in fibrosis.

  • Cellular Details: Epithelioid histiocytes release enzymes and cytokines, such as ACE, lysozyme, and calcitriol. The overproduction of calcitriol may lead to hypercalciuria and hypercalcemia.

Giant cells are the result of fusion and may include Schaumann or asteroid bodies- nonspecific but supportive findings.

  • Organ Involvement: Granulomas can affect almost any organ, most commonly the lungs and intrathoracic lymph nodes (up to 90%). They may also affect skin, eyes, heart, liver, spleen, bone marrow, and nervous system, affecting normal tissue (e.g., fibrosis in lungs, arrhythmias in heart).
  • Pathological Variants: Granulomas appear in skin lesions (e.g., lupus pernio), but acute sarcoidosis (Löfgrens syndrome) may have erythema nodosum without granulomas. Fibrosis is present in chronic disease, and granulomas in neural tissue in neurosarcoidosis.
  • Non-Specific Findings: Granulomas can increase the ACE levels and lead to hypercalcemia. Pulmonary granulomas and lymphadenopathy tend to be seen with imaging.

Histopathology of sarcoidosis must be interpreted with caution. Since granulomas can be caused by a large number of diseases (e.g. tuberculosis, fungal infections, lymphoma), the most important diagnostic measure is to rule out other causes.

Special stains for acid-fast bacilli and fungi should be negative in sarcoidosis, confirming the granulomas are noncaseating and not due to infection.

Clinical Manifestations or Symptoms of Sarcoidosis

Sarcoidosis symptoms can vary widely depending on the organ affected, and most patients have no symptoms. Respiratory (dry cough, dyspnea), skin (erythema nodosum, lupus pernio), eye (uveitis), and constitutional (fatigue, fever) symptoms are common. Multisystem disease may cause weight loss and lymphadenopathy.

Patients with sarcoidosis may present with any combination of the following features:

  • Respiratory: Mostly impacts the lungs with a result of dry cough, chest pain, and increasing dyspnea. The test can be normal, but bilateral hilar lymphadenopathy is usually seen on imaging. Chronic disease may lead to fibrosis and respiratory failure.
  • Constitutional: Other non-specific symptoms are fatigue, low-grade fever, night sweats, and weight loss. Fever, hilar adenopathy, erythema nodosum, and polyarthritis (Löfgren syndrome) have a good prognosis and generally resolve.
  • Skin: Prevalence of approximately 10 -35%. Involves erythema nodosum and lupus pernio, together with papules or nodules, which can have granuloma on biopsy.
  • Eye: Observed in as many as 50% cases. Involves uveitis, conjunctivitis and copious tears, in which the eyes exhibit signs of redness, pain, and vision alterations. The untreated cases may result in cataracts or glaucoma.
  • Lymphatic: Lymphadenopathy usually occurs, including hilar and peripheral nodes. In systemic disease, splenomegaly and hepatomegaly could be present.
  • Musculoskeletal: It may involve arthralgia or arthritis (usually ankle) and bone lesions. Sarcoid arthritis is generally acute and migratory. Lytic lesions may be rarely caused by granulomas in bone.
  • Cardiac: Cardiac sarcoidosis can either present as palpitations, syncope or heart failure because of granulomatous infiltration of either the myocardium or conduction system. Arrhythmias and heart block are deadly complications; severe cases of these situations require an implantable defibrillator.
  • Nervous System (Neurosarcoidosis): Neurologic involvement may include cranial neuropathies (facial nerve palsy in particular), aseptic meningitis, seizures, or hypothalamic/pituitary dysfunction (resulting in diabetes insipidus). There is also a report of psychiatric symptoms (depression, anxiety).
  • Kidneys/Metabolic: Granulomas may produce excessive 1,25-dihydroxyvitamin D, leading to hypercalcemia and hypercalciuria. Patients can get kidney stones or nephrocalcinosis. Renal sarcoidosis (granulomatous nephritis) is rarer.
  • Others: Parotid gland enlargement (Heerfordt’s syndrome), central diabetes insipidus, and other organ-specific symptoms occur. Nonspecific constitutional features (malaise, fever of unknown origin) are seen in some patients.

Risk Factors and Epidemiology of Sarcoidosis

The incidence of sarcoidosis depends on the population. African Americans and individuals of Scandinavian or Irish ancestry have the greatest risk. The average age of onset is 20-50 years. The involvement of organs varies in women and men. There are no lifestyle factors that are conclusively shown to cause sarcoidosis; thus, prevention cannot be done.

Sarcoidosis shows distinct patterns across populations, with risk influenced by demographic and genetic factors rather than modifiable lifestyle behaviours. This makes prevention challenging, as highlighted in the key risk factors summarised below:

FactorEffect on Sarcoidosis Risk
Age (20–40 years)High risk (peak incidence)
GenderSlight female predominance
RaceMost common in African Americans; Caucasians have lower prevalence; high prevalence in Scandinavia/Japan
GeneticsFamilial clustering; HLA associations (e.g. DR alleles)
Environmental ExposuresImplicated (beryllium, mould), but not proven causes
Lifestyle (Smoking)Not protective; no lifestyle prevention known

Diagnosis of Sarcoidosis

The diagnosis involves a compatible clinical and radiological image and histological findings of noncaseating granulomas, and ruling out other etiologies. The most important are chest imaging (bilateral hilar lymphadenopathy or interstitial disease), supportive laboratory findings (elevated ACE, calcium), and confirmatory biopsy (granulomas without infection).

Diagnosis of sarcoidosis is based on 3 criteria: 

  1. Clinical and radiologic findings consistent with sarcoidosis, 
  2. Histopathologic evidence of noncaseating granulomas in at least one organ, and 
  3. Exclusion of alternative diagnoses (especially infections and malignancies).

The workup typically involves:

1. Imaging Studies

  • Chest X-ray: The classical observation is bilateral hilar lymphadenopathy (BHL), which is evident in most patients. Interstitial lung infiltrates (reticular or nodular patterns) may also be found. Scadding’s stages of sarcoidosis (0–IV) describe CXR progression.

The following tables describe the stages based on X-ray findings:

StageChest X-ray Findings
IBilateral hilar adenopathy only
IIBilateral hilar adenopathy + diffuse lung opacities (interstitial infiltrates)
IIIDiffuse lung opacities alone (hilar nodes regressing)
IVAdvanced fibrosis (reticular/fibrotic changes)
  • High-Resolution CT (HRCT): Gives additional detail; presents micronodules along bronchovascular bundles, fibrosis, and predominance in the upper lobes. In the case of a normal chest X-ray, HRCT is able to identify parenchymal disease.
  • Other Imaging: In case of particular organ involvement, imaging is guided: MRI (brain MRI or heart MRI in case of CNS/cardiac sarcoid), PET scans or Gallium scans to identify some occult inflammation, and so on.
  • Radiographic Staging (Scadding System): The appearances of the chest X-ray are classified into stages that represent the severity of the disease. The staging has a role in prognosis and management.

2. Pulmonary Function Tests (PFTs) 

Most pulmonary sarcoidosis produces a restrictive pattern (reduced total lung capacity, normal or elevated FEV₁/FVC ratio) and reduced diffusing capacity (DLCO). Approximately 10% may show an obstructive component. Reduction in DLCO and exercise desaturation can be used to assess pulmonary hypertension.

3. Laboratory Tests

  • Serum Angiotensin-Converting Enzyme (ACE): Increased in most sarcoidosis patients, indicating granuloma burden. However, ACE has limited sensitivity/specificity. It may serve to aid diagnosis or track activity.
  • Calcium and Vitamin D: Granulomatous production causes hypercalcemia (2-7% of patients) and increases 1,25-dihydroxyvitamin D. Hypercalciuria is more common. The routine check of serum calcium, creatinine, and urinalysis is performed.
  • Other Markers: An increase in alkaline phosphatase could be indicative of hepatic granulomas. Non-specific markers of inflammation (ESR, CRP) can be raised. Serologic tests like ANA or RF may be done to exclude other connective tissue diseases.
  • Tuberculin (PPD) Test: Often negative in sarcoidosis due to anergy. A positive PPD suggests latent TB (and may coexist or mimic sarcoid).

4. Biopsy
A tissue biopsy demonstrating noncaseating granulomas is essential for a definitive diagnosis. The biopsy site is chosen based on accessibility and clinical involvement:

  • Lymph Node Biopsy: In case of peripheral lymphadenopathy, an excisional node biopsy is performed. Transbronchial biopsy or mediastinoscopy can be used to sample mediastinal nodes.
  • Lung Biopsy: Granulomas in pulmonary sarcoidosis are frequently found on transbronchial lung biopsy (via bronchoscopy). Surgical lung biopsy (video-assisted thoracoscopic biopsy) is rarely needed if other sites are uninformative.
  • Skin Biopsy: Easy for cutaneous lesions (especially papules or plaques). The conjunctival or lacrimal gland biopsy can also be done in case of ocular involvement.
  • Other Sites: If these organs show abnormalities, liver, spleen, or nerve biopsies can be performed.

The following table summarises the key pathological findings and important differential diagnoses to consider when evaluating suspected sarcoidosis:

CategoryCondition / FindingKey FeaturesHow to Differentiate / Rule Out
Key Pathology FindingNoncaseating epithelioid granulomasMacrophages (epithelioid histiocytes), giant cells and lymphocytes; no necrosis; no organisms on stain.Confirm with biopsy; ensure absence of infection using special stains (AFB, PAS, GMS)
Infectious CausesTuberculosis & atypical mycobacteriaCaseating granulomas are more common; systemic symptoms like fever and weight loss are also present.AFB stain, culture, and PCR for mycobacteria
Fungal infections (Histoplasmosis, Coccidioidomycosis)Sarcoidosis may look like granulomas; an endemic history of exposure.PAS, GMS stains; fungal cultures/serology
Occupational DiseaseBerylliosisSimilar granulomas; history of beryllium exposure (industry-related)Exposure history, beryllium lymphocyte proliferation test
MalignancyLymphoma / metastatic cancerLymphadenopathy, systemic symptomsBiopsy with malignant cells (not granulomas)
Autoimmune / VasculitisGranulomatosis with polyangiitisNecrotising granulomas, vasculitis, renal involvementANCA testing, biopsy showing vasculitis
Interstitial Lung DiseasesHypersensitivity pneumonitisExposure-related, diffuse lung involvementHistory of antigen exposure, imaging patterns
Idiopathic pulmonary fibrosisProgressive fibrosis without granulomasHRCT pattern (UIP), no granulomas.
Other CausesCat-scratch diseaseInfectious granulomas, lymphadenopathySerology for Bartonella
Foreign body reactionGranulomas around foreign materialHistory, biopsy showing foreign material

Treatment and Management of Sarcoidosis

Many cases of sarcoidosis are mild and self-limited, requiring only observation. Corticosteroids are used as the main therapy to treat symptomatic or progressive disease. Chronic or refractory cases are treated with steroid-sparing agents (methotrexate, azathioprine).

The sarcoidosis treatment depends on disease severity, organ involvement, and symptoms. These principles are mainly to treat patients with organ-threatening/severe disease and monitor those with mild, asymptomatic involvement. Key points include:

  • Observation: In asymptomatic or limited disease (e.g., Stage I), observation without treatment is appropriate. Approximately two-thirds spontaneously remit in 2-3 years. Follow-up is frequent, which involves clinical examination, chest X-rays, and pulmonary function tests.
  • Corticosteroids: Systemic corticosteroids (e.g., prednisone) can be used as first-line treatment of active disease. Recommended in symptomatic pulmonary disease or severe extrapulmonary progression (ocular, cardiac, CNS, hypercalcemia, renal).
  1. Dosage: Typically starts at 20–40 mg prednisone daily (≈ 0.3 — 0.6 mg/kg). In 4-6 weeks, the response is again checked, and the dose is reduced to maintenance (10-20 mg/day). Depending on the response, treatment can last from 6 months to 1–2 years.
  2. Response and Monitoring: Signs of improvement include relief of symptoms, improved imaging, and normalised labs. Tapering frequently results in relapses, and treatment is balanced to control the disease and reduce steroid toxicity.
  • Steroid-Sparing Agents: In cases of intolerance to steroids or in the case of chronic treatment, other immunosuppressive agents are used:
  1. Methotrexate: A folate antagonist that suppresses immune activity. The most typical dose ranges between 10 and 20 mg per week. Methotrexate is prescribed to treat lung, skin, and joint disease and is commonly the initial steroid-free treatment option.
  2. Azathioprine: A substitute antimetabolite used in some cases where methotrexate is contraindicated.
  3. Leflunomide: A less commonly used alternative to methotrexate.
  4. Hydroxychloroquine: Useful in hypercalcemia, skin lesions, arthritis and mild disease.
  5. Mycophenolate mofetil: An additional alternative in refractory cases.
  • Biologic Agents: Biologic therapies with TNF-α have been tried in refractory or life-threatening instances (e.g. severe cardiac or neurosarcoidosis):
    1. Anti-TNF Therapy: Infliximab (IV) and adalimumab (SQ) block tumour necrosis factor-α, a cytokine central to granuloma formation. They have demonstrated their use in chronic sarcoidosis, in which the conventional agents are not effective.
    2. Others: New treatments encompass monoclonal antibodies against IL-6 or IL-12/23, which are experimental.
  • Organ-Specific Management:
    1. Ocular: Uveitis and ocular inflammation are treated with topical (eye drops) and/or systemic steroids to avoid loss of vision. Consultation in ophthalmology is necessary.
    2. Cardiac: Systemic steroids are initiated in case of cardiac involvement; pacemaker or defibrillator implantation may be required in arrhythmias.
    3. Neurosarcoid: Methotrexate or infliximab may be used in combination with high-dose steroids. Involvement of neurology is typically required.
    4. Hypercalcemia: Hydration and steroids (or antimalarial drugs) to reduce vitamin D activation and lower calcium.
  • Supportive Care:
    1. Pulmonary Rehabilitation: Exercise can help manage breathlessness.
    2. Eye and Heart Monitoring: It is recommended that regular ECGs and ophthalmologic exams, even in asymptomatic patients, be conducted because of the risk of silent involvement.
    3. Lifestyle: Patients are to avoid tobacco and sun exposure (to reduce calcium photosynthesis). Immunosuppressive therapy requires vaccinations (flu, pneumococcal).

Complications and Prognosis of Sarcoidosis

Sarcoidosis has a favourable prognosis; lots of patients experience spontaneous remission. Chronic disease, however, may lead to serious problems. The most dreaded are pulmonary fibrosis and hypertension, loss of sight, heart block, and brain impairments. In untreated or severe cases, mortality ranges from 3-5%.

Sarcoidosis is usually prognostically favourable, depending on the severity of the disease, the organ involvement, and timely treatment, with a probability of chronic complications in some patients:

  • Outcomes: Approximately 60-70% achieve remission in 2-5 years, particularly in Löfgren syndrome. Beyond 2-3 years, the disease is more likely to be chronic.

The majority of chronic cases result in mild-moderate disability, with permanent damage, which occurs in 10-12% of cases. Life expectancy is typically normal with low mortality (1-5%).

  • Pulmonary Complications: Chronic disease can lead to lung fibrosis, bronchiectasis and progressive respiratory failure. Pulmonary hypertension may develop, and end-stage disease may need lung transplants.
  • Cardiac: Additional concerns include myocardial involvement, cardiomyopathy, arrhythmias, and heart block, followed by a risk of sudden cardiac death.
  • Ocular: Unchecked chronic uveitis can lead to glaucoma, cataracts or vision loss.
  • Neurologic: Neurosarcoidosis may lead to meningitis, seizures, hydrocephalus or persistent cranial nerve palsies with potential irreversible deficits.
  • Other Complications: May involve the liver, hypercalcemia-induced kidney stones, and steroid-induced diseases such as osteoporosis, diabetes, and infections.
  • Mortality: Sarcoidosis rarely causes death, with the total mortality in untreated patients approximated at 3–5%. When it happens, it is normally the result of respiratory failure, cardiac complications or immunosuppressed infections.

FAQs sbout Sarcoidosis

  1. What is sarcoidosis?

Sarcoidosis is an inflammatory systemic disease that is characterised by noncaseating granulomas. It is most likely to hit the lungs (bilateral hilar lymphadenopathy) and can include the skin, eyes, heart, and other organs. Its cause is not known, and it has no definite cure.

  1. What causes granuloma formation?

Granulomas are the consequence of a hyper-immune reaction consisting of T cells and macrophages. This is driven by cytokines (TNF-α, IFN-γ, IL-2). Possible triggers include environmental antigens, infections, and genetics, though none are proven.

  1. How is sarcoidosis diagnosed?

Diagnosis involves biopsy of noncaseating granulomas without necrosis or infection (negative AFB/fungal stains) and clinical and radiological correlation to exclude others.

  1. What is Löfgren’s syndrome?

A mild acute sarcoidosis is characterised by a fever, bilateral hilar lymphadenopathy, erythema nodosum, and usually ankle arthritis. It prognoses very well and normally heals in 6-24 months.

  1. What lab abnormalities are seen?

There are increased ACE, hypercalcemia, and occasionally dysfunctional liver enzymes. Blood samples can be associated with mild anaemia or leukopenia.

  1. What are the main treatments?

Corticosteroids (e.g., prednisone) are used as the first-line treatment. In severe cases or cases resistant to treatment, immunosuppressants (methotrexate, azathioprine) or biologics (e.g., infliximab) are added. Mild cases might only require observation.

  1. What is the prognosis?

In mild and acute cases, about 60-70% achieve remission. Chronic disease may cause organ damage in 10–20%. The overall mortality is low (1 to 5%), and cardiac or neurologic involvement aggravates the outcomes.

  1. Can sarcoidosis be prevented?

No. The reason is not known, and this is impossible to prevent. General lung health might be improved by avoiding irritants such as smoke or dust, but it cannot prevent disease.

  1. What tests and imaging are used?

Primary tools are chest X-ray and CT. PET scans, MRI (heart/brain), pulmonary function, etc., assist in the determination of the extent and severity. Biopsy remains confirmatory.

  1. How often is monitoring needed?

Follow-up (after 3 to 6 months) is recommended with clinical examination, imaging, and lung tests. Eye tests and ECGs (electrocardiograms) are recommended due to potential silent involvement.

Conclusion

Sarcoidosis is a systemic inflammatory disease which is based on noncaseating granuloma and has an ambiguous aetiology. The topic is significant to NEET-PG because of its unique pathology, diverse manifestations, and a clear approach to diagnosis and treatment (corticosteroids and immunosuppressants).

DocTutorials help students use advanced technology and learning methods to grasp the syllabus effectively. Our online video lectures, Qbanks, exam-focused edition notes, flashcards, and mind maps help them practice strategically and prepare for exams.

Join DocTutorials today and explore our NEET PG course to excel in your medical career.

NEET PG Online Live Power Pack
DocTutorials App Download Now

Latest Blogs

Intermittent Explosive Disorder: Causes, Symptoms, and Treatment

Intermittent_Explosive

Intermittent Explosive Disorder (IED) is an impulse-control disorder characterised by unexpected aggressive outbursts (verbal or physical). Episodes can include yelling, throwing, or physical assault, usually accompanied by relief or remorse, and can interfere with social and occupational functioning.

It typically starts during childhood or adolescence (age ≥6) and can improve over time. The behaviour is unplanned, disproportionate and impulsive; it is not due to a different disorder. Keep reading to know more about IED.

What are the Causes of Intermittent Explosive Disorder?

IED is probably caused by the interaction between genetically susceptible personality, particularly brain differences with serotonin, and environmental stressors such as maltreatment. The combination of all these factors can lead to the inability to control anger and aggression.

The aetiology of IED is multifactorial, involving genetic, neurobiological, and environmental factors. It is argued that inherited traits and brain chemistry are key factors:

  • Genetic Factors: A strong genetic component is exhibited by family and twin studies. Impulsive aggression is approximately 45-50% hereditary, and a first-degree relative with IED is approximately a threefold risk factor. The overall genetic contribution is between 28-45% (verbal aggression and aggression towards others).
  • Neurobiological Factors: IED reveals chemical and brain changes. Impulsive aggression has been associated with low serotonin (5-HT), fronto-limbic grey matter and increased amygdala reactivity. Serotonin dysfunction is the most consistent finding.
  • Environmental Factors: Childhood experiences play a significant role in the risk of IED. The probability of subsequent abuse, trauma, violence, chronic stress or family conflict is enhanced by exposure to abuse, trauma, violence, chronic stress or family conflict.

What are the Risk Factors of Intermittent Explosive Disorder?

Intermittent Explosive Disorder (IED) has risk factors that predispose it. It affects more men and normally starts in childhood or adolescence, with few new cases after 40. Risk factors include family history, exposure to violence in childhood, exposure to violence, co-morbid conditions, and other factors.

Causes refer to aetiology, whereas risk factors are those attributes that relate to an increased risk of developing IED. Major risk factors are:

  • Gender: IED rates are higher among males. Impulsive acts of aggression are more prevalent in men and boys than in females.
  • Age: Onset often occurs in childhood or adolescence; symptoms peak in the second decade of life. After 40 years, new cases are uncommon.
  • Family History: Family history of IED or impulse-control disorders increases risk.
  • Childhood Trauma: A history of childhood abuse (physical/verbal) or witnessing violence strongly predisposes one to IED.
  • Psychiatric Comorbidity: Comorbid mental disorders, particularly impulsivity or aggressive ones, are risk factors. These include:
  • Attention-Deficit/Hyperactivity Disorder (ADHD).
  • Conduct Disorder or Oppositional Defiant Disorder (particularly in youth).
  • Personality Disorders (e.g. antisocial, borderline, narcissistic).
  • Substance use disorders (alcohol, drugs) – both a risk and a common co-occurrence.
  • Personality Traits: Traits like impulsivity, hostility, and poor anger control (even without a formal disorder) predispose to IED.

What are the Symptoms of Intermittent Explosive Disorder?

IED patients experience unpredictable, brief flashes of intense anger or violence, which may lack obvious causes. Outbursts are disproportionate and can involve yelling, aggression, or property damage, accompanied by physical arousal such as a racing heart. Between episodes, they appear normal.

The 7 signs of intermittent explosive disorder include:

  1. Aggressive Outbursts: Verbal (shouting, insults, threats) or physical (hitting, slapping) aggressive behaviour.
  2. Impulse-driven: The aggression is impulsive, not pre-planned or used for secondary gain. Patients frequently report experiencing an accumulation of tension that bursts out.
  3. Destructive Behaviour: The episodes may lead to property damage or assault.
  4. Ouburst Duration: The outbursts are usually less than 30 minutes. Frequency can vary: some people experience multiple episodes within a week; others have months between episodes.
  5. Emotional Cycle: Patients usually experience irritability, tension or an energy surge just before an outburst.
  6. Physical Symptoms: The physical symptoms are rapid heart rate, shaking, heat flushes or tightness in the chest.
  7. Repentance after Outburst: They often feel remorse, guilt or embarrassment.

Examples of behaviours (episodes) include:

  • Yelling/screaming (often profanely)
  • Intense arguments and temper tantrums
  • Threatening gestures or menacing postures
  • Road rage, violence toward strangers or family members
  • Punching walls, breaking dishes or furniture
  • Slapping, pushing, or kicking others
  • Threatening weapons or verbally assaulting others
  • Physical fights or sexual/ domestic assaults
  • Sexual or romantic jealousy outbursts (less common)

Physical/emotional signs during outbursts:

  • Sudden increase in energy or adrenaline (“rush”)
  • Racing heart, palpitations, chest tightness
  • Trembling or shaking hands
  • Headache
  • Tingling or hot flush sensation
  • Feeling out of control or detached

Feelings of relief and exhaustion are common after an episode, but guilt or remorse are also common. Most individuals who have IED are aware of their excessive response and might apologise when they calm down. Yet, they can do little to prevent the next outburst without assistance.

In NEET PG Psychiatry, keep in mind that IED disorder episodes are brief, impulsive, and remorseful. This assists in differentiating between IED and planned aggression or between chronic anger disorders. The presence of remorse and episodic nature are characteristic.

What is the Diagnosis of Intermittent Explosive Disorder?

Intermittent Explosive Disorder (IED) is a clinically diagnosed disorder under DSM-5 or ICD-11 criteria, as a recurrent, disproportionate, impulsive, explosive outburst. No lab tests are available; diagnosis is based on history, pattern of episodes, and ruling out medical, substance-related, or other psychiatric etiologies.

The diagnosis of IED disorder is carried out according to clinical criteria (DSM-5 or ICD-11) and episode pattern. There are no laboratory tests; it relies on a thorough history and ruling out other causes.

Key DSM-5 criteria include recurrent impulsive aggressive outbursts (verbal or physical) that are grossly out of proportion to triggers. Specifically:

Either,
A. Minor Outbursts: Verbal or short-term physical aggression at least 2 times a week during 3 months, causing no serious harm, or,
B. Major Outbursts: 3 outbursts in a year, resulting in property damage or physical assault on others.

  • The aggression is impulsive or anger-based, not premeditated for gain.
  • Outbursts result in significant distress or social/occupational dysfunction.
  • The patient is at least 6 years old (or at the developmental level).
  • The behaviours cannot be attributed to other psychiatric disorders (e.g. not just in bipolar mania or substance withdrawal).

ICD-11 criteria involve recurrent short spells of verbal or physical aggression and lack of impulse control and outbursts that are evidently disproportional to provocation.

IED is not diagnosed when aggression is attributed to other disorders (e.g. adjustment disorder, bipolar disorder, ASD or conduct/ODD in youth).

Diagnostic Workup

  • Clinical Interview: Evaluate frequency, nature, and circumstances of outbursts. Take patient history, family/friend history.
  • Medical Evaluation: Eliminate neurological or medical conditions (e.g. brain tumours, head injury, dementia, thyroid problems, hypoglycemia) that may result in aggression.
  • Substance Use: Screen for intoxication/withdrawal from alcohol or stimulants, as these can mimic or exacerbate IED.
  • Psychiatric Differential: Rule out mood disorders (particularly bipolar), PTSD, personality disorders, ADHD, conduct disorder, ODD and substance use disorders. These may co-exist with IED, but the diagnosis of aggression must be excessive compared to that of the other disorder.
  • Severity Assessment: Aggression level can be determined using tools such as the Life History of Aggression Scale or anger questionnaires (primarily in research).

The table below shows the major differences in the DSM-5 and ICD-11 diagnostic criteria of Intermittent Explosive Disorder (IED):

Criterion / AspectDSM-5 (312.34)ICD-11 (6C73)
Core DefinitionFrequent outbursts of aggression are caused by the inability to suppress.Frequent short-term verbal or physical aggression or property damage as a result of impulsiveness.
Frequency Threshold≥2 minor outbursts/week for ≥3 months OR ≥3 major outbursts/year.None based on a particular numerical limit; characterised by a pattern of repeated outbursts.
IntentAnger-driven/impulsive (no external gain, such as money or power).Episodes of anger that are grossly out of proportion to stress.
ExclusionsFailure to be better explained by some other disorder or substances; age 6 or older.None of the other mental/neurodevelopmental disorders explains it; it is not included in the chronic anger pattern.

What is the Treatment for Intermittent Explosive Disorder?

Successful management of IED often incorporates medications and psychotherapy. The aim is to decrease outbursts and severity and enhance impulse control. The first-line treatment is Cognitive-Behavioural Therapy (CBT) and other psychotherapies that are typically used in combination with pharmacotherapy to normalise mood and aggression.

IED is managed through a mixture of psychotherapy and medications to help decrease the impulsive aggression and enhance emotional control. Here are the treatment options for IED disorder:

1. Non-pharmacological Treatment

  • Cognitive-Behavioural Therapy (CBT): CBT for anger management is the cornerstone. It assists the patients in identifying triggers, developing coping skills and altering hostile thinking. 

Research demonstrates that anger, hostility, and impulsivity can be reduced within minutes and over about 12 weeks with the aid of relaxation, cognitive restructuring, coping, and relapse prevention.

  • Anger Management Programs: These are planned programs (often conducted in groups) that concentrate on impulse control, communication skills, and conflict management.
  • Family Therapy or Education: The use of family involvement can help to enhance the dynamics and support. Incidents can be minimised by teaching communication and de-escalation techniques.
  • Stress Reduction and Lifestyle: Regular physical activity, sleep, and stress management (e.g. meditation) can help to decrease impulsivity. Treatment may be facilitated by lifestyle changes such as a balanced diet, good sleep hygiene, and substance avoidance, but these are all adjunctive.

2. Pharmacotherapy

There are no FDA-approved, specifically IED-reducing drugs, though many medications are used off-label to minimise aggression:

  • SSRIs (Selective Serotonin Reuptake Inhibitors): First-line medication class. Fluoxetine is best supported: A placebo-controlled trial showed that it significantly reduced the number of aggressive outbursts.

Other SSRIs (citalopram, sertraline) are also prescribed. The way SSRIs work is by raising brain serotonin, which is normally low in IED.

  • Mood Stabilisers / Anticonvulsants: These are particularly applied where mood swings or impulsivity are high. Options include:
    • Lithium: Evidence of decreasing aggression.
    • Carbamazepine & Oxcarbazepine: Are capable of decreasing impulsive aggression. Oxcarbazepine, e.g., was identified as decreasing total, verbal, and object-directed aggression.
    • Valproate (divalproex): It was previously in use, but it was found to be ineffective in the case of IED with some side effects.
    • Phenytoin: Minimal evidence indicates that it could potentially decrease impulsivity (used in some studies).
  • Antipsychotics: A typical antipsychotic (e.g. risperidone) can be used in cases of severe aggression, though this is less convincingly supported. They do not have a direct role in IED alone.
  • Anxiolytics (e.g. benzodiazepines) are not recommended because they can lead to dependence and may cause disinhibition. The extreme cases may include short-term use.

There are some reports of buspirone or beta-blockers being used to help with anger, although they are not routine. The following table describes a probable prescribed medication:

Medication ClassExamplesNotes/Effects
SSRIs (Antidepressants)Fluoxetine, Sertraline, EscitalopramMost researched class; enhances serotonin, and impulsive aggression diminishes. It can take approximately 2-3 months to take effect.
Mood stabilisers / AnticonvulsantsLithiumCarbamazepine, OxcarbazepinePhenytoinLithium is effective at decreasing aggression (observed levels); oxcarbazepine decreases aggressive acts; valproate is ineffective.
AntipsychoticsRisperidone, QuetiapineConsider for refractory cases with severe aggression; evidence is limited.
AnxiolyticsNone routinely recommended(Minimal relaxation of anxiety but disinhibition and dependency risk).

What are the Prevention Strategies for Intermittent Explosive Disorder?

There is no established way of totally preventing IEDs. Nevertheless, severity and better results can be alleviated by early management and targeted control of risk factors. Strategies concentrate on education, early therapy and control of related conditions.

IED disorder prevention is aimed at early treatment and not necessarily a cure. Upon the detection of symptoms or comorbidities, timely assessment and therapies such as CBT (Cognitive Behavioural Therapy) may reduce the risk and avoid progression, particularly among young people.

  • Early Identification: Careful identification of potentially at-risk youth (e.g., having ADHD or conduct problems, abused in the past) and the administration of interventions (anger management training, counselling) could aid in avoiding the transition to the full-blown IED level.
  • Treatment of Comorbidities: The presence of aggressive or impulsive symptoms should not be overlooked; early intervention in conditions such as ADHD or substance abuse can decrease the risk of IED.
  • Family Support: Families with a history of violence or IED should be offered support, parenting classes, and stress management, as this can make the situation more stable.
  • Anger Management Education: Impulse control could be enhanced by teaching children and adolescents frustration-coping skills (e.g., deep breathing, time-outs, communication).
  • Avoiding Substance Abuse: Avoiding alcohol/drug abuse in individuals at risk is significant, as these substances may provoke or aggravate outbursts.
  • Community Programs: In high-risk populations, school or community interventions that educate on emotional regulation may be beneficial.

What are the Complications of Intermittent Explosive Disorder?

IED may contribute to severe psychosocial and legal issues. Recurring aggressive behaviours not only decrease quality of life but also may harm health, relationships, education and career. It is important to understand these complications to appreciate the importance of treatment.

Major complications include:

  • Psychosocial Impairment: Individuals with IED generally lack good social functioning as they have bonding difficulties and poor family life. This impacts work and school performance, exposure to job loss or discipline, and reduced quality of life.
  • Legal Problems: Impulsive aggression might result in criminal offences, such as assault, restraining order, or road rage DUI (Driving Under the Influence). The repeated outbursts can lead to imprisonment or a lawsuit due to property damage.
  • Physical Injuries: Outbursts can lead to self- or other-directed destructive behaviours, including cuts, bruises, or worse. Long-term anger may also lead to hypertension and other diseases related to stress.
  • Co-occurring Disorders: IED is frequently associated with conditions such as depression, anxiety, substance abuse, and other impulse-control disorders. It is also associated with increased prevalence of physical health conditions such as headache, heart disease and diabetes.
  • Suicidality: Self-harm and suicide risks are high in people with IED, so it is important to monitor suicidal intentions.
  • Long-term Consequences: IED may be chronic when left unattended. Although outbursts can decrease in the later years, long-term consequences such as legal matters and broken relationships can still persist.

Since IED disorder creates severe impairment, comparable to or greater than other psychiatric disorders, it is not taken lightly. Treatment not only seeks to prevent the outbursts, but also to avert these extreme implications in life.

FAQs about Intermittent Explosive Disorder

  1. What differentiates IED from normal anger?

IED includes repetitive, severe, and impulsive violence that is disproportionate to provocations, in contrast to common anger that is more restrained and context-specific.

  1. How common is IED?

The prevalence of IED disorder is relatively high; approximately 4-7% of individuals experience it at some point in their lives, more so in males and often in youth.

  1. At what age is IED diagnosed?

IED is diagnosed in people 6 years of age or older because small children can experience developmentally normal tantrums.

  1. What are the main symptoms of IED?

The main symptoms comprise abrupt verbal or physical outbursts, loss of control, and disproportionate reactions, with subsequent regret.

  1. What causes IED?

IED is caused by a set of genetic, neurobiological (e.g. serotonin malfunction), and environmental (such as childhood trauma) factors.

  1. How is IED diagnosed?

It is clinically diagnosed, focusing on recurrent impulsive aggression and excluding other causes, on the basis of DSM-5 or ICD-11.

  1. What is the first-line treatment for IED?

The first-line treatment is Cognitive-Behavioural Therapy (CBT) that may be used in combination with medication, such as SSRIs, to control the symptoms.

  1. How is IED different from ODD or conduct disorder?

IED is impulsive and episodic in nature, whereas ODD (Oppositional Defiant Disorder) and conduct disorder display consistent behavioural patterns, and they may involve planned aggression.

  1. Can IED be prevented?

Prevention is not certain; however, early intervention, treatment, and control of risk factors can diminish the severity.

  1. What are the key exam points about IED?

Key points to remember include impulsive, disproportionate aggression, diagnosis only in individuals aged 6 years or older, and the need to rule out other disorders. The initial treatment is Cognitive-Behavioral Therapy (CBT).

Conclusion

Intermittent Explosive Disorder is a chronic psychiatric disorder characterised by impulsive aggression outbursts. It is important for NEET-PG Psychiatry due to clear DSM-5/ICD-11 criteria, identifiable risk factors, and defined management (CBT and SSRIs).

To strengthen your understanding of topics like Intermittent Explosive Disorder in Psychiatry, DocTutorials can support your preparation. We offer structured exams, high-quality video lectures, Qbank, and clinical case questions in specific formats to suit NEET PG aspirants.

Join DocTutorials today and explore our NEET PG course to stay ahead in your medical career.

NEET PG Online Live Power Pack
DocTutorials App Download Now

Latest Blogs

NEET PG Online Live Power Pack
DocTutorials App Download Now