Proctitis: Causes, Symptoms, Diagnosis, and Treatment
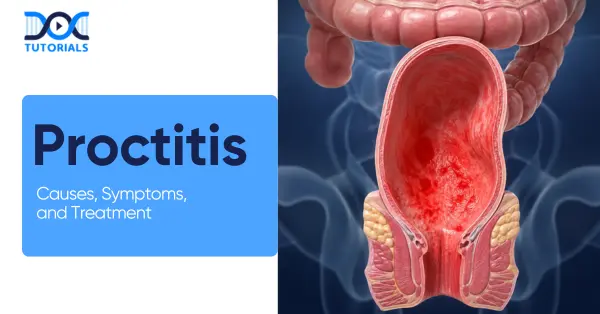
Proctitis is a disease caused by inflammation of the inner lining of the rectum, the last part of the large intestine. It is typically characterised by symptoms like pain in the rectum, bleeding, discharge, and an urge to pass stools that is often painful and disruptive to normal life.
The disorder can develop as a result of numerous causes, such as infections, inflammatory bowel diseases, radiation therapy, or autoimmune disorders. For medical students and aspirants, proctitis is an important topic that bridges clinical understanding with real-world patient management. Read on to learn in detail about this condition.
What is Proctitis?
Proctitis is inflammation of the rectal lining that disrupts normal bowel function and leads to symptoms such as pain, bleeding, and urgency. It commonly occurs due to infections, inflammatory bowel disease, or radiation exposure.
Proctitis refers to inflammation of the rectum, the final portion of the large intestine just before the anus. The term itself combines “procto,” meaning rectum, and “itis,” meaning inflammation.
The condition occurs when the inner lining of the rectum is irritated by infections, inflammatory bowel disease (IBD), radiation, or other chemical or bacterial triggers. The rectum helps pass stool, so any inflammation can significantly affect normal bowel function.
The symptoms of proctitis may include rectal pain, diarrhoea, bleeding, rectal discharge, and a persistent urge to pass stool. The symptoms can be either short-lived or chronic.
It is usually found in people with inflammatory bowel disease, including ulcerative colitis or Crohn’s disease, and can also be a side effect of radiation therapy or as a result of sexually transmitted infections.
What are the Causes of Proctitis?
Proctitis can result from infections, IBD such as ulcerative colitis, radiation therapy, or antibiotic-induced gut imbalance. Other causes include surgical changes, food protein sensitivity in infants, and eosinophilic infiltration.
A variety of conditions, medical treatments, and external factors can lead to the development of proctitis. These include:
Inflammatory Bowel Disease (IBD): Rectal inflammation is observed in almost 30% of patients with IBD. It is seen more frequently in people with ulcerative colitis compared to those with Crohn’s disease.
Infections: Sexually transmitted infections (STIs) are one of the most frequent causes, particularly among people who have anal intercourse. These are gonorrhoea, genital herpes, monkeypox, and chlamydia. Also, Salmonella, Shigella, and Campylobacter are possible foodborne infections associated with proctitis.
Antibiotic Use: Some antibiotics used to treat infections may disrupt healthy gut bacteria. This could result in the proliferation of harmful bacteria, such as Clostridioides difficile, in the colon and rectum, leading to inflammation.
Surgical Procedures: Diversion proctitis may develop after specific surgeries involving the colon or small intestine. In such cases, stool is rerouted away from the rectum to an opening created surgically, known as a stoma.
Food Proteins: Proctitis in infants may result from an allergy to proteins present in cow milk or soy-based formula. Breastfed infants may also be affected if the mother consumes dairy products.
White Blood Cell Accumulation: Eosinophilic proctitis occurs when eosinophils, a type of white blood cell, build up in the rectal lining. This condition is more commonly observed in children under the age of two.
What are the Risk Factors of Proctitis?
Risk increases with unsafe sexual practices, multiple partners, and lack of protection during intercourse. Patients undergoing pelvic radiation therapy are also at higher risk of developing rectal inflammation.
Certain factors can increase the likelihood of developing proctitis:
Sexual Activity: Proctitis is also prone to being triggered by sexual activity that increases the risk of STIs. This includes having multiple sexual partners, practising anal intercourse, not using protection such as condoms, or having a partner diagnosed with an STI.
Radiation Therapy for Cancer: Radiation around the rectum or prostate can cause rectal inflammation. Proctitis caused by radiation can start during therapy and last weeks or months later, or it can manifest years later.
What are the Symptoms of Proctitis?
The common symptom of proctitis is tenesmus, a constant urge to pass stool even after evacuation. Patients may also experience rectal pain, bleeding, mucus discharge, diarrhoea, or constipation.
The symptoms of proctitis can vary slightly depending on the underlying cause. The most common symptom is tenesmus, which refers to a constant and uncomfortable urge to defecate. This sensation often continues even after a bowel movement.
Other proctitis symptoms may include:
Blood present in the stool or bleeding from the anus
Pain in the rectum, abdomen, or anal region
Discomfort or pain during bowel movements
Mucus or discharge from the anus
Loose and watery stools or diarrhoea
Constipation
Swollen lymph nodes in the groin
Anyone experiencing symptoms such as anal discharge, bleeding, or persistent pain should consult a doctor without delay.
How is Proctitis Diagnosed?
Diagnosis involves a clinical history, physical examination, and rectal evaluation using digital exam or anoscopy. Confirmatory tests include stool studies, blood tests, and endoscopic procedures like sigmoidoscopy or proctoscopy.
Healthcare professionals begin by inquiring about your symptoms and subsequently conduct a physical exam of the rectum to examine evidence of proctitis. This check-up typically involves rectal examination and anal inspection.
In case of suspected proctitis, the provider will ask additional questions to learn more about the potential cause and the type of condition. These may include:
Medications you have taken recently.
Whether you have a family history of autoimmune diseases.
Whether you have had unprotected sex or contact with unscreened partners.
Whether you have recently travelled abroad.
Based on your answers and the initial findings, the provider will decide which further tests are necessary. Tests may include:
Blood Test: A blood test can help identify infections or other conditions that can cause proctitis. It can also exhibit indicators of blood loss or increased white blood cell counts.
Stool Test: A stool sample can be tested to confirm an infection, bleeding, or an excess of white blood cells.
Rectal Culture: In this test, the healthcare provider collects a sample from the inside of the rectum using a cotton swab. This sample is then cultured to identify bacteria or viruses.
Proctoscopy: This is done when the inside of the rectum is examined with a short and rigid endoscope. The proctoscope consists of a hollow tube that is fitted with a light and a camera. If required, instruments can be passed through it to collect a tissue sample for biopsy.
Flexible Sigmoidoscopy: A slightly longer, flexible scope may be used to examine the rectum and the lower part of the colon (sigmoid colon).
This helps determine colon involvement, which may indicate inflammatory bowel disease or a gastrointestinal infection. The procedure typically requires bowel preparation beforehand.
What are the Treatment Options for Proctitis?
Treatment for proctitis depends on the underlying cause and may include antibiotics, antivirals, or anti-inflammatory drugs. Chronic cases like IBD require long-term immunomodulators, corticosteroids, and lifestyle modifications.
The most appropriate treatment for proctitis largely depends on its underlying cause. In acute inflammation, targeted therapies may directly resolve the condition. Nonetheless, where proctitis is associated with a chronic disease, treatment will tend to be a mix of drugs as well as long-term changes to both the diet and lifestyle.
Infections
When an infection is identified as the cause, treatment focuses on eliminating the specific pathogen. Medications are usually prescribed by doctors based on the kind of infection. Antibiotics are used to treat bacterial infections, including sexually transmitted infections (STIs), and antiviral medications are used to treat viral infections, such as genital herpes.
Injury
In cases of proctitis caused by physical irritation like anal intercourse or other related activities, it is important to avoid the activity that causes the irritation. Medications may also be recommended to alleviate or manage pain and treat symptoms such as diarrhoea.
Radiation Therapy
Proctitis associated with radiation therapy is relatively common. Research from 2015 indicates that nearly 75% of individuals receiving pelvic radiation develop acute symptoms, while about 20% may experience long-term effects. The treatment depends on the severity. Mild cases can go away on their own.
In cases of severe symptoms, doctors can prescribe corticosteroid enemas to reduce inflammation. Additional medications like sucralfate, commonly used for treating stomach ulcers, may also help alleviate symptoms of radiation-induced proctitis.
Inflammatory Bowel Disease
In cases of proctitis associated with inflammatory bowel disease (IBD), it needs to be treated continuously to manage the symptoms. The main objective should be to minimise inflammation, avoid exacerbations, and sustain remission since no cure has been developed yet.
To achieve this, doctors may prescribe various categories of medications, including:
1. Corticosteroids
These medicines suppress the immune system and reduce inflammation in the treated area. Common options include:
Hydrocortisone
Prednisone
Methylprednisolone
Budesonide
2. Immunomodulators
The medications help control the immune system, which contributes to chronic inflammatory diseases like Crohn’s disease. They are commonly used to manage and reduce the severity of symptoms. Examples include:
Methotrexate
Cyclosporine
6-mercaptopurine
Azathioprine
3. Aminosalicylates
Also known as 5-ASA drugs, these medications are commonly used to control inflammation. Examples include:
Mesalamine
Balsalazide
Olsalazine
Sulfasalazine
4. Ulcerative Colitis
Ulcerative colitis (UC) is a chronic type of IBD that causes inflammation in the lining of the colon and rectum. In severe cases, ulcers or open sores may form. Although there is no cure, a combination of therapies can effectively manage symptoms, reduce flare-ups, and maintain remission.
Medications
If a drug causes inflammation, such as some antibiotics, it is crucial to stop taking the medication. In these situations, the physician can prescribe appropriate substitutes to ensure that one can still undergo the required treatment and the rectal lining is given time to heal.
Medications used to treat UC will likely act on the immune response, as it is an immune-mediated disease. These may include:
Anti-integrin drugs, e.g. vedolizumab (Entyvio)
Interleukin 12/23 inhibitors, such as ustekinumab (Stelara)
Immunomodulators, e.g. methotrexate
TNF-α inhibitors, such as adalimumab or infliximab
Janus kinase (JAK) inhibitors, such as upadacitinib or tofacitinib
Other treatments, such as aminosalicylates or corticosteroids, might also be prescribed by the doctors.
Lifestyle Changes
Although no specific diet can cure UC, certain foods may worsen symptoms. For instance, high-fibre or spicy foods can trigger discomfort in some individuals. A balanced diet that reduces symptoms and flare-ups and promotes healing is frequently advised.
Surgery
Surgery might be required in situations when medications and other treatment methods are not effective. A review indicates that about 20-30% of patients with UC may require surgery. Surgery may involve:
Ileostomy, where waste is emptied into a pouch outside the body attached to the small intestine.
Colectomy, removal of the colon.
Ileoanal pouch surgery, in which an internal pouch is made to join the small intestine to the anal muscles.
FAQs about Proctitis
What are the common causes of proctitis?
Proctitis is a condition caused by inflammation of the rectal lining and may result from various factors. Most prevalent are infections (particularly sexually transmitted infections), inflammatory bowel diseases like ulcerative colitis, and radiation. In other cases, it can also be caused by antibiotic exposure, surgery, or immunologically related disorders.
What symptoms should raise suspicion of proctitis?
The most common symptoms are pain in the rectum, blood, mucus, diarrhoea, and constant need to defecate (tenesmus). There are also those who might have abdominal pain or discomfort during bowel movements, which can greatly impact their day-to-day life.
What is the clinical diagnosis of proctitis?
A physical examination typically initiates diagnosis, such as a digital rectal examination and anoscopy. This can be followed by stool tests, blood tests and such procedures as proctoscopy or flexible sigmoidoscopy to determine the precise cause and extent of inflammation.
What are the treatment options for proctitis?
The treatment varies according to the underlying cause. Bacterial infections are treated with antibiotics, whereas viral infections can be treated with antiviral medications.
Anti-inflammatory drugs, corticosteroids or immunomodulators are often used in conjunction with lifestyle changes in situations associated with inflammatory bowel disease.
Can proctitis be prevented?
Although risk cannot be avoided in all cases, it can be minimised through the implementation of safe sexual practices, treatment of comorbidities such as inflammatory bowel disease and avoidance of unnecessary use of antibiotics. Risk can also be minimised by carefully monitoring radiation therapy.
How long does it take to recover from proctitis?
The recovery time depends on the cause and severity. Symptoms may be managed over time in all forms of chronic cases, although in most mild and acute cases, they can be treated and relieved within a period of 4 to 6 weeks.
What are some of the factors or triggers of proctitis?
Apart from infections and inflammatory diseases, proctitis can also be triggered by physical injury to the rectum. This can be irritation caused by the insertion of objects, exposure to specific chemicals or trauma to the anorectal area.
Is there a risk of cancer in proctitis?
There is no direct association between proctitis and colorectal cancer. Nevertheless, the healing process of severe or chronic inflammation can be delayed and must be assessed and treated properly to prevent complications.
Is proctitis contagious?
Proctitis is not contagious. But in the event that it is triggered by sexually transmitted infections like gonorrhoea, herpes or chlamydia, the infections can be passed on during sexual intercourse. Early detection and notification of partners are important in the successful control and prevention of transmission.
Does diet and lifestyle have an influence on the symptoms of proctitis?
No, diet and lifestyle can influence symptom intensity, particularly in inflammatory bowel disease. Flare-ups can be reduced by avoiding trigger foods (spicy or high-fibre foods may exacerbate symptoms), staying hydrated, and managing stress, which in turn facilitates recovery.
Conclusion
Proctitis is a condition characterised by inflammation of the rectal lining, which can lead to discomfort and disturbances in normal bowel habits. It is commonly associated with sexually transmitted diseases, but other causes such as inflammatory bowel disease, infections, or radiation exposure may also contribute.
For additional guidance, DocTutorials can be your study companion. We offer crisp videos, clinical Qbank, exam-focused notes, flashcards, and mind maps. This helps ensure aspirants gain complete clarity over complex medical topics.
Join DocTutorials today and explore our NEET PG course to excel in your medical career!
NEET PG Exam 2025 is the ultimate gateway for medical graduates aspiring to pursue postgraduate courses in medicine, including MD,…
Hamstring Injury: Symptoms, Diagnosis, and Treatment
A hamstring injury is a strain in any of the three large muscles in the back part of the thigh or their tendons close to the knee or pelvis. These injuries are particularly frequent among athletes, accounting for nearly 12% to 29% of all sports-related injuries, with recurrence rates reported to be over 30%.
Due to their high incidence and tendency to recur, they are a key focus area in the NEET PG exam and clinical practice. Keep reading to learn about the causes, recognise early symptoms, and understand the right diagnostic and treatment approaches for hamstring injuries.
What is a Hamstring Injury?
A hamstring injury is a strain or tear of the muscles on the back of the thigh, and is common in activities that require running and jumping. The severity depends on the extent of muscle damage, with higher-grade injuries causing more intense symptoms and functional limitations.
A hamstring injury is a strain or tear of the muscles in the back of the thigh. It is one of the most commonly observed sports-related injuries. These tears are commonly referred to as hamstring strains, pulled hamstrings or torn hamstrings.
The hamstrings consist of three major muscles in each leg and are among the largest muscles in the thigh. They play a crucial role in almost all leg movements. Activities such as running, jumping, and squatting place high stress and strain on these muscles, which are highly prone to injury compared to most other muscles.
What are the Causes of Hamstring Injury?
Hamstring injuries can be brought about by a mixture of both mechanical stress and other internal or external factors. These are environmental factors, genetic factors, and lifestyle habits like lack of flexibility or proper warm-up.
Hamstring injuries can result from a combination of physical strain and contributing factors. Here are the key causes of hamstring injury:
Infectious/Environmental Causes
Hamstring injuries are typically mechanical, although some environmental factors can increase the risk. For example, exercising or playing sports on uneven or overly hard surfaces may increase the risk of injury. But there is no evidence that infections themselves cause hamstring injuries.
Genetic/Autoimmune Causes
There is some evidence suggesting that genetic factors may influence the likelihood of hamstring injuries. Certain individuals may inherit muscle or tendon traits that make them more prone to strains. Also, autoimmune diseases affecting muscle health may indirectly increase injury risk.
Lifestyle and Dietary Factors
Habits are important factors in hamstring injury. Muscle strain may be caused by poor warm-up habits, lack of flexibility, and inadequate strength training. Moreover, inadequate nutrition may delay muscle recovery and increase the chances of injury.
What are the Risk Factors of Hamstring Injury?
Several factors increase the likelihood of hamstring injuries, including high-intensity sports, previous injuries, and muscle imbalances. Age, fatigue, and poor flexibility further raise the risk by reducing the muscle’s ability to handle physical stress.
Some of the things that may make one susceptible to a hamstring injury include:
Sports: Activities involving sprinting, rapid running, or intense stretching, such as dancing, can increase the risk.
Prior Hamstring Injury: Hamstring injuries happen more frequently in people who have suffered a previous hamstring injury, particularly in those who resume activity sooner than the time of injury.
Muscle Fatigue, Weakness, and Poor Flexibility: Weak or tired muscles are more prone to injury, and muscles that lack flexibility may struggle to handle physical stress.
Muscle Imbalance: When the quadriceps (front thigh muscles) are stronger than the hamstrings, the likelihood of injury increases.
Age: It is more likely that hamstring injuries increase with age.
What are the Symptoms of Hamstring Injury?
Hamstring injuries are accompanied by sudden pain in the back of the thigh, swelling, stiffness, and limited mobility. Extreme instances can include bruising, muscle weakness, and a pop sensation during injury.
The most common symptoms of a hamstring muscle injury include:
A noticeable lump or tight knot in the muscle that can be seen or felt.
Bruising around the affected area.
A popping feeling or sound during the time of the injury (more prevalent in severe cases).
Muscle spasms.
Stiffness in the muscle or tightness.
Pain in the back of the thigh, especially during movement or activity.
Pain near the area where the hamstring connects to the buttocks, particularly while sitting (relief may occur when shifting weight away from that side).
Swelling.
Tenderness when touched.
Difficulty moving the leg properly.
Pain may radiate from the back of the thigh to the groin, buttocks, or other parts of the leg.
More severe (higher-grade) strains lead to stronger and more obvious symptoms. Grade 2 and Grade 3 injuries often result in reduced strength in the affected hamstring.
How is a Hamstring Injury Diagnosed?
Diagnosis is done through clinical examination with the help of imaging methods to determine the amount of muscle damage. Proper assessment helps differentiate hamstring injuries from similar conditions and ensures accurate treatment planning.
To diagnose the injury, it must be evaluated correctly to determine its severity. The diagnosis of a hamstring injury is done as follows:
Clinical Evaluation
A hamstring injury is typically diagnosed with a clinical examination. A healthcare provider will review the patient’s history, including how the injury occurred, the symptoms experienced, and any prior injuries.
Then, a physical examination is performed to determine movement, muscle strength, and tender points.
Diagnostic Tests
To confirm the diagnosis and determine the depth of the injury, other tests may be necessary:
Imaging Tests: MRI (magnetic resonance imaging) is the most common test used to identify soft-tissue injuries, including muscle tears. The injury can also be assessed in real time using ultrasound.
X-rays: Although X-rays cannot show soft tissue damage, they are useful in ruling out fractures or other bone-related conditions.
Differential Diagnosis
Certain conditions may have symptoms similar to a hamstring injury, such as:
Sciatica: The pain that runs along the leg to the lower back as a result of compression of the nerves.
Muscle Cramps: Spasmodic contractions of the muscle, which cause pain.
Tendonitis: Inflammation of tendons around the hip or knee.
These conditions should be differentiated by a proper evaluation to provide the appropriate treatment approach.
What are the Treatment Options for Hamstring Injury?
The treatment aims to relieve pain, reduce swelling, and restore muscle strength through rest, medication, and rehabilitation. Most cases are treated conservatively; however, severe injuries may require advanced treatment or surgery.
The primary aim of treatment is to ease pain and control swelling. The following can be prescribed by a medical practitioner:
Avoid intense physical activities to give the muscle time to recover.
Use ice packs a few times per day to help decrease the swelling and pain.
Apply a compression bandage or wear compression shorts to control swelling.
When possible, elevate the leg above heart level to reduce swelling.
Take over-the-counter painkillers such as ibuprofen (Advil, Motrin IB, and others) or acetaminophen (Tylenol, others).
1. Physical Therapy
A medical practitioner or physical therapist can lead you through some light hamstring stretching and strengthening exercises. As pain and swelling resolve, more exercises can be added to restore strength and flexibility slowly.
2. Surgery or Other Procedures
The majority of the partial hamstring ruptures heal without surgery and respond well to physical therapy. Nevertheless, once the tendons have lost their attachment to the pelvis or shinbone, they can be repaired. Severe muscle tears may also necessitate surgery.
A more recent treatment method is platelet-rich plasma (PRP) therapy. This involves drawing a sample of your blood, separating the platelets and healing components, and injecting them into the injured area. Despite ongoing research, PRP therapy has proven promising for enhancing muscle injury recovery.
FAQs about Hamstring Injury
What are the common causes of hamstring injuries?
Hamstring injuries are commonly a result of abrupt and vigorous actions like running or jumping, which overstretch the muscles. The risk can be enhanced by other conditions such as lack of flexibility, inability to warm up properly, and muscle imbalance.
What does a hamstring injury feel like?
A hamstring injury is mostly characterised by sharp and acute pain in the back of the thigh. Some individuals may feel or hear a “pop” or tearing sensation at the time of injury.
The swelling and tenderness usually occur within a few hours and may be accompanied by the presence of bruising or skin discolouration on the back of the leg.
How is a hamstring injury diagnosed and treated?
Imaging tests such as MRI can be used to confirm a suspected hamstring tear. Management is generally non-surgical and involves rest, ice, compression, and elevation (RICE), along with nonsteroidal anti-inflammatory drugs (NSAIDs) like ibuprofen to help manage pain and inflammation.
How long does it take to recover from a hamstring injury?
Depending on the injury, the recovery time varies. Mild strains may heal within a few weeks, whereas more severe tears can take several months. Following a structured rehabilitation plan can help speed up recovery.
What should I avoid with a hamstring injury?
Do not overstrain or resume physical activity too soon. Straining the muscle prior to complete healing may result in reinjury or a more serious tear. It’s important to consult a healthcare provider before resuming normal activities.
When should I see a doctor for a hamstring injury?
You should seek medical attention in case of severe pain, excessive swelling, or inability to walk. Seeing a doctor is also recommended in case the symptoms are not alleviated by home care.
Are there any long-term effects of hamstring injuries?
Without proper treatment, hamstring injuries can lead to persistent pain, loss of muscle strength, and an increased risk of subsequent injuries. Early treatment and proper rehabilitation are essential for full recovery.
Can a hamstring heal without surgery?
The majority of partial hamstring injuries can be treated through rest and physical therapy, without requiring surgery. However, if the tendons detach from the bone, surgical repair may be required. Severe tears can also be subject to operative care.
What role does physical therapy play in recovery?
Physical therapy is important in recovery as it enhances strength, flexibility, and functional performance. To ensure effective healing, a therapist may develop a custom rehabilitation program to help in safe healing.
Are there any specific exercises to strengthen the hamstrings?
Yes, exercises like hamstring curls, deadlifts, and bridges can help strengthen these muscles. It is advisable to consult a healthcare provider or physical therapist before beginning any new exercise routine.
Conclusion
Hamstring injuries are common, painful disorders that can interfere with daily life and sports performance unless addressed effectively. Although they might be minor at first, lack of rest or returning to activity too soon may slow down the healing process and lead to the risk of recurrence.
For NEET PG aspirants, a clear understanding of topics such as hamstring injuries is essential for both the exam and clinical practice. For additional guidance, DocTutorials can be your study companion. We offer crisp videos, clinical Qbank, exam-focused notes, flashcards, and mind maps. This helps ensure aspirants gain complete clarity over complex medical topics.
Join DocTutorials today and explore our NEET PG course to excel in your medical career!
NEET PG Exam 2025 is the ultimate gateway for medical graduates aspiring to pursue postgraduate courses in medicine, including MD,…
Zollinger-Ellison Syndrome: Causes, Symptoms, and Treatment
Not all digestive health conditions are common or identifiable. One such rare yet important condition is Zollinger-Ellison Syndrome, where the body produces excessive stomach acid due to specific tumours known as gastrinomas, usually found in the pancreas or duodenum.
Zollinger-Ellison Syndrome is uncommon, affecting only about 0.5 to 3 people per million each year. It is most often diagnosed in individuals between the ages of 20 and 50 and is slightly more common in men than in women. Despite its rarity, understanding this condition is crucial, especially for those working in the medical field. Keep reading to know more.
What is Zollinger-Ellison Syndrome?
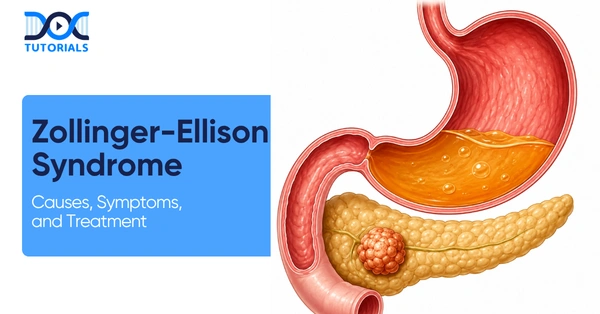
Zollinger-Ellison Syndrome (ZES) is a rare disorder caused by gastrin-secreting tumours located in the pancreas or duodenum. This results in the formation of severe ulcers, reflux, and other digestion-related complications.
The Zollinger-Ellison Syndrome (ZES) is a rare disorder in which tumours known as gastrinomas produce excessive amounts of a hormone called gastrin. Another name for this condition is pancreatic ulcerogenic tumour syndrome.
They are a type of neuroendocrine tumour which are normally found in the pancreas or the duodenum (top part of the small intestine). Of all gastrinomas, 60% are cancerous. These tumours stimulate cells that release gastrin, which in turn stimulates the stomach to produce gastric acid. This excess acid leads to ulcers, acid reflux, and other digestive problems.
This may result in chronic diarrhoea in aggressive peptic ulcer disease in severe cases. Treatment is symptom-based, although in some cases, surgical removal of the tumours can provide a cure. However, tumours can recur.
What are the Causes of Zollinger-Ellison Syndrome?
ZES is caused by gastrin-producing tumours that may arise due to genetic conditions like Multiple Endocrine Neoplasia type 1 or occur randomly. These tumours increase gastrin levels, leading to excess acid secretion and ulcer formation.
Here are the important causes of Zollinger Ellison Syndrome leading to gastrin-secreting tumours:
Genetic Factors
In certain instances, Zollinger-Ellison Syndrome is linked to a hereditary condition called Multiple Endocrine Neoplasia type 1 (MEN1). MEN1 is associated with tumour development in endocrine glands, including the pancreas. Nearly 25–30% of ZES cases are associated with MEN1, indicating a strong genetic influence.
Sporadic Cases
The majority of ZES cases are observed to manifest randomly, with no known family history of cases. These are called sporadic cases. While the exact cause is not yet established, gastrinoma formation is believed to be influenced by genetic mutation in conjunction with environmental factors.
Pathophysiology
In terms of the underlying mechanism, Zollinger-Ellison Syndrome is attributed to excess production of gastrin by gastrinoma tumours.
Gastrin stimulates parietal cells in the stomach to secrete hydrochloric acid. This hypergastrinemia leads to increased acid secretion, which damages the lining of the stomach and intestines. This may cause peptic ulcers, bleeding and perforation (in severe cases).
What are the Symptoms of Zollinger-Ellison Syndrome?
Zollinger-Ellison syndrome may cause abdominal pain, heartburn, diarrhoea, nausea, and unexplained weight loss. Severe cases may lead to ulcers, fat in your stools, and health problems caused by the presence of high acid levels in your body.
There are instances where Zollinger Ellison syndrome may show no symptoms at all. When they occur, symptoms of Zollinger-Ellison syndrome are as follows:
Blood in vomit or stool
Persistent burning or gnawing stomach ache
Feeling tired
Fatty or oily stools
Constant heartburn
Indigestion, especially after consuming fatty meals
Poor appetite
Nausea and vomiting
Unexplained weight loss
Symptoms vary depending on the size and number of tumours. Larger gastrinomas produce more gastrin, leading to higher acid levels and more intense symptoms of peptic ulcer disease.
If the tumours spread (metastasise), especially to the liver, they may lead to liver cancer. Symptoms of liver involvement may include:
Itchy skin
Jaundice
Yellow discolouration of the whites of the eyes and mucous membranes
What is the Diagnosis of Zollinger-Ellison Syndrome?
Diagnosis involves clinical assessment, serum gastrin fasting levels, and other diagnostic methods such as secretin stimulation. Imaging and biopsy are used to identify and determine the nature of tumours.
Diagnosis of Zollinger-Ellison Syndrome (ZES) takes a progressive and systematic approach in order to identify it accurately:
Clinical Evaluation and History Taking
The physician starts by assessing your symptoms, medical history, and any family history of endocrine diseases such as MEN1. Detailed questions are asked about digestive issues, their frequency, and how long they have been present to build a clear clinical picture.
Blood Testing for Gastrin Levels
To measure hormone levels, a fasting serum gastrin test is performed. Although a high level of gastrin is an important measure, above 1,000 pg/mL is only strongly suggestive in cases when the gastric pH is low (less than 2). The Chromogranin A (CGA) test is also employed to aid in the diagnosis since it reveals the presence of neuroendocrine tumour activity.
Secretin Stimulation Testing
This specialised test is used to differentiate Zollinger-Ellison Syndrome from other causes of elevated gastrin levels. After administering secretin, a rise in gastrin levels greater than 120 pg/mL supports the diagnosis of ZES.
Advanced Imaging
Various forms of imaging are used in order to find out and locate any existing tumours. In many cases, the abdominal CT (computed tomography) scan is used first, whereas the MRI (magnetic resonance imaging) is used for detailed imaging of small tumours. These imaging tools help detect lesions that may not be visible through routine methods.
Tissue Diagnosis through Biopsy
A biopsy is important to confirm the diagnosis. The immunohistochemistry (IHC) panels and lymph node biopsies are some of the ways used to identify the characteristics of the tumours and distinguish them as benign or malignant.
Genetic Evaluation
If MEN1 is present, then genetic tests are done to confirm the diagnosis. It also aids in identifying family members who are at risk and formulating management plans accordingly.
What are the Treatment Options of Zollinger-Ellison Syndrome?
Treatment involves the use of various medications and procedures, such as proton pump inhibitors, surgical procedures, and medications. Treatment in the early stages helps to alleviate the symptoms and avoid possible complications.
Zollinger-Ellison Syndrome is managed mainly by addressing the tumours and reducing excessive acid secretion. In most cases, doctors prioritise treating the tumours first. The treatment options include:
1. Preventing Tumour Growth
The following strategies are used to control or slow the development of tumours:
Chemotherapy, which slows tumour growth.
Surgical removal of gastrinomas from the liver to prevent further spread
Embolisation is a procedure to block blood flow to tumours.
Introduction of therapeutic drugs into the tumour to control its activity.
2. Reducing Gastrin Production
Physicians can also prescribe hormonal drugs like octreotide. The drug is used to treat symptoms by decreasing gastrin secretion and to control hormonal effects.
3. Reducing Acid Levels
Excess acid needs to be managed to treat ulcers and reduce symptoms. Treatment mainly includes proton pump inhibitors (PPIs), which are drugs used to inhibit the production of acid. These drugs work by blocking the activity of proton pumps in acid-secreting stomach cells.
Common examples of PPIs include:
Esomeprazole (Nexium)
Omeprazole (Prilosec)
Lansoprazole (Prevacid)
Pantoprazole (Protonix)
Rabeprazole (Aciphex)
For patients with long-term Zollinger-Ellison Syndrome, pantoprazole delayed-release tablets may be used as an ongoing treatment option. Lowering stomach acid levels allows peptic ulcers to heal more effectively and reduces symptom severity.
4. Surgery
Surgical intervention may be considered, although it can be challenging. Gastrinomas are often small and difficult to locate. A surgeon may successfully remove a single tumour, but surgery becomes more complex if multiple tumours are present or if the disease has spread to the liver.
According to the National Organisation for Rare Disorders, complete removal of a gastrinoma is successful in approximately 20–30% of cases. If complications such as peptic ulcers arise, surgery may also be required to:
Repair perforations in the stomach or duodenal wall
Remove blockages caused by ulcers
Control or stop internal bleeding
In rare and severe situations, removal of the stomach may be considered as a last-resort treatment option.
FAQs about Zollinger-Ellison Syndrome
What is the best treatment for Zollinger-Ellison syndrome?
Zollinger-Ellison syndrome is mainly treated with medications known as proton pump inhibitors (PPIs). These medications are regarded as the first-line medication since they can efficiently suppress excessive acid secretion in the stomach.
PPIs work by blocking the activity of tiny acid-producing pumps located in the stomach lining, thereby reducing acid levels and helping relieve symptoms.
What are the first signs of Zollinger-Ellison syndrome?
Some common early symptoms of Zollinger-Ellison syndrome include abdominal pain, nausea, vomiting, unexplained weight loss, and diarrhoea. If properly managed, ulcers can be effectively controlled. But in case it is left untreated, complications can develop.
What causes Zollinger-Ellison syndrome?
Zollinger-Ellison syndrome is caused by tumours known as gastrinomas, which typically develop in the pancreas or the duodenum. These tumours produce large amounts of the hormone gastrin, leading to excessive stomach acid production.
What foods are good for Zollinger-Ellison syndrome?
Since Zollinger-Ellison syndrome leads to increased stomach acid due to gastrin-secreting tumours, diet can help manage symptoms alongside medical treatment.
Low-acid and high-alkaline foods like vegetables and whole grains can be useful in lowering levels of acid and enhancing comfort in the digestive system.
How serious is Zollinger-Ellison syndrome?
Zollinger-Ellison syndrome may be severe and even life-threatening. For instance, a gastrinoma may block the duodenum, which can lead to rupture. Additionally, the tumour may spread to other organs, particularly the liver, increasing the severity of the disease.
What is the best test for Zollinger-Ellison syndrome?
The most effective initial screening test for Zollinger-Ellison syndrome is the fasting serum gastrin test. Ideally, this test is performed when the patient is not taking acid-reducing medications, although it can still be used as a preliminary screening tool even if such medications are being taken.
What is the survival rate of Zollinger-Ellison syndrome?
The survival rate is highly dependent on the spread of the tumours. Patients whose gastrinomas have not metastasised to the liver have an approximate 20-year survival rate of 95%. In contrast, those with liver metastases have an average 10-year survival rate of around 15%, even after undergoing surgery to remove tumours.
At what age do ZES usually start?
Zollinger-Ellison syndrome is a rare disorder which is largely diagnosed among people aged between 20 and 60 years. It is usually characterised by the formation of one or more tumours of the duodenum, pancreas, or nearby lymph nodes.
Is Zollinger-Ellison syndrome cancerous?
In many cases, gastrinomas associated with Zollinger-Ellison syndrome can be cancerous. Recent statistics indicate that approximately 60% of these tumours are cancerous, and by the time they are discovered, they might have extended to other body parts.
However, cases linked to MEN1 are less likely to be cancerous initially, while other forms may carry a higher risk of malignancy.
What should you avoid eating with Zollinger-Ellison syndrome?
People with Zollinger-Ellison syndrome should avoid foods that trigger or increase acid production. This includes spicy foods, citrus fruits, and caffeinated drinks. Avoiding these items can help minimise discomfort and reduce symptom severity.
Conclusion
Zollinger Ellison Syndrome is a serious and rare disorder which may result in excess stomach acid and severe problems without proper management. Although it may feel daunting when you are actually diagnosed, knowing the condition and how to treat it can help you manage it with confidence.
For additional guidance, DocTutorials can be your study companion. We offer crisp videos, clinical Qbank, exam-focused notes, flashcards, and mind maps. This helps ensure aspirants gain complete clarity over complex medical topics.
Join DocTutorials today and explore our NEET PG course to excel in your medical career!
NEET PG Exam 2025 is the ultimate gateway for medical graduates aspiring to pursue postgraduate courses in medicine, including MD,…
Acute Inflammation: Causes, Symptoms, and Treatment
Acute inflammation is a fundamental pathological response that protects the body against harmful stimuli. It plays a critical role in removing injurious agents and initiating tissue repair, and supporting recovery and wound healing.
For those in the healthcare field or aspiring medical professionals, gaining a clear understanding of the causes, symptoms, and treatment of acute inflammation is essential for delivering effective patient care and doing well in exams. Keep reading to know more.
What is Acute Inflammation?
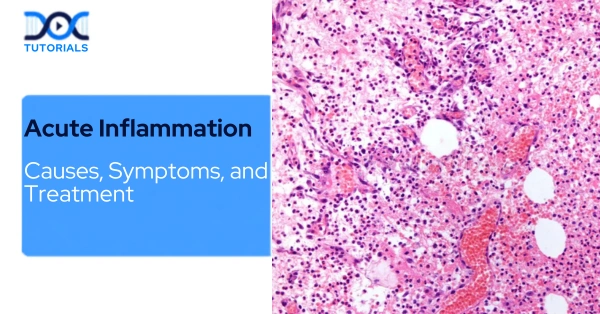
Acute inflammation is the body’s immediate protective response to injury or infection, marked by redness, swelling, and pain. It helps eliminate harmful agents and initiates tissue healing.
Acute inflammation is a direct and adaptive reaction of the body to harm, infection, or tissue damage, and is commonly characterised by the typical features of redness, swelling, and pain. It is the initial defence against harmful stimuli, such as pathogenic microorganisms and chemical irritants.
This response is triggered when the immune system releases pro-inflammatory cytokines and other mediators that rapidly localise to the affected site to eliminate the injurious agent and initiate tissue repair and healing.
What are the Causes Of Acute Inflammation?
Acute inflammation can be triggered by physical injuries, chemical exposure, infections, or allergens, all of which cause tissue damage and activate the immune response.
Acute inflammation can arise as a result of any factor leading to tissue damage or cell injury. These causes may be classified into physical, chemical and biological agents. Physical causes involve trauma like cuts, burns or insect bites. Chemical causes involve exposure to toxic substances, drugs, or environmental pollutants. Biological causes include infections from microorganisms such as bacteria, viruses, and parasites.
Additionally, others can be allergic, such as to certain foods, environmental influences, or animal contact. This leads to the excessive activation of the immune system and the development of acute inflammation.
What are the Risk Factors of Acute Inflammation?
The typical risk factors of acute inflammation are infections, physical trauma, tissue damage, chemical irritants, immune response, and internal irritants that may trigger or intensify the inflammatory process.
Acute inflammation is a temporary immune response to sudden tissue damage or exposure to pathogens. It is a defence process that prevents harm and promotes healing and is clinically characterised by the presence of redness, heat, swelling, and pain.
Below are some common risk factors associated with acute inflammation:
Infections
Invasion by pathogenic microorganisms such as bacteria, viruses, and fungi can activate the immune system, leading to an acute inflammatory response aimed at eliminating the infectious agents.
Physical Trauma
Any form of physical injury, including cuts, burns, fractures, sprains, frostbite, or penetration of foreign bodies (e.g., splinters), may cause immediate tissue damage, triggering inflammation.
Tissue Damage/Necrosis
Cell death caused by ischemia (reduced blood supply), hypoxia, or direct physical injury leads to the release of intracellular components, which act as inflammatory signals.
Chemical Irritants
The tissues may be damaged as a result of exposure to dangerous chemicals, toxins, acids or environmental pollutants and may trigger an inflammatory cascade.
Immune Reactions
Even without direct injury or infection, hypersensitivity reactions (allergies) and autoimmune responses can stimulate inappropriate or excessive inflammatory activity.
Internal Irritants
Dead tissue, immune complexes, or substances produced within the body can act as irritants and keep inflammation active in a specific area.
What are the Symptoms of Acute Inflammation?
Acute inflammation symptoms are identified by five classical signs, such as redness, swelling, heat, pain, and loss of function, each reflecting underlying physiological changes in the body.
Acute inflammation is characterised by 5 classical clinical signs, each reflecting underlying physiological changes:
Redness (Rubor): This happens because of the vasodilation and the raised blood flow (hyperemia) in the affected region, giving it a visibly red appearance.
Swelling (Tumour): Arises from an excess accumulation of fluid in the body tissues known as oedema, characterised by the increased permeability of the blood vessels.
Heat (Calor): Resulting from an increase in blood flow and the metabolism rate at the site of inflammation, leading to an elevation of the local temperature.
Pain (Dolour): Occurs due to the discharge of inflammatory mediators like prostaglandins and bradykinin, which stimulate nerve endings, resulting in tenderness, throbbing, or burning sensations.
Loss of Function (Functio Laesa): Indicates partial or total impairment of functionality caused by pain, swelling, and structural damage.
How is Acute Inflammation Diagnosed?
Diagnosis involves a combination of medical history, physical examination, and diagnostic tests such as blood investigations and imaging to confirm inflammation and identify its cause.
Diagnosis of acute inflammation is a mix of clinical assessment, physical examination, and pertinent diagnostic studies. Upon examining the patient’s medical history, recent trauma, and medications, the doctor performs a complete physical examination to assess the 5 classical signs of acute inflammation: redness, swelling, heat, pain, and loss of function.
Depending on the severity and nature of symptoms, other diagnostic tests can be prescribed, such as blood tests, allergy tests, ultrasound, CT (computed tomography) scans, MRI (magnetic resonance imaging), or biopsy.
The laboratory results tend to show increased levels of inflammatory markers, including C-reactive protein (CRP), erythrocyte sedimentation rate (ESR), and plasma viscosity (PV). After considering every clinical and diagnostic evidence, the doctor makes the diagnosis and develops a treatment plan.
What are The Treatment Options for Acute Inflammation?
Treatment focuses on relieving symptoms and addressing the underlying cause through medications like NSAIDs and corticosteroids, along with supportive care when needed.
Acute inflammation is treated depending on the cause. A doctor may focus on eliminating the root cause, managing the symptoms, or sometimes both at the same time.
For example, if the inflammation is due to a bacterial or fungal infection, the doctor may prescribe antibiotics or antifungal medications. Some of the typical treatments that specifically address inflammation include:
Nonsteroidal Anti-Inflammatory Drugs (NSAIDs)
Nonsteroidal anti-inflammatory drugs (NSAIDs) are the most common in relieving pain, swelling, fever, and other discomforts related to inflammation. Nevertheless, they fail to treat the underlying cause of the condition.
These drugs act by inhibiting some body enzymes which encourage inflammation. Common examples include naproxen, ibuprofen, and aspirin. They can be readily obtained over the counter and online. Nevertheless, they should be used with caution and under the guidance of a doctor or pharmacist, as they may cause side effects.
Acetaminophen, commonly known as paracetamol or Tylenol, helps reduce pain but does not directly decrease inflammation. This allows the inflammatory process to continue supporting the body’s natural healing.
Corticosteroids
Corticosteroids comprise a group of steroid hormones, such as cortisol, which affect the body functions associated with inflammation. They are used to manage conditions such as asthma, allergic reactions, dermatitis, IBD, systemic lupus, hepatitis, arthritis, and temporal arteritis.
These medications are available in different types, including tablets, injections, inhalers, creams, and ointments. However, the prolonged use of these medications poses certain health risks. Therefore, it is advisable that they are taken on prescription.
Immunosuppressants and Chronic Inflammation Management
When inflammation becomes chronic, treatment approaches may differ based on the condition. Some drugs are designed to inhibit the immune system’s response. These medications are useful in managing symptoms of conditions such as psoriasis and rheumatoid arthritis, as well as other autoimmune diseases.
But since they suppress the immune system, they may render the body more susceptible to infections. Immunosuppressant drugs are also essential for individuals who have undergone organ transplant surgery, as they prevent the body from rejecting the new organ. Such individuals need to take extra precautions to avoid infections.
FAQs about Acute Inflammation
What are 5 symptoms of acute inflammation?
Acute inflammation is clinically defined as the presence of five signs: rubor (redness), calor (heat), tumour (swelling), dolour (pain), and functio laesa (loss of function).
What is a common cause of acute inflammation?
Acute inflammation usually happens as a natural response of the body to infection or injury. For example, if you come down with a cold or cut your finger, your body triggers an inflammatory response that directs immune cells to the injury site to start the healing process.
What are the 4 stages or cellular events of acute inflammation?
The four stages of inflammation are: initiation (alarm bells ring), amplification (immune cells rush in), destruction (removal of damaged tissue and pathogens), and resolution (healing and restoring balance). This is the natural process of your body reacting to some injury or infection.
What does acute inflammation feel like?
Acute inflammation is typically painful, reddish, swollen, and warm with or without stiffness or restricted motion in the area. It may be uncomfortable or intense, but it is typically short-term and improves within a few days as healing occurs.
How long is acute inflammation?
Acute inflammation is usually temporary, lasting a few days. When a wound becomes warm, red, painful, and swollen, it is a clear sign that inflammation is occurring.
What is the difference between acute and chronic inflammation?
Acute inflammation is an immediate, temporary reaction to trauma or disease (takes days), which is marked by redness, swelling, and pain in order to facilitate healing.
Chronic inflammation, on the other hand, is a slow, long-term response that can last months or years, often occurring when the immune system fails to eliminate a threat, leading to tissue damage and diseases such as diabetes or arthritis.
Are antibiotics always needed for acute inflammation?
No, acute inflammation does not necessarily require antibiotics. Antibiotics are only used to treat inflammation that is a result of bacterial infections.
Can acute inflammation turn into chronic inflammation?
Yes, acute inflammation can turn into chronic inflammation if the initial trigger is not resolved, if the immune response fails to shut off, or if there are repeated episodes of acute inflammation. While acute inflammation lasts a few days, this transition occurs when the immune system continues to send white blood cells to the site, causing damage over months or years.
Does exercise help with acute inflammation?
Yes, exercise is an effective, non-pharmacological agent which can be used to control inflammation, but its impact relies on its intensity and regularity.
Moderate-intensity exercise is generally anti-inflammatory, reducing systemic inflammatory markers like CRP, whereas intense, prolonged exercise can temporarily increase inflammation.
What foods can reduce acute inflammation?
To reduce acute inflammation, focus on a diet rich in omega-3 fatty acids, antioxidants, and polyphenols, such as fatty fish, berries, leafy greens, nuts, and olive oil. Key anti-inflammatory foods include turmeric, avocados, green tea, peppers, and dark chocolate. A Mediterranean-style diet is highly effective for reducing inflammation.
Conclusion
Acute inflammation pathology is a fundamental concept in medicine, representing the body’s immediate and protective response to injury, infection, or harmful stimuli. Fortunately, all symptoms can be managed effectively with appropriate diagnoses and timely interventions, which may vary depending on the cause.
For every NEET PG aspirant, developing a strong understanding of topics such as acute inflammation and related pathological processes is vital for exam preparation and clinical decisions in real-world practice.
DocTutorials will assist you in this journey through expert-guided video lectures, Quick Revision Programs (QRPs), and high-yield study materials, all designed to help you pass your exams and emerge as a successful future medical professional. Learn more about Doctutorials’ NEET PG course and take a step towards your dream!
NEET PG Exam 2025 is the ultimate gateway for medical graduates aspiring to pursue postgraduate courses in medicine, including MD,…
DocTutorials vs Other Coaching Apps: Why V6 is the Ultimate NEET PG Game-Changer
Enter Mobile Number
Enter your mobile number to access study materials
Enter valid phone number
📱 OTP via SMS
XKk6!qn
Enter the code exactly as shown (case sensitive)
We'll send you a verification code
Verify OTP
OTP sent to
Complete Registration
Academic Details
🎓 Please provide your academic information
Processing...
No internet connection. Please check your network.
✓ Session Active
Preparing for the NEET PG exam is tough. Finding the right coaching platform should not be a struggle. With many options available today, you might naturally feel overwhelmed. You have older, well-known brands, and then you have DocTutorials. Which one should you pick for your medical career? In this blog, we compare DocTutorials with other standard coaching platforms to help you make a smart choice.
The Big Difference: What Makes the New V6 Update Stand Out?
While other apps provide standard videos and tests, DocTutorials has launched the V6 update. This is a massive game-changer. It is not just about basic study material; it is about how you interact with it. With V6, you get smart features like Video Timestamped Comments, allowing you to leave personal notes exactly where you need them. You also get Consolidated Notes and the ability to Highlight and Annotate your MCQ explanations. Other platforms are still catching up to these tools.
DocTutorials V6 vs Other Coaching Apps
Feature
DocTutorials V6
Other Coaching Apps
Learning Approach
System-Based Learning
Isolated Subject Learning
Video Notes
Timestamped comments
Standard static notes
QBank Features
Highlight and annotate
Basic text answers
Motivation
Daily Goals & Streaks
No tracking features
DocTutorials Core Strengths: Built for Smart NEET PG Prep
System-Based Learning: A Clinical Approach
Your foundation is strong, but V6 connects it all. System-Based Learning does not replace your 19 subjects; it integrates them. For example, in the Cardiovascular System, you learn Anatomy, Physiology, Pathology, Pharmacology, Medicine, Surgery, OBGYN, and Radiology in one seamless flow. Since PG exams are highly clinical, this trains you to think exactly like a doctor. You revise smarter, not harder, without jumping blindly between subjects.
Learn With Better Video Lectures
Most apps have video classes. But DocTutorials offers crisp, focused lectures taught directly by top medical educators. You get comprehensive Syllabus Videos, Previous Year Question recall discussions, and Integrated MCQ videos. This combination makes learning complex topics incredibly simple for every student.
Faculty-Reviewed QBank V6
Practicing good questions is the secret to a high rank. The V6 QBank provides over twelve thousand MCQs and Image-Based Questions. It even includes new Video-Based MCQs. While others give you simple answers, DocTutorials lets you create custom tests and bookmark tough questions.
Quick Revision Program (QRP V6)
When the final exam is near, you do not have time for long videos. The QRP V6 gives you crisp, short revision videos. It helps you quickly recall every important subject. Other apps have heavy revision tools, but QRP is famous for being fast.
Visual Learning & Motivation: Streaks and Mind Maps
To remember drugs and formulas, you need visual help. DocTutorials offers interactive Flashcards designed for active recall. You also get topic-wise Mind Maps to simplify complex subjects. Moreover, the new V6 update introduces Daily Goals & Streaks. You can set and track your daily study targets. Maintaining your streak keeps you highly motivated and strictly disciplined throughout your long preparation journey.
Study Materials Comparison Guide
Study Material
DocTutorials V6
Other Coaching Apps
Flashcards
Interactive and shareable
Basic or not included
Mind Maps
Topic-wise and synced
Rarely available
Revision Notes
Consolidated V6 notes
Lengthy PDF files
Test Series
Real exam interface
Basic web interface
Real Exam Test Series & Expert Mentorship
The test series on DocTutorials mimics the actual NEET PG exam perfectly. You get Grand Tests and Topic-wise Mini Tests. After the test, you get detailed faculty analysis. This helps you fix mistakes quickly. Furthermore, studying alone can be stressful. DocTutorials gives you direct access to WhatsApp mentorship groups. Top medical faculty will guide you, answering your doubts directly. With V6, it easily beats older competition.
Frequently Asked Questions (FAQs)
Is DocTutorials good for NEET PG?
Yes, it is one of the absolute best platforms with expert faculty.
What is System-Based Learning in V6?
It integrates all 19 subjects around organ systems for clinical understanding.
How do Goals & Streaks help me?
They help you track daily study targets and keep you motivated.
How many questions are in QBank V6?
It has over twelve thousand carefully reviewed clinical questions.
Are there mind maps available for students?
Yes, subject-wise mind maps are included for very easy revision.
How does the QRP V6 help me?
It provides short, focused videos for very quick final revision.
Does DocTutorials have previous year questions?
Yes, it covers ninety-five percent of past exam questions.
Does the app offer student mentorship?
Yes, top faculty will guide you directly via WhatsApp groups.
Are active recall flashcards included?
Yes, highly interactive flashcards are there to boost your memory.
Is the test series like the real exam?
Yes, it perfectly mimics the real NEET PG computer interface.
Enter your mobile number to access study materials
Enter valid phone number
📱 OTP via SMS
LfV!Fi$
Enter the code exactly as shown (case sensitive)
We'll send you a verification code
Verify OTP
OTP sent to
Complete Registration
Academic Details
🎓 Please provide your academic information
Processing...
No internet connection. Please check your network.
✓ Session Active
Preparing for NEET PG isn’t just about mastering concepts. It’s also about understanding the exam pattern and recognizing frequently asked topics. One of the smartest strategies to boost your preparation is practicing Previous Year Questions (PYQs).
In this article, we bring you a complete subject-wise collection of NEET PG PYQs with detailed answers, designed to support aspirants at every stage of their journey.
Here’s how this resource can help you:
Gain clarity on the exam pattern and recurring question trends
Pinpoint high-yield topics across each subject
Get comfortable with a real exam-like format
Sharpen your speed, accuracy, and confidence
Strengthen weaker areas with focused subject-wise practice
Whether you’re in the early stages of preparation or revising closer to the exam, these NEET PG 2025 PYQs with solutions will give you an extra edge and help maximize your performance on exam day.
Explore How Past Years’ Questions Can Improve Your Preparation
Preparation for the NEET PG examination requires a structured approach, and the referral of previous year question papers. These papers will give a first-hand account of the exam pattern, the level of difficulty, and the topics most frequently asked in it, making it valuable to those who have to start preparing afresh.
In addition, going through NEET PG previous year questionpapers regularly can also assist you in revising the essential concepts and evaluating the level of your progress. You can master your performance as well as improve your knowledge by using original past papers and thus develop self-confidence before the real exam.
Keep reading for a detailed insight into the NEET PG previous year question (PYQ) papers and how studying them can benefit you.
What are the Benefits of Solving NEET PG Previous Year Question Papers?
Here is how going through the NEET PG PYQs can be a game-changer for your NEET preparation:
Improves Accuracy and Speed
Regular practice with the NEET PG previous year question book will help you develop a more precise approach to answering questions. You also get to know how to be careful with making mistakes and improve certain problem-solving skills. This, in the long run, helps you react fast and with confidence, which is the key factor in getting a high score.
Helps in Self-Assessment
NEET PG previous question papers are an excellent tool to ascertain your levels of improvement. They offer a clear overview of the level of your preparation because they tell you about your strong points and about the aspects where you need to improve.
Such specific feedback allows you to work more efficiently. By identifying the topics you are weaker in and working on them consistently, you will enhance both your subject knowledge and confidence.
Builds Familiarity with Question Types
Solving previous papers introduces you to the different formats and styles of questions that commonly appear in the exam. This includes repeated topics and common question trends, giving you an edge on what to expect.
Attempting these papers in full-length mock test settings helps simulate the actual exam environment, allowing you to build the stamina and mental readiness required for test day.
Enhances Time Management
With just 210 minutes to tackle 200 questions, you will have a little over one minute per question. This makes time management a critical skill. Practising with previous NEET PG question papers enables one to develop the habit of working efficiently under pressure.
Through consistent exposure to timed question-solving, you learn to balance speed with precision, ensuring better use of the allotted time.
Acts as an Effective Revision Tool
Working through previous year papers is a powerful method of revising the syllabus. These papers help consolidate what has already been studied by applying knowledge to practical questions.
Many resources offer books and PDFs containing past NEET PG questions, making it easy to integrate this step into a revision plan. Regular practice not only sharpens memory but also boosts overall confidence ahead of the exam.
How to Effectively Solve Previous Year’s Question Papers for NEET PG 2026?
Approaching NEET PG previous year question papers with a clear plan can significantly enhance your preparation. Follow these simplified yet effective steps to make the most out of them:
Incorporate a Paper into Your Daily Schedule
Make it a habit to solve at least one previous year’s question paper each day as part of your regular study timetable. This routine helps build consistency and exam readiness.
Use Past Year Papers to Spot Recurring Topics
Carefully go through previous years’ questions to identify common topics and concepts that are frequently tested. This helps you focus your efforts on areas that carry more weight in the exam.
Practice MCQs After Completing Each Topic
Once you have studied a chapter, reinforce your understanding by solving multiple-choice questions from subject-wise books. This step ensures you are applying what you have learnt in a test-like format.
Identify Key Areas Through Paper Analysis
Analysing past papers allows you to detect which topics appear most often, guiding you to prioritise them during your revision.
Aim to Solve at Least Ten Years’ Worth of Papers
Working through a decade’s worth of previous NEET PG question papers ensures extensive coverage of the syllabus and familiarises you with a wide range of question types and patterns.
What is the Marks Distribution in NEET PG Previous Year Question Papers?
The following is the marks distribution pattern as per the last year NEET PG question paper:
Correct Answer
+4
Incorrect Answer
-1
No response
0
Subject-wise marks distribution pattern is given below:
Section of Question Paper
Number of Subjects
Average Number of Questions
Average Number of Marks
Part A (Pre-Clinical)
3
50
200
Part B (Para-Clinical)
5
100
400
Part C (Clinical)
6
150
600
What is the Subject-Wise Distribution of Questions in the NEET PG Exam?
The table below is an overview of how questions are distributed across different subjects in the NEET PG examination:
Parts in the Question Paper
Name of the Subjects
Number of Questions
Part A (Pre-Clinical)
Microbiology
20
Pharmacology
20
Physiology
17
Anatomy
17
Biochemistry
16
Part B (Para-Clinical)
General Surgery includes Orthopaedics, Anaesthesia, and Radiodiagnosis
45
General Medicine including Dermatology and Venereology
45
Social and Preventive Medicine
25
Pathology
25
Forensic Medicine
10
Part C (Clinical)
Obstetrics and Gynaecology
30
ENT
10
Paediatrics
10
Ophthalmology
10
FAQs About NEET PG Previous Year Question Papers
Will old NEET PG exam questions be repeated?
Yes, certain questions, mostly ones with an emphasis on a fundamental idea or clinical scenario, can repeat in a variant with minor changes. Approximately 10 to 15 questions are repeated yearly in some rephrased way.
How many years of NEET PG papers should an individual solve?
It is advisable to practise at least the last 10 years of question papers to cover a broad range of topics and question styles.
When should I begin to do last year’s question papers?
You will be able to solve them after studying the basics of major subjects. A daily training combined with your studies is the best approach.
Is solving NEET Previous Year’s papers sufficient to score well in the NEET PG exam?
Solving NEET PG previous year question papers significantly improves exam understanding and performance. However, PYQs alone are not sufficient to score high. Candidates must also study standard textbooks, revision notes, updated guidelines, and practice mock tests to build strong concepts and clinical reasoning.
How many questions in NEET PG come from past years’ papers?
On average, around 10–15 questions in the NEET PG exam are directly or indirectly based on previous years’ questions. Exact repetitions are rare; however, similar concepts, clinical scenarios, and frequently tested topics often reappear with slight modifications.
Should PYQs be studied topic-wise or year-wise?
Topic-wise PYQ practice is ideal during the initial phase of preparation as it helps strengthen conceptual clarity and subject understanding. Year-wise PYQs are more beneficial closer to the exam, as they simulate real exam conditions and improve time management and accuracy.
When should NEET PG PYQs be started during preparation?
NEET PG PYQs should be started early in the preparation phase, preferably after completing each subject. Early exposure helps reinforce concepts, identify weak areas, and build exam-oriented thinking. PYQs should be revised multiple times before the final exam.
Are online PYQ question banks reliable for NEET PG?
Most reputed online PYQ question banks are reliable and widely used by NEET PG aspirants. However, candidates should ensure that the answers and explanations are updated according to the latest exam pattern, syllabus changes, and current clinical guidelines.
Are subject-wise PYQs better than mixed practice?
Subject-wise PYQs are more effective during the learning phase, as they help consolidate concepts within a subject. Mixed or year-wise PYQ practice is better during revision, as it enhances integration of subjects and prepares candidates for real exam scenarios.
Can PYQs replace mock tests for NEET PG?
PYQs cannot replace mock tests for NEET PG preparation. However, they play a complementary role by strengthening conceptual clarity and familiarity with exam trends. Mock tests are essential for improving speed, accuracy, time management, and handling exam pressure.
Conclusion
NEET PG previous year question papers are an essential component in a proper preparation strategy to ace this highly competitive NEET PG exam. These papers not only assist you in comprehending the pattern and level of the difficulty but also assist in honing your precision, swiftness, and time balance.
Solving past papers frequently can help you improve not only your problem-solving skills but also track your general progress. Therefore, to enhance the quality of your preparation, resort to reliable sources such as DocTutorials, where the best variety of materials, explanations, and structured guidance provided by the experts cater to NEET PG examinees.
Utilise such resources and remain persistent in your work. Start solving NEET PG previous year question papers today and take a confident step towards achieving your goal. Join DocTutorials and explore our NEET PG course today.
NEET PG 2025 Anatomy Previous Year Questions
Question 1
Non-clinical question
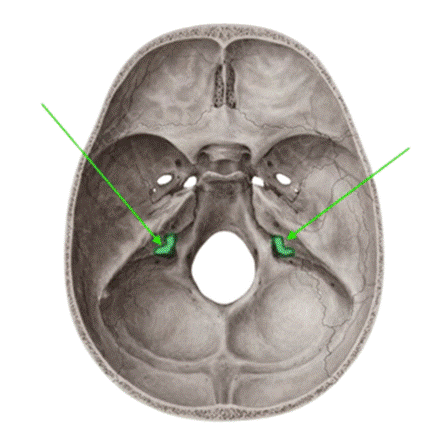
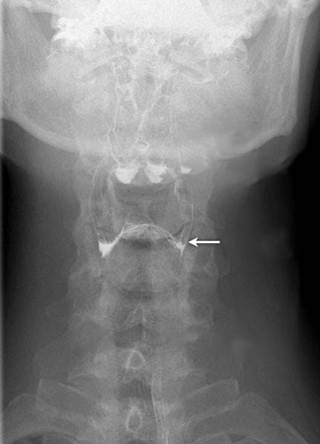
1. Which of the following nerves does not pass through the marked structure?
Options:
Glossopharyngeal nerve
Vagus nerve
Spinal accessory nerve
Hypoglossal nerve
Correct Answer: D) Hypoglossal nerve
Question 2
Non-clinical question
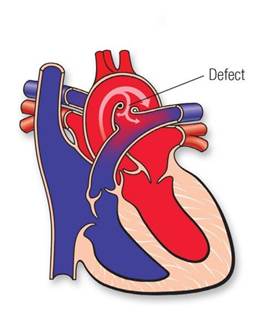
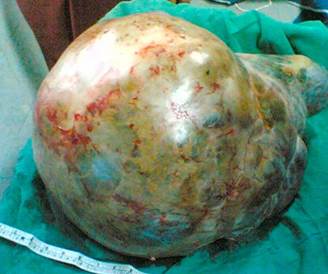
The persistence of which of the following arch arteries is responsible for the congenital anomaly marked in the image given below?
Options:
6th left pharyngeal arch artery
6th right pharyngeal arch artery
4th left pharyngeal arch artery
4th right pharyngeal arch artery
Correct Answer: A) 6th left pharyngeal arch artery
Question 3
Non-clinical question
Upon the delivery of a term new born, a thorough examination of the umbilical cord reveals crucial information. What are the essential components of a healthy umbilical cord?
Options:
2 arteries and 1 vein
2 veins and 1 artery
1 vein and 1 artery
2 veins and 2 arteries
Correct Answer: A) 2 arteries and 1 vein
Question 4
clinical question
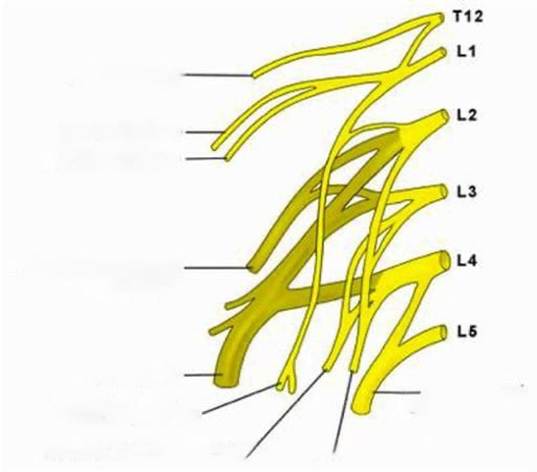
A woman presented with complaints of loss of sensation over the lateral aspect of the thigh and was diagnosed with meralgia paresthetica. The nerve involved in this condition arises from which of the following nerve roots?
Options:
T12 and L1
L1 and L2
L2 and L3
L2, L3, and L4
Correct Answer: C) L2 and L3
Question 5
Non-clinical question
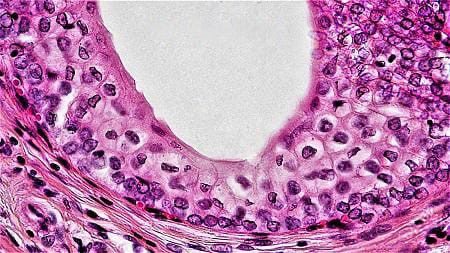
The epithelium depicted in the image below is seen in which of the following structures?
Options:
Esophagus
Ureter
Trachea
Duodenum
Correct Answer: B) Ureter
Question 6
Non-clinical question
A 19-year-old boy presented to the OPD with shoulder pain. He had been training in the gym and had hyperextended his shoulder. On examination, the avulsion of the long head of the triceps was noticed. What is the site at which avulsion of the long head of triceps occurs?
Options:
Shaft of the humerus
Delotoid tuberosity of the humerus
Infraglenoid tubercle
Supraglenoid tubercle
Correct Answer: C) Infraglenoid tubercle
Question 7
Non-clinical question
Identify the marked structure
Options:
Thyroid cartilage
Epiglottis
Pyriform sinus
Valllecula
Correct Answer: C) Pyriform sinus
Question 8
Non-clinical question
A 75-year-old male who is a known case of hypertension and type 2 diabetes mellitus presents with epistaxis, which does not respond to conservative measures and nasal packing. Which of the following arteries should be prioritised for ligation?
Options:
Posterior ethmoidal artery
Anterior ethmoidal artery
Sphenopalatine artery
Greater palatine artery
Correct Answer: C) Sphenopalatine artery
Question 9
Non-clinical question
The marked structure does not have which of the following components?
Options:
GVE
GVA
GSA
GSE
Correct Answer: D) GSE
Question 10
Non-clinical question
Which pair of nerves supplies the muscles marked A and B, respectively?
Options:
Nerve to the mylohyoid and the facial nerve
Facial nerve and spinal accessory nerve
Spinal accessory nerve and facial nerve
Ansa cervicalis and hypoglossal nerve
Question 11
Non-clinical question
During eversion of the foot, which of the following ligaments is most likely to be injured?
Options:
Anterior talofibular
Deltoid ligament
Posterior talofibular
Calcaneofibular
Correct Answer: B) Deltoid ligament
Question 12
Clinical question
During an abdominal surgery, the surgeon accidentally nicks a structure that passes posterior to the epiploic foramen, which results in profuse bleeding. Which of the following structures is most likely to get injured?
Options:
Aorta
Hepatic artery
IVC
Portal vein
Correct Answer: C) IVC
Question 13
Non-clinical question
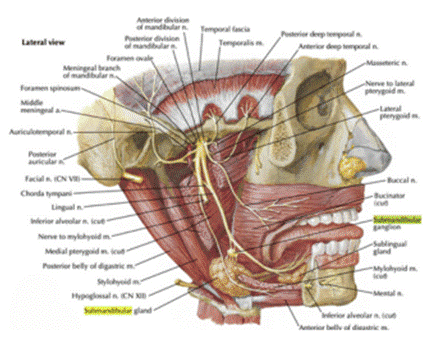
Identify the marked structure that passes inferior to the posterior belly of the digastric and can be seen after submandibular gland resection.
Options:
Facial artery
Hypoglossal nerve
Marginal mandibular nerve
Facial nerve
Correct Answer: B) Hypoglossal nerve
Question 14
Non-clinical question
A patient presents with cancer near the anal opening. Which of the following groups of lymph nodes is most likely to be involved in this patient?
Options:
Superficial inguinal lymph nodes
Deep inguinal lymph nodes
Internal iliac lymph nodes
External iliac lymph nodes
Correct Answer: A) Superficial inguinal lymph nodes
Question 15
Non-clinical question
A patient presents with muscle wasting, reduced tone, and weakness of the right hand. Fine motor movements, such as dough kneading, are also affected. Which of the following structures is most likely to be impaired in this patient?
Options:
Anterior grey horn of the spinal cord in the cervical region
Internal capsule
Corticospinal tract in the cervical region
Brainstem
Correct Answer: A) Anterior grey horn of the spinal cord in the cervical region
NEET PG 2025 Anaesthesia Previous Year Questions
Question 1
Clinical question
Following administration of a muscle relaxant, the patient develops erythema, flushing, and a drop in blood pressure. Which of the following agents is most likely responsible?
Options:
A) Vecuronium
B) Atracurium
C) Cis-atracurium
D) Pancuronium
Correct answer: B) Atracurium
Question 2
Clinical question
A 35-year-old male undergoing abdominal surgery under general anaesthesia develops
sudden generalised muscle rigidity, rapid increase in body temperature, and tachycardia shortly
after administration of sevoflurane and succinylcholine. His end-tidal CO₂ is rising despite
controlled ventilation. What is the most appropriate immediate treatment?
Options:
A) Dantrolene
B) Paracetamol
C) Calcium chloride
D) Propranolol
Correct answer: A) Dantrolene
NEET PG 2025 BiochemistryPrevious Year Questions
Question 1
Clinical question
A labourer was stuck in a tunnel for 5 days without food. Which of the following processes serves as the primary source of energy for the brain during this time?
Options:
A) Glycogenolysis
B) Gluconeogenesis
C) Ketogenesis
D) Lipolysis
Correct answer: C) Ketogenesis
Question 2
Clinical question
Under an experimental condition, blood glucose level is spiked to 2-3 times the normal level and is sustained at this level. Which of the following describes the pattern of insulin levels in the blood?
Options:
A) Sudden rise in insulin followed by a slower, sustained drop in insulin
B) Continuous increase in insulin until a maximum concentration
C) Increase in insulin followed by a decrease below the baseline level
D) Sudden initial increase followed by a delayed but higher and continuing increase in insulin levels
Correct answer: D) Sudden initial increase followed by a delayed but higher and continuing increase in insulin levels
Question 3
Non-clinical question
A patient presents with ataxia, anaemia, and sensory neuropathy. Laboratory tests show elevated total homocysteine and methylmalonic acid levels. Production of which of the following amino acids could be affected?
Options:
A) Tyrosine
B) Glutamine
C) Cysteine
D) Methionine
Correct answer: D) Methionine
Question 4
Clinical question
A patient on long-term hydrochlorothiazide presents with features of heart failure,
horizontal nystagmus, and peripheral neuropathy. There is no history of alcohol use or smoking. Which of the following deficiencies can cause this presentation?
Options:
A) Thiamine
B) Selenium C) Zinc
D) Vitamin B12
Correct answer: A) Thiamine
Question 5
Clinical question
A 10-year-old boy presents with coarse facial features, organomegaly, corneal opacity, and peripheral neuropathy. A deficiency of the enzyme alpha-L-iduronidase is found. Which of the following is accumulated in this condition?
Options:
A) Dermatan sulfate and heparan sulfate
B) Dermatan sulfate
C) Keratan sulfate and chondroitin sulfate
D) Sphingolipids
Correct answer: A) Dermatan sulfate and heparan sulfate
Question 6
Clinical question
A 10-year-old presents with multiple freckles and hyperpigmentation that worsens with sun exposure. Examination reveals two basal cell carcinomas on the face. Which of the following DNA repair mechanisms is defective?
Options:
A) Base excision repair
B) Nucleotide excision repair
C) DNA mismatch repair
D) DNA double-strand break repair
Correct answer: B) Nucleotide excision repair
Question 7
Clinical question
A 10-month-old boy presents with recurrent oral lesions and respiratory infections. Laboratory investigations reveal reduced B cell, T cell, and NK cell counts along with reduced adenosine
deaminase levels. Which of the following is the most likely diagnosis?
Options:
A) Agammaglobulinemia
B) Alpha-1 antitrypsin deficiency
C) DiGeorge syndrome
D) Severe combined immunodeficiency
Correct answer: D) Severe combined immunodeficiency
Question 8
Non-clinical question
Which of the following molecular diagnostic tests is useful in syndromic conditions like meningitis?
Options:
A) Uniplex PCR
B) Multiplex PCR
C) Nested PCR
D) Arbitrarily primed PCR
Correct answer: B) Multiplex PCR
Question 9
Non-clinical question
A frameshift mutation was introduced into the coding sequence of an mRNA. If this occurs at the 4th position in an mRNA with 900 nucleotides, which of the following is most likely to happen?
Options:
A) No biological change
B) Partial loss of protein and function
C) Complete loss of protein and function
D) No change in function as it will be removed in post-translational modification
Correct answer: C) Complete loss of protein and function
Question 10
Clinical question
A 40-year-old woman who underwent ileal resection presents with features of anaemia despite a balanced diet. Her RBC count is 2.8 million/mm³, and serum iron is 164 mcg/dL. Which of the
following is most likely to be found in her?
Options:
A) Iron deficiency anaemia
B) Megaloblastic anaemia
C) Aplastic anaemia
D) Hemolytic anaemia
Correct answer: Megaloblastic anaemia
Question 11
Non-clinical question
Which of the following, if given in large volumes, can lead to hyperchloremic metabolic acidosis?
Options:
A) Dextrose in NS (DNS)
B) Normal saline
C) 5% dextrose in water
D) Ringer’s lactate
Correct answer: B) Normal saline
Question 12
Clinical question
A patient presents with bleeding symptoms and factor 9 deficiency that resolve after
administration of a vitamin K injection. Which of the following is the most likely underlying condition?
Options:
A) Classical haemophilia
B) Biliary obstruction
C) Pernicious anaemia
D) Hepatitis A
Correct answer: B) Biliary obstruction
Question 13
Clinical question
A child presents with elevated concentrations of phenylalanine. Phenylalanine hydroxylase activity is found to be normal. Which of the following coenzymes, also required for tyrosine metabolism, could be deficient in this child?
Options:
A) Biopterin
B) Pyridoxal phosphate
C) Adenosylcobalamin
D) Dihydrofolic acid
Correct answer: A) Biopterin
Question 14
Clinical question:
An 8-year-old boy presents to the OPD for evaluation of a subcutaneous xanthoma on his right elbow. His father recently died of a myocardial infarction, and there is a family history of similar findings. Laboratory investigations reveal total cholesterol of 480 mg/dL, triglycerides of 146 mg/dL, and LDL cholesterol of 300 mg/dL. Which of the following types of
Familial hyperlipoproteinemias is the most likely underlying condition?
Options:
A) Type I
B) Type IIa
C) Type IIb
D) Type III
Correct answer: B) Type IIb
Question 15
Clinical Question:
A 70-year-old man presents with a fracture following trivial trauma. He also has perifollicular haemorrhages, lusterless hair, and dry skin. He is on an exclusive diet of toast and buns and has microcytic hypochromic anaemia. Which of the following enzymes is most likely affected in this patient?
Options:
A) Prolyl hydroxylase
B) ALA synthase
C) Glutathione peroxidase
D) Dihydrofolate reductase
Correct answer:A) Prolyl hydroxylase
Question 16
Clinical question:
A 7-month-old infant presents with developmental delay, seizures, and a cherry-red spot on fundoscopy. The mother has a history of an abortion at 8 weeks. Genetic testing reveals a deficiency of hexosaminidase A. Which of the following accumulates in this condition?
Options:
A) GM1 ganglioside
B) GM2 ganglioside
C) Galactocerebroside
D) Sphingolipids
Correct answer: B) GM2 ganglioside
Question 17
Clinical question:
A boy presents with orange-colored tonsils and a family history of multiple cardiovascular-related deaths. Laboratory investigations show total cholesterol of 80 mg/dL, triglycerides 146 mg/dL, HDL <5 mg/dL, and LDL 90 mg/dL. Which of the following is the most likely diagnosis?
Options:
A) Niemann-Pick disease type C
B) Tangier disease
C) Familial abetalipoproteinemia
D) Familial hyperlipoproteinemia type I
Correct answer:B) Tangier disease
NEET PG 2025 Dermatology Previous Year Questions
Question 1
Clinical Question
A 20-year-old presented with a non-progressive hypopigmented skin lesion that has been present since birth. It shows white accentuation under Wood’s lamp examination, and diascopy is inconclusive. What is the most likely diagnosis?
Options:
A) Vitiligo
B) Nevus depigmentosus
C) Nevus anaemicus
D) Indeterminate leprosy
Correct Answer: B) Nevus depigmentosus
Question 2
Non-Clinical Question
An image shows the characteristic skin findings of phrynoderma, described as plugged keratotic papules. Which of the following should be done next?
Options:
A) Ocular examination
B) Vitamin D3 status
C) Deep tendon reflexes
D) Vitamin B12 status
Correct Answer: A) Ocular examination
Question 3
Clinical Question
A patient presents with a plaque on the face with central clearing and atrophy, and his chest X-ray demonstrates apical calcification. Which of the following can be used for the diagnosis of the underlying condition?
Options:
A) PCR
B) Mantoux test
C) Slit skin smear test
D) Probe test
Correct Answer: A) PCR
NEET PG 2025 ENT Previous Year Questions
Q.1
Clinical Question:
A 28-year-old male with a history of chronic ear discharge and hearing loss undergoes an otoscopic evaluation. The image below shows a large central perforation of the tympanic membrane with visible middle ear structures. What is the most appropriate surgical intervention for this patient?
Options:
Atticotomy
Modified radical mastoidectomy
Myringoplasty
Tympanoplasty
Correct Answer: D) Tympanoplasty
Q.2
Clinical Question:
An industrial worker presents with hearing loss. On examination, Rinne’s test was negative on the left side and positive on the right side. Weber’s test lateralized to the left side. Pure Tone Audiometry (PTA) was done with the results as shown below. What is the most appropriate diagnosis?
Options:
Right conductive hearing loss
Left conductive hearing loss
Right sensorineural hearing loss
Left sensorineural hearing loss
Correct Answer: B) Left conductive hearing loss
Q.3
Clinical Question:
A 12-year-old male presents with recurrent, profuse nasal bleeding and right-sided nasal obstruction. Endoscopy reveals a globular, vascular mass in the right nasal cavity occupying the posterior choanae and nasopharynx. A CT scan shows anterior bowing of the posterior wall of the maxillary sinus. What is the most likely diagnosis?
Options:
Nasopharyngeal angiofibroma
Antrochoanal polyp
Rhinoscleroma
Rhinosporidiosis
Correct Answer: A) Nasopharyngeal angiofibroma
Q.4
Clinical Question:
A patient presents to the emergency department with significant nasal trauma after a fall.
Examination reveals a deviated nasal pyramid, and palpation confirms crepitus and mobility of
the nasal bones. A lateral nasal bone X-ray confirms a displaced nasal bone fracture. Which of
the following instruments is specifically designed for the closed reduction of a displaced nasal
bone fracture?
Options:
Tilley’s forceps
Luc’s forceps
Walsham forceps
Bayonet forceps
Correct Answer: C) Walsham forceps
Q.5
Clinical Question:
Following a building collapse, a male patient was brought to the emergency department with a copious amount of debris in the mouth, making endotracheal intubation impossible. The emergency procedure shown in the image was performed. Which of the following statements regarding this procedure is true?
Options:
It is used for effective ventilation for up to 6 hours
It is used to measure central venous pressure
It should be followed by a tracheostomy
The work of breathing is more than with bag-and-mask ventilation
Correct Answer: C) It should be followed by a tracheostomy
Q.6
Clinical Question:
A 3-year-old child presents to the casualty in an unresponsive state after consuming peanuts. What is the most appropriate immediate management?
Options:
Give abdominal thrusts
Give 5 back slaps
Start chest compressions
Attempt endotracheal intubation
Correct Answer: C) Start chest compressions
Q.7
Clinical Question:
A 72-year-old female smoker presents with a long history of hoarseness of voice, difficulty swallowing, and difficulty breathing. The patient was diagnosed with laryngeal cancer and underwent surgical management. The post-operative picture is shown below. Which of the following surgeries was most likely performed on the patient?
Options:
Partial laryngectomy
Total laryngectomy
Standard tracheostomy
Percutaneous tracheostomy
Correct Answer: B) Total laryngectomy
Forensic Medicine
NEET PG 2025 Forensic Medicine Previous Year Questions
Question: 1
Clinical question
A 26-year-old woman is brought dead to the emergency department. On examination, there are multiple crescentic abrasions over the sides of her neck and lower jaw, along with deep bruising of neck muscles on internal dissection during autopsy. The hyoid bone is intact, but a minor haemorrhage is seen in the strap muscles. Which of the following is the most likely cause of death?
Options:
Ligature Strangulation
Mugging
Throttling
Garroting
Correct Answer: C) Throttling
Question 2
Non-clinical question
As per the Protection of Children from Sexual Offences (POCSO) Act, who is legally considered a child under the law for protection against sexual offences?
Options:
Girls under 16 years of age
All children under 16 years of age
All children under 18 years of age
Girls under 18 years of age
Correct Answer: C) All children under 18 years of age
Question 3
Non-clinical question:
Which of the following statements regarding the “Zasko phenomenon” is true?
Options:
A) It refers to the postmortem clotting of blood
B) It is used to describe the gaping of a wound along skin tension lines
C) It refers to the tendon reflex after death
D) It is used to describe the seeping of blood from wounds at the time of death
Correct Answer: C) It refers to the tendon reflex after death
Question 4
Non-clinical question
A 22-year-old male is found dead in his room. On autopsy, the stomach contents emit a strong garlic-like odour, and red-velvet discolouration of the gastric mucosa is noted, along with greyish granular material resembling pesticide powder. Which of the following is the most likely poison involved?
Options:
A) Organophosphorus compound
B) Acute arsenic poisoning
C) Aluminium phosphide
D) Carbamates
Correct Answer: B) Acute arsenic poisoning
Question 5
Clinical question
A 16-year-old girl and a 23-year-old boy undergo medical examination following allegations of rape made by the girl’s parents. The girl states the sexual act was consensual, and no injuries were found on examination. According to the law, what is the legal status of the consent in this case?
Options:
Consent is invalid as the girl is under 18 years old
No punishment since the act was consensual
No punishment since the man says he loves her and wants to marry her
Parents must prove that the act was non-consensual
Correct Answer: A) Consent is invalid as the girl is under 18 years old
NEET PG 2025 Medicine Previous Year Questions
Question 1: A patient presents with complaints of salt craving, generalized hyperpigmentation, and laboratory findings of hyperkalemia and metabolic acidosis. Which of the following is the most likely diagnosis?
Options:
A) Addison’s disease B) Conn’s disease C) Pheochromocytoma D) Cushing’s syndrome
Correct Answer: A) Addison’s disease
Question 2: A critically ill patient with COVID-19 is admitted to the ICU and requires mechanical ventilation. The patient’s PaO₂/FiO₂ ratio is 100, consistent with severe Acute Respiratory Distress Syndrome. Which of the following ventilatory strategies is most appropriate for managing this patient?
Options: A) High PEEP and high tidal volume B) Low PEEP and low tidal volume C) Low PEEP and high tidal volume D) High PEEP and low tidal volume
Correct Answer: D) High PEEP and low tidal volume
Question 3: A 15-year-old boy presents with progressive enlargement of hands and feet, coarse facial features, prominent enlarged jaw, and frontal bossing. On examination, he is noted to have bitemporal hemianopia. Which of the following is the most definitive test to confirm the diagnosis?
Options: A) Increased IGF-1 levels B) Decreased IGF-1 levels C) Suppressed GH on administration of glucose
D) Non-suppressed GH on administration of glucose
Correct Answer: D) Non-suppressed GH on administration of glucose
Question 4: A 69-year-old man presents with severe dyspnea and increasing amounts of clear sputum. ABG reveals pH 7.2, PCO₂ 66 mmHg, PaO₂ 44 mmHg, and bicarbonate 26 mEq/L. His SpO₂ is 77%. Which of the following is the underlying abnormality?
Options: A) Metabolic acidosis B) Metabolic alkalosis C) Respiratory acidosis D) Respiratory alkalosis
Correct Answer: C) Respiratory acidosis
Question 5: An asthmatic patient on salbutamol and ipratropium continues to have nocturnal exacerbations. Which of the following is the next best step?
Options: A) Add oral corticosteroids B) Switch to an inhaled corticosteroid plus a long-acting β2-agonist C) Increase frequency of salbutamol D) Add montelukast at night
Correct Answer: B) Switch to an inhaled corticosteroid plus a long-acting β2-agonist
Question 6: A 19-year-old boy was diagnosed with meningococcal meningitis. What is the drug of choice (DOC) for prophylaxis to be given to his contacts?
Options: A) Rifampicin B) Ethambutol C) Doxycycline D) Amoxicillin
Correct Answer: A) Rifampicin
Question 7: A patient presents with pain and swelling of the knee joint. Synovial fluid aspirate shows rhomboid-shaped crystals that are positively birefringent under polarized light microscopy. What is the most likely diagnosis?
Options: A) Gout B) Pseudogout C) Amyloidosis D) Rheumatoid arthritis
Correct Answer: B) Pseudogout
Question 8: A patient presents with progressive skin thickening. Laboratory evaluation reveals ANA positivity along with anti–Scl-70 antibodies. Which clinical manifestation is most strongly associated with this antibody?
Options: A) Gastric antral vascular ectasia B) Calcinosis cutis C) Interstitial lung disease D) Raynaud’s phenomenon
Correct Answer: C) Interstitial lung disease
Question 9: A patient presents with frothy sputum, hemoptysis, paroxysmal nocturnal dyspnea, and dyspnea on exertion. Lung biopsy reveals hemosiderin-laden macrophages. Which of the following conditions is least likely to be associated with this finding?
Options: A) Volume overload B) Right ventricular failure C) Pulmonary vein obstruction D) Protein-losing enteropathy
Correct Answer: B) Right ventricular failure
Question 10:
A 50-year-old man presents to the emergency department with altered sensorium, hypotension, and shortness of breath. His arterial blood gas reveals a pH of 7.2, PaCO₂ of 44 mmHg, PaO₂ of 54 mmHg, HCO₃⁻ of 16 mEq/L, and a base excess of -12. Serum electrolytes show sodium 130 mEq/L and chloride 84 mEq/L. Based on these findings, what is the most likely acid–base disturbance?
Options:
A) Metabolic acidosis with anion gap of 30
B) Metabolic acidosis with anion gap of 20
C) Respiratory acidosis with anion gap of 30
D) Respiratory alkalosis with anion gap of 20
Correct Answer: A) Metabolic acidosis with anion gap 30
Question 11: A 45-year-old woman presents with a 6-month history of paroxysmal nocturnal dyspnea, palpitations, and breathlessness. On examination, blood pressure and oxygen saturation are normal, jugular venous pressure is elevated, the pulse is irregular, and tender hepatomegaly is present. Cardiac examination reveals a heaving apex and a mid-diastolic murmur at the apex. She has a past history of acute rheumatic fever. Which of the following statements regarding this patient is false?
Options: A) This patient has an increased risk of stroke B) “a” wave is absent on JVP C) This patient has features of right heart failure D) Pre-systolic accentuation of the mid-diastolic murmur is a hallmark feature
Correct Answer: D) Pre-systolic accentuation of the mid-diastolic murmur is a hallmark feature
Question 12: A patient presents with morning stiffness and tests positive for anti-CCP antibodies. Which of the following histological features is most characteristic of the underlying disease?
Options: A) Synovial inflammation with pannus formation B) Cartilage degeneration with osteophyte formation C) Subepidermal blister with IgA deposits D) Tophus with monosodium urate crystals
Correct Answer: A) Synovial inflammation with pannus formation
Question 13: A 70-year-old patient with hypertension and atrial fibrillation presents with an acute-onset weakness of right side of body and aphasia, which began 2 hours ago. A non-contrast CT scan of the brain shows no evidence of haemorrhage. What is the next best step in management?
Options: A) Administration of intravenous rTPA B) Carotid Doppler ultrasound C) Transesophageal echo D) IV low molecular weight heparin
Correct Answer: A) Administration of intravenous rTPA
Question 14: An HIV-positive patient presents with a 2-week history of fever, cough, and weight loss. He is diagnosed with tuberculosis. What is the most appropriate approach to management?
Options: A) Start antiretroviral therapy (ART) 2 weeks after initiating anti-tubercular therapy (ATT) B) Start ATT and ART simultaneously C) Start ART after completing the course of ATT D) Start ATT 2 weeks after initiating ART
Correct Answer: A) Start antiretroviral therapy (ART) 2 weeks after initiating anti-tubercular therapy (ATT)
Question 15: A 55-year-old man with a long-standing history of diabetes mellitus presents with numbness and tingling in both feet. On examination, deep tendon reflexes in the lower limbs are reduced. Which of the following is the most likely cause of his symptoms?
Options:
A) Bilateral distal symmetric polyneuropathy
B) Autonomic neuropathy
C) Mononeuropathy
D) Acute motor axonal neuropathy
Correct Answer: A) Bilateral distal symmetric polyneuropathy
Question 16: A 21-year-old female, a known case of insulin-dependent diabetes mellitus (IDDM), presents to the emergency department with altered sensorium. She has a history of missing her insulin doses for the past two days. On examination, her blood pressure is 80/60 mmHg and pulse rate is 103/min. Laboratory values reveal a serum sodium of 126 mEq/L, potassium 4.3 mEq/L, BUN 79 mg/dL, creatinine 2.2 mg/dL, and a random blood glucose level of 720 mg/dL. Which of the following is not a part of the initial management of this patient?
Options: A) 3% NaCl B) 0.9% NaCl C) IV insulin D) Monitor potassium level
Correct Answer: A) 3% NaCl
Question 17: A 55-year-old female presents with respiratory distress and hemoptysis on day 7 after knee replacement surgery. Her respiratory rate is 28/min, and pulse is 120/min. What is the most appropriate investigation?
Options: A) Ventilation-perfusion (V/Q) scan B) Chest X-ray C) CT Pulmonary Angiography (CTPA) D) D-dimer
Correct Answer: C) CT Pulmonary Angiography (CTPA)
Question 18: A patient in altered sensorium is found to have a serum sodium of 95 mEq/L. She was treated with 3% hypertonic saline, and after 24 hours, her sodium level increased to 111 mEq/L. After sodium correction, her neurological status has deteriorated. What is the next best step in management?
Options: A) Brainstem evoked potential B) Electroencephalogram (EEG) C) MRI brain D) CSF analysis
Correct Answer: C) MRI brain
Question 19:
A 12-year-old child with chronic kidney disease is admitted for evaluation of bone pain and growth retardation. Laboratory investigations reveal: serum calcium 7.2 mg/dL, serum phosphate 6.3 mg/dL, alkaline phosphatase 370 U/L, and elevated parathyroid hormone levels. X-ray of the long bones shows metaphyseal dysplasia. Which of the following is the most appropriate treatment for this patient? Options: A) Phosphate binders only B) Oral calcium supplements C) Calcium supplements with phosphate binders D) Oral calcium with vitamin D
Correct Answer: C) Calcium supplements with phosphate binders
Question 20:
A 70-year-old male presents to the emergency department with dyspnea and palpitations for the past 4 hours. ECG is suggestive of atrial fibrillation. He is hemodynamically stable. What is the next best step in management?
Options: A) Emergency cardioversion B) Control ventricular rate C) Echocardiography to look for left atrial clot D) Start low molecular weight heparin
Correct Answer: B) Control ventricular rate
NEET PG 2025 Microbiology Previous Year Questions
Question 1
Clinical question
A farmer presents with an ulcerative skin lesion with central necrosis. A smear from the lesion, stained with polychrome methylene blue, shows capsulated bacilli positive for the M’Fadyean reaction. Which of the following is the most likely diagnosis?
Options:
A) Bacillus anthracis
B) Yersinia pestis
C) Clostridium perfringens
D) Chlamydia trachomatis
Correct answer: A) Bacillus anthracis
Question 2
Clinical question
A 32‑year‑old farmer presents with high‑grade fever, severe myalgia, and redness of the eyes. Investigations reveal elevated bilirubin. Which of the following is the most likely diagnosis?
Options:
A) Brucellosis
B) Weil’s syndrome
C) Malaria
D) Enteric fever
Correct answer: B) Weil’s syndrome
Question 3
Clinical question
A 19‑year‑old college student presents with sudden‑onset fever, headache, vomiting, and a rapidly spreading purpuric rash. He appears confused, and his BP is measured to be 80/50 mmHg, HR 120/min, and Temp 39.5°C. On examination, he has petechiae and purpura over his lower limbs and trunk. He succumbs to his illness, and an autopsy is carried out. The gross specimen of the brain is shown below. Which of the following pathogens is the most likely cause of his condition?
Options:
A) Streptococcus pneumoniae
B) Haemophilus influenzae type B
C) Neisseria meningitidis
D) Listeria monocytogenes
Correct answer: C) Neisseria meningitidis
Question 4
Clinical question
A 35‑year‑old man presents with a 2‑week history of low‑grade fever, nonproductive cough, weight loss, and fatigue. Chest X‑ray shows bilateral hilar lymphadenopathy with patchy infiltrates. A lactophenol cotton blue mount from the sputum culture appears as below. What is the most likely diagnosis?
Options:
A) Pulmonary tuberculosis
B) Histoplasmosis
C) Coccidioidomycosis
D) Blastomycosis
Correct answer: B) Histoplasmosis
Question 5
Non-clinical question
Group A Streptococcus is the most common cause of bacterial pharyngitis in school-aged children. Which of the following bacterial components is primarily responsible for its attachment to fibronectin on the epithelial lining of the pharynx?
Options:
A) Lipoteichoic acid
B) Capsule
C) Flagella
D) Lipoprotein
Correct answer: A) Lipoteichoic acid
Question 6
Clinical question
A child presents with intense perianal itching, especially at night. On examination, thread‑like white worms are seen in the perianal region, and the microscopic examination is shown below. Which of the following is the most likely causative organism?
Options:
A) Enterobius vermicularis
B) Ancylostoma duodenale
C) Trichuris trichura
D) Ascaris lumbricoides
Correct answer: A) Enterobius vermicularis
Question 7
Clinical question
A child presents with painful vesicular lesions near the mouth. Tzanck
smear reveals multinucleated giant cells with intranuclear inclusions. What is the most likely
causative organism?
Options:
A) Cytomegalovirus
B) Herpes simplex virus
C) Varicella-zoster virus
D) Molluscum contagiousm virus
Correct answer: B) Herpes simplex virus
Question 8
Clinical question
A male patient presents with fever, cough, and hemoptysis. Microscopic examination of bronchoalveolar lavage (BAL) fluid shows septate hyphae with acute-angle dichotomous branching. Which of the following is the most likely diagnosis?
Options:
A) Mucormycosis
B) Histoplasmosis
C) Aspergillosis
D) Candidiasis
Correct answer: C) Aspergillosis
Question 9
Clinical question
A middle-aged man from a tropical region presents with progressive swelling of the lower limb. A peripheral blood smear is shown below. What is the most likely cause of his limb swelling?
Options:
A) Hypoalbuminemia
B) Lymphatic obstruction
C) Hypoproteinemia
D) Increased hydrostatic pressure
Correct answer: B) Lymphatic obstruction
Question 10
Clinical question
A patient presents with chronic meningitis. Laboratory findings reveal Gram-positive, filamentous branching bacteria which are weakly acid-fast with modified Ziehl–Neelsen (ZN) stain. The paraffin bait technique is used to isolate the organism. Which of the following is the most likely causative organism?
Options:
A) Actinomyces israeli
B) Mycobacterium tuberculosis
C) Nocardia asteroides
D) Cryptococcus neoformans
Correct answer: C) Nocardia asteroides
Question 11
Clinical question
In a village, several people develop dysentery after consuming raw milk. Laboratory examination of stool samples reveals: Gram-negative, curved rods with predominant polymorphonuclear infiltration. Which of the following is the most likely causative organism?
Options:
A) Clostridium perfringens
B) Staphylococcus aureus
C) Vibrio parahaemolyticus
D) Campylobacter jejuni
Correct Answer: D) Campylobacter jejuni
Question 12
Clinical question
A patient presents with a long-standing swelling and discharging sinuses on the foot as shown below. The discharge contains black granules. What is the most likely finding on the KOH mount?
Options:
A) Small spores and pseudohyphae
B) Arthrospores
C) Septate hyphae with 4-5 microns in width
D) Filamentous branching bacteria
Correct Answer:C) Septate hyphae with 4-5 microns in width
NEET PG 2025 OBG Previous Year Questions
Q.1
Clinical Question:
In a woman with a regular 28-day menstrual cycle, which of the following best describes the typical hormonal profile during days 21 to 25 of the cycle?
Options:
Low estrogen, high progesterone, low LH and FSH
Low estrogen, low progesterone, low FSH and LH
Low estrogen, high progesterone, high FSH and LH
High estrogen, high progesterone, low FSH and LH
Correct Answer: D) High estrogen, high progesterone, low FSH and LH
Q.2
Clinical Question:
Identify the manoeuvre shown in the given image.
Options:
Manual removal of placenta
Controlled cord traction
Uterine massage
Bimanual compression of the uterus
Correct Answer: B) Controlled cord traction
Q.3
Clinical Question:
A 32-year-old woman with an obstetric score of P2L2 presents with 6 months of secondary amenorrhea. Laboratory evaluation shows FSH 36 mIU/mL, LH 56 mIU/mL, and anti-Müllerian hormone (AMH) 0.05 ng/mL. Which of the following is the most likely diagnosis?
Options:
Polycystic Ovarian Syndrome
Primary Ovarian Insufficiency
Hypothyroidism
Hyperprolactinemia
Correct Answer: B) Primary Ovarian Insufficiency
Q.4
Clinical Question:
A 28-year-old woman in labour is undergoing per vaginal examination, and a pulsating umbilical cord is felt below the presenting part. What is the most appropriate next step in management?
Options:
Elevate buttocks, push the presenting part upward, and fill the bladder
Attempt to reposition the cord into the vagina and vaginal packing
Wait and watch with close monitoring
Augment labor with oxytocin
Correct Answer: A) Elevate buttocks, push the presenting part upward, and fill the bladder
Q.5
Clinical Question:
A G2P1L1 with a history of a previous cesarean section is undergoing a trial of labor and presents in active labor. During labor, there is fetal bradycardia and maternal tachycardia. Persistent suprapubic pain between contractions is also noted. On examination, the cervix is 8 cm dilated, and the vertex is at -1 station. What is the next best step in management?
Options:
Emergency lower segment cesarean section
Artificial rupture of membranes
Augment labor with oxytocin
Attempt instrumental vaginal delivery
Correct Answer: A) Emergency lower segment cesarean section
Q.6
Clinical Question:
In the repair of a mediolateral episiotomy, what is the correct order of tissue approximation during suturing?
Options:
Mucosa → Muscle → Skin
Skin → Mucosa → Muscle
Muscle → Skin → Mucosa
Skin → Muscle → Mucosa
Correct Answer: A) Mucosa → Muscle →
Q.7
Clinical Question:
A patient presents with 2 months of amenorrhea and an enlarged uterus. On examination, there is darkening of the areola, prominent Montgomery’s tubercles, a linea nigra is present, and there is bluish discoloration of the vagina on per-vaginal examination. How would you categorize these signs of pregnancy?
Options:
Presumptive signs of pregnancy
Probable signs of pregnancy
Positive signs of pregnancy
Diagnostic signs of pregnancy
Correct Answer: B) Probable signs of pregnancy
Q.8
Clinical Question:
Hydronephrosis due to the extension of a cervical tumor is a criterion for which FIGO stage of cervical cancer?
Options:
Stage IIIA
Stage IIIB
Stage IVA
Stage IVB
Correct Answer: B) Stage IIIB
Q.9
Clinical Question:
A woman presents with abdominal distension and ascites. On examination, the abdomen is enlarged, and CA-125 levels are elevated. Imaging shows a large multicystic ovarian mass with irregular septations. What is the most likely diagnosis?
Options:
Serous cystadenocarcinoma
Granulosa cell tumor
Simple serous cystadenoma
Mucinous cystadenoma
Correct Answer: A) Serous cystadenocarcinoma
Q.10
Clinical Question:
A woman develops atonic postpartum hemorrhage that does not respond to initial measures and medical management. What is the next best step in management that can be done in the labour room?
Options:
Intrauterine balloon tamponade
Uterine artery ligation
Internal iliac artery ligation
Compression sutures
Correct Answer: A) Intrauterine balloon tamponade
Q.11
Clinical Question:
A primigravida undergoing vaginal delivery develops shoulder dystocia after delivery of the fetal head. Which of the following is the correct sequence of maneuvers used in its management?
Options:
McRoberts → Rubin → Gaskin → Zavanelli
Zavanelli → McRoberts → Gaskin → Rubin
Rubin → McRoberts → Gaskin → Zavanelli
Gaskin → Rubin → McRoberts → Zavanelli
Correct Answer: A) McRoberts → Rubin → Gaskin → Zavanelli
Q.12
Clinical Question:
A woman, P2L2, with a history of difficult vaginal deliveries conducted by an untrained attendant, now presents with the complaint of “something coming out of her vagina.” On examination, the finding is as shown in the image below. Injury to which of the following ligaments is most likely responsible for this condition?
Options:
Sacrospinous ligament
Mackenrodt’s ligament
Broad ligament
Round ligament
Correct Answer: B) Mackenrodt’s ligament
Q.13
Clinical Question:
During an assisted breech delivery, the attending identified winging of the scapula and performed the following manoeuvre. Identify this.
Options:
Lovset maneuver
Burn-Marshall maneuver
Mauriceau-Smellie-Veit maneuver
Pinard’s maneuver
Correct Answer: A) Lovset maneuver
Q.14
Clinical Question:
A 55-year-old post-menopausal woman presents to the OPD for a routine BP checkup. Her BP was 170/100 mmHg. She also complains of a blood-stained discharge per vagina. What is the next best step in management?
Options:
Reassure her that some discharge is normal at this age
Immediate referral to a cardiologist before any further evaluation
Immediate pelvic examination, transvaginal sonography (TVS), and Pap smear
Start antihypertensive medication and observe for 1 week
Correct Answer: C) Immediate pelvic examination, transvaginal sonography (TVS), and Pap smear.
Q.15
Clinical Question:
A 46-year-old nulliparous woman presents with delayed cycles and heavy bleeding for the past 1 year. Transvaginal ultrasonography reveals an endometrial thickness of 18 mm. What is the next best step in management?
Options:
Start combined oral contraceptive pills
Schedule hysterectomy
Wait and watch for 6 months
Perform endometrial biopsy
Correct Answer: D) Perform endometrial biopsy
Q.16
Clinical Question:
A 65-year-old postmenopausal female presents with a chief complaint of vaginal bleeding for the past three months. She undergoes a hysterectomy, and the gross specimen is shown below. Based on the image and clinical scenario, which of the following is the most likely diagnosis?
Options:
Endometrial cancer
Fibroid
Endometriosis
Adenomyosis
Correct Answer: A) Endometrial cancer
Q.17
Clinical Question:
A woman presents for her first antenatal visit and reports that her LMP was approximately 2 months ago. Which ultrasound parameter is the most accurate for dating the pregnancy at this stage?
Options:
Biparietal Diameter (BPD)
Crown-Rump Length (CRL)
Femur Length (FL)
Abdominal Circumference (AC)
Correct Answer: B) Crown-Rump Length (CRL)
Q.18
Clinical Question:
A primigravida at 37 weeks presents with decreased fetal movements for one day. A Nonstress Test (NST) showed one acceleration in 20 minutes and no decelerations. What is the next step in management?
Options:
Continue NST for 40 minutes
Induce labour immediately
Emergency LSCS
Instrumental delivery
Correct Answer: A) Continue NST for 40 minutes
Q.19
Clinical Question:
A 42-year-old woman presents with chronic lower abdominal pain and dysmenorrhea. MRI is
as shown. What is the most likely diagnosis?
Options:
Intramural fibroid
Adenomyosis
Endometrial carcinoma
Endometriosis
Correct Answer: B) Adenomyosis
Q.20
Clinical Question:
A pregnant female gives a history of toxoplasma infection 5 years ago and currently tests positive for IgG antibodies. On examination, lymphadenopathy is noted. What is the next step in management?
Options:
Reassure and continue the pregnancy
Carry out an MTP
Counsel her about the potential teratogenic effects of the infection
Treat the female for toxoplasmosis
Correct Answer: A) Reassure and continue the pregnancy
NEET PG 2025 Ophthalmology Previous Year Questions
Q.1
Clinical Question:
A 15-year-old girl presents with a painless swelling in the right supraorbital region that has been gradually progressing over the past year. What is the most likely diagnosis?
Options:
Lacrimal gland mass
Dermoid cyst
Hemangioma
Epidermoid cyst
Correct Answer: B) Dermoid cyst
Q.2
Clinical Question:
A patient presents with guttate lesions in one eye and bullous keratopathy in the other eye. What is the most probable diagnosis?
Options:
Trichoma
Herpes keratitis
Fuchs endothelial dystrophy
Keratoconus
Correct Answer: C) Fuch’s endothelial dystrophy
Q.3
Clinical Question:
Which of the following statements regarding orbital cellulitis is true?
Options:
Ethmoidal sinusitis is the most common source of infection in all age groups
Topical broad-spectrum antibiotics are the mainstay of treatment
The inflammation is restricted anterior to the orbital wall
Patients characteristically present with proptosis, blurring of vision, normal pupillary and ocular movements
Correct Answer: A) Ethmoidal sinusitis is the most common source of infection in all age groups
Q.4
Clinical Question:
A 65-year-old male presents with complaints of a decrease in vision. There were white deposits on the anterior lens surface, seen during slit lamp examination. What is the most likely diagnosis?
Options:
Glaucomflecken with acute angle closure glaucoma
Pseudoexfoliation syndrome
iritis with pupillary deposits
Anterior capsule opacification
Correct Answer: B) Psedoexfoliation syndrome
Q.5
Non-clinical Question:
Which of the following conditions is treated using the modality shown in the image?
Options:
Keratoconus
Keratoglobus
Vogt’s limb striae
Corneal dystrophy
Correct Answer: A) Keratoconus
Q.6
Clinical Question:
Binocular single vision consists of which of the following components, corresponding to Image A and Image B, respectively?
Options:
Fusion and stereopsis
Fusion and simultaneous macular perception
Simultaneous macular perception and stereopsis
Simultaneous macular perception and fusion
Correct Answer: D) Simultaneous macularperception and fusion
NEET PG 2025 Orthopaedics Previous Year Questions
Question 1
Clinical question
A 26-year-old male presents with complaints of chronic lower back pain, which has been progressive for the past 1 year. He also experiences early morning stiffness lasting for 1.5 hours, which is relieved by exercise. He also gives a history of anterior uveitis. Which of the following investigations is most useful for early diagnosis of the underlying condition?
Options:
A) Anti-CCP
B) MRI of the sacroiliac joint
C) CT spine of the sacroiliac joint
D) Bone scan
Correct answer: B) MRI of sacroiliac joint
Question 2
Clinical question
A 66-year-old female presents with chronic lower back pain. An oblique lumbar spine X-ray is done and shown below. Based on the radiological findings, which of the following is the most likely diagnosis?
Options:
A) Spondylolysis
B) Spondylolisthesis
C) Crush vertebral fracture
D) Klippel Feil syndrome
Correct answer: A) Spondylolysis
Question 3
Clinical question
A 25-year-old man presents to the emergency department following a motorbike accident and is found to have a closed midshaft fracture of the left tibia. Six hours later, he develops severe leg pain that is disproportionate to the injury and worsens with passive dorsiflexion of the foot. The pain is not relieved by analgesics. On examination, dorsalis pedis and posterior tibial pulses are present, but there is no sensation over the first dorsal web space. What is the most appropriate next step in management?
Options:
A) Administer opioid analgesics and observation
B)Elevation of limb and observation
C) Immediate fasciotomy
D) Apply cast and follow-up
Correct answer: C) Immediate fasciotomy
Question 4
Clinical question
A 24-year-old male sustained a shaft of femur fracture after a road traffic accident, and internal fixation was done for the same. Two days later, he developed shortness of breath with confusion and a petechial rash. What is the most likely diagnosis?
Options:
A) Fat embolism
B) Tension pneumothorax
C) Air embolism
D) ARDS
Correct answer: A) Fat embolism
Question 5
Clinical question
A 70-year-old man undergoes routine blood work as part of a health check-up. He has no major complaints except for occasional bone pain. He denies weakness or recent fractures. On physical examination, no focal deficits are noted.
X-ray pelvis shows thickened cortices with areas of sclerosis and lysis.
What is the most likely diagnosis?
Options:
A) Osteomalacia
B) Primary hyperparathyroidism
C) Paget’s disease
D) Osteoporosis
Correct answer: C) Paget’s disease
NEET PG 2025 Pathology Previous Year Questions
Question 1
Non-clinical question:
Which of the following conditions follows the inheritance pattern shown in the given pedigree chart?
Options:
A) Achondroplasia
B) Kearns-Sayre syndrome
C) Williams syndrome
D) Prader-Willi syndrome
Correct answer: B) Kearns-Sayre syndrome
Question 2
Clinical question:
A patient presents with recurrent episodes of disseminated gonococcal infection. A joint aspirate during an episode of joint pain reveals Neisseria gonorrhoeae. Which of the following could be the underlying mechanism?
Options:
A)Myeloperoxidase deficiency
B) PMN cell chemotactic defect
C) Terminal complement deficiency
D) C2 deficiency
Correct answer: C) Terminal complement deficiency
Question 3
Clinical question
A patient presents with long limbs and ectopia lentis. His arm span is found to be greater than his height. Marfan syndrome is suspected. Which of the following gene defects is most likely responsible?
Options:
A) PLOD1
B) Elastin
C) Fibrillin
D) COLA1
Correct answer: C) Fibrillin
Question 4
Clinical question
A 45-year-old female presents with a 2-year history of progressive unilateral hearing loss, tinnitus, and ataxia. An MRI imaging of the brain reveals a well-defined tumour located in the cerebellopontine angle (CPA). A surgical resection is performed, and subsequent histopathological examination of the tumour reveals Antoni A and B areas. Which of the following is the most likely diagnosis?
Options:
A) Meningioma
B) Ependymoma
C) Schwannoma
D) Vestibular neuritis
Correct answer: C) Schwannoma
Question 5
Clinical question
An elderly male presents with cervical lymph node enlargement and increased bleeding tendency. Bone marrow examination reveals >25% blasts, and the peripheral smear is as shown below. Which of the following cytogenetic abnormalities is most likely associated with this condition?
Options:
A) Inv (16)
B) t(15;17)
C) t(8;21)
D) t(9;22)
Correct answer: B) t(15;17)
Question 6
Clinical question
An elderly male presents with progressive, painless testicular swelling. Gross examination of the testis shows a multinodular, homogeneous, gray-white mass without haemorrhage or necrosis. Histopathological examination is shown below. What is the most likely diagnosis?
Options:
A) Yolk sac tumour
B) Seminoma
C) Embryonal carcinoma
D) Leydig cell tumour
Correct answer: B) Seminoma
Question 7
Clinical question
A patient presents with a midline neck swelling. Histology showed amyloid deposition, and immunohistochemistry is positive for synaptophysin, chromogranin, and TTF‑1. Which of the following is the most likely diagnosis?
Options:
A) Papillary thyroid cancer
B) Medullary thyroid cancer
C) Follicular thyroid cancer
D) Anaplastic thyroid cancer
Correct answer: B) Medullary thyroid cancer
Question 8
Non-clinical question
A gross specimen of the liver shows a well-circumscribed lesion, as shown below. What is the most likely diagnosis?
Options:
A) Hepatocellular adenoma
B) Hepatocellular carcinoma
C) Focal nodular hyperplasia
D) Regenerative nodule
Correct answer: C) Focal nodular hyperplasia
Question 9
Clinical question
An elderly male presents with bilateral cervical lymph node enlargement. Histopathological examination reveals small cleaved cells as well as larger cells with open chromatin. Immunohistochemistry reveals CD10-positive and BCL2-positive cells. Which of the following cytogenetic abnormalities is most commonly associated with this condition?
Options:
A) t(11;18)
B) t(14;18)
C) t(11;14)
D) t(8;14)
Correct answer: B) t(14;18)
Question 10
Non-clinical question
Which of the following are caspase-mediated forms of cell death?
Options:
A) Apoptosis and necroptosis
B) Apoptosis and necrosis
C) Apoptosis and pyroptosis
D) Apoptosis and ferroptosis
Correct answer: C) Apoptosis and pyroptosis
Question 11
Clinical question
A patient presents with mild anaemia and jaundice. Examination reveals splenomegaly. Laboratory findings show an elevated mean corpuscular haemoglobin concentration (MCHC). His father has also had a similar clinical history. What is the most likely diagnosis?
Options:
A) Hereditary spherocytosis
B) Iron deficiency anaemia
C) Autoimmune hemolytic anaemia
D) Thalassemia minor
Correct answer: A) Hereditary spherocytosis
Question 12
Clinical question
An 8-year-old child presents with progressive vision loss, and an MRI was done, which showed a suprasellar mass. Histopathology of the mass showed the findings of palisading epithelium and wet keratin. Which among the following is the most likely diagnosis?
Options:
A) Craniopharyngioma
B) Pituitary adenoma
C) Rathke’s cleft cyst
D) Meningioma
Correct answer: A) Craniopharyngioma
Question 13
Clinical question
An elderly patient presents with fatigue, generalised lymphadenopathy, and hepatosplenomegaly. After examination and laboratory investigations, a diagnosis of CLL is made. Which of the following laboratory techniques is most useful to compare and quantify CD markers on cells?
Options:
A) ELISA
B) Western blot
C) Flow cytometry
D) Immunohistochemistry
Correct answer: C) Flow cytometry
Question 14
Non-clinical question
Antimitochondrial antibody (AMA) positivity is most strongly associated with which of the following conditions?
Options:
A) Primary biliary cholangitis
B) Autoimmune hepatitis
C) Sarcoidosis
D) Wilson’s
Correct answer: A) Primary biliary cholangitis
Question 15
Clinical question
A patient presents with a 1‑month history of cough, chest pain, and dyspnea. Imaging reveals bilateral hilar lymphadenopathy. Biopsy of a mediastinal lymph node shows non‑caseating granulomas containing stellate inclusions. Which of the following is the most likely diagnosis?
Options:
A) Tuberculosis
B) Sarcoidosis
C) Lung cancer
D) Hypersensitivity pneumonitis
Correct answer: B) Sarcoidosis
Question 16
Clinical question
A 45-year-old man presents with rapidly progressive swelling, pain, foul-smelling discharge, and discolouration of the hand following a traumatic injury, as shown in the image given below. What is the most likely diagnosis?
Options:
A) Wet gangrene
B) Dry gangrene
C) Infectious tenosynovitis
D) Raynaud’s phenomenon
Correct answer: A) Wet gangrene
Question 17
Clinical question
A middle-aged woman presents with dry eyes and dry mouth. Laboratory tests reveal positive anti-Ro (SSA) and anti-La (SSB) antibodies. What is the most likely underlying pathological mechanism?
Options:
A) Destruction of exocrine glands by neutrophils
B) IgE-mediated hypersensitivity reaction
C) Lymphocytic infiltration and destruction of salivary and lacrimal glands
D) Deposition of amyloid in salivary glands
Correct answer: C) Lymphocytic infiltration and destruction of salivary and lacrimal glands
Question 18
Clinical question
A 36-year-old male patient with gluten sensitivity presents with intensely itchy, grouped vesicular lesions on the extensor surfaces. A skin biopsy with direct immunofluorescence shows the following finding. What is the most likely diagnosis?
Options
A) Bullous pemphigoid
B) Pemphigus vulgaris
C) Dermatitis herpetiformis
D) Psoriasis
Correct answer: C) Dermatitis herpetiformis
Question 19
Clinical question
A patient presents with a persistent red lesion on the lateral border of the tongue. Biopsy confirms squamous cell carcinoma. Which of the following viral infections is most strongly associated with this malignancy?
Options:
A) Epstein–Barr virus
B) Cytomegalovirus
C) Herpes simplex virus
D) Human papillomavirus
Correct answer: D) Human papillomavirus
Pediatrics
NEET PG 2025 Pediatrics Previous Year Questions
Question 1
Clinical question
A 2-year-old child is brought to the emergency room with a generalised seizure following a high-grade fever. What is the first-line drug of choice for seizure control in this
setting?
Options:
A) Diazepam
B) Ethosuximide
C) Valproate
D) Phenytoin
Correct answer: A) Diazepam
Question 2
Clinical question
A 3-year-old boy presents with fever and cough. A chest x-ray was done, which showed the following findings. Which of the following is the most likely underlying pathology?
Options:
A) Right upper lobe collapse
B) Right upper lobe abscess
C) Right upper lobe consolidation
D) Bronchogenic carcinoma
Correct answer: C) Right lobe consolidation
Question 3
Clinical question
A pregnant woman is diagnosed with HIV infection at 34 weeks of gestation. Her viral load was 1200 copies/mL, and she was then started on ART. She delivers a 2.5 kg term baby at 38 weeks. What is the most appropriate postnatal prophylaxis for the newborn?
Options:
A) Both nevirapine and zidovudine for 12 weeks, along with exclusive breast milk feeding
B) Nevirapine for 6 weeks with exclusive breastfeeding
C) No breastfeeding and initiate exclusive formula feeding
D) Nevirapine prophylaxis for 6 weeks
Correct answer: A) Both nevirapine and zidovudine for 12 weeks, along with exclusive breast milk feeding
Question 4
Clinical question
Which of the following is most likely in a neonate presenting with congenital hypothyroidism, decreased T3 and T4 levels, decreased radioactive iodine uptake, but a normal thyroid on ultrasound?
Options:
A) Thyroid dyshormonogenesis
B) Thyroid agenesis
C) Iodine deficiency
D) Defect in iodine transport
Correct answer: D) Defect in iodine transporter
Question 5
Clinical question
During examination of a neonate, an index finger was found missing along with multiple deformities of all four limbs, as shown in the image given below. Which of the following is the most likely diagnosis?
Options:
A) Arthrogryposis multiplex congenita
B) CTEV
C) Amniotic band syndrome
D) Syndactyly
Correct answer: C) Amniotic band syndrome
NEET PG 2025 Pharmacology Previous Year Questions
Question: 1
Clinical question
A 38-year-old female presents with a pounding headache, palpitations, and sweating for 2 months. Each episode lasts for 20 minutes and is triggered by stress or physical exertion. Her pulse is 112/min, BP is 180/100 mm Hg, and urine shows elevated VMA and normetanephrines. MRI reveals a right adrenal mass. Which drug can be used both pre- and intra-operatively?
Options: A) Esmolol B) Phenoxybenzamine C) Nifedipine D) Clonidine
Correct Answer: B) Phenoxybenzamine
Question 2
Non-clinical question
In the given cardiac action potential graph, identify the phase where amiodarone acts.
Options:
0
1
2
3
Correct Answer: D) 3
Question: 3
Clinical question
A patient with tumour lysis syndrome has elevated uric acid levels. What is the mechanism of action of pegloticase?
Options:
Oxidises uric acid
Hydrolyses uric acid
Inhibits xanthine oxidase
Inhibits URAT-1 transporters in the kidney
Correct Answer: A) Oxidises uric acid
Question: 4
Clinical question
A female patient with HIV infection (CD4 count 150 cells/mm³) was newly diagnosed with rifampicin-resistant tuberculosis. What anti-tubercular treatment regimen should be initiated, and which HIV-related complication should you look out for?
Which of the following drugs is most appropriate to be started in a diabetic patient with an HbA1c of 8.8 mmol/L with heart failure who is already on metformin and insulin glargine?
Options:
Pioglitazone
Empagliflozin
Glibenclamide
Sitagliptin
Correct Answer: B) Empagliflozin
Question 6
Clinical question
A 32-year-old woman with a BMI of 38 kg/m² undergoes an elective lower segment cesarean section (LSCS) at 35 weeks due to preeclampsia. Which of the following is the most appropriate pharmacological method for DVT prophylaxis in this patient?
Options:
Aspirin
Clopidogrel
Warfarin
LMWH
Correct Answer: D) LMWH
Question 7
Clinical question
What is the mechanism of renal calculi formation in a patient on Hydrochlorothiazide?
Options:
Increased calcium excretion
Decreased calcium excretion
Increased oxalate absorption
Decreased citrate excretion
Correct Answer: D) Decreased citrate excretion
Question 8
Non-clinical question
In the Pritchard regimen for the management of eclampsia, what is the loading dose of magnesium sulfate?
Options:
10
14
4
20
Correct Answer: B) 14
Question 9
Clinical question
A patient is diagnosed with paroxysmal supraventricular tachycardia and requires prophylaxis for the same. Which of the following drugs is appropriate for this patient?
Options:
IV adenosine
IV esmolol
Oral phenytoin
Oral verapamil
Correct Answer: D) Verapamil
Question 10
Clinical question
A female diagnosed with migraine presents to the OPD and complains of 4-5 episodes per month, with each episode lasting 24-48 hours. She also experiences anxiety and palpitations. She experiences partial pain relief with OTC NSAIDs and was started on sumatriptan prophylaxis, but developed chest tightness and flushing. She has no history of cardiac illnesses, but there is a positive family history of coronary artery disease. Which of the following drugs can be used for prophylaxis in this patient?
Options:
Naratriptan
Propranolol
Topiramate
Ergotamine
Correct Answer: B) Propranolol
Question 11
Clinical question
A 60-year-old man with chronic kidney disease presents with complaints of increasing
fatigue, dyspnea on exertion, and signs of congestive heart failure. On evaluation, he is found to have anaemia. Which of the following drugs is appropriate for this patient?
Options:
Parenteral iron
Folic acid
Filgastrim
Darbepoietin-alpha
Correct Answer: D) Darbepoietin-alpha
Question 12
Non-clinical question
Benralizumab, a monoclonal antibody used to treat asthma, acts against which of the following?
Options:
IL-1
IL-4
IL-5
TNF alpha
Correct Answer: C) IL-5
Question 13
Clinical question
A patient presents with complaints of patches in the oral mucosa, as shown below, with a burning sensation on taking spicy food for the past 6 months. Which of the following drugs can cause this side effect?
Options:
A) Ciprofloxacin
B) Fluconazole
C) Beta blockers
D) Lithium
Correct Answer: C) Beta blockers
Question 14
Clinical question
A patient presents with symptoms of GERD. Which of the following drugs increases the tone of the LES and increases gastric emptying?
Options:
Sodium alginate
Pantoprazole
Metoclopramide
Vonoprazan
Correct Answer: C) Metoclopramide
NEET PG 2025 Physiology Previous Year Questions
Q.1
Clinical Question:
A 22-year-old college student flies to Leh, which is at an altitude of 3700 m above sea level. She experiences nausea, headache, mental confusion, and blurred vision. Which of the following is the underlying mechanism for these findings?
Options:
Increase in sympathetic activity leading to vasoconstriction of cerebral vessels, leading to transudation of fluid
Decrease in PaO₂ leading to vasoconstriction of cerebral vessels, leading to transudation of fluid
Decrease in PaO₂ leading to vasodilatation of cerebral vessels, leading to transudation of fluid
Decrease in pH leading to vasodilatation of cerebral vessels, leading to transudation of fluid
Correct Answer: C) Decrease in PaO₂ leading to vasodilatation of cerebral vessels, leading to transudation of fluid
Q.2
Clinical Question:
A woman presents with complaints of secondary amenorrhea and infertility. Investigations revealed a microadenoma of the pituitary gland and hyperprolactinemia. What is the underlying mechanism by which hyperprolactinemia causes these complaints?
Options:
Antagonistic effect of prolatin on estrogen receptors
Decreased GnRH secretion from hypothalamus
Increased secretion of FSH
Increased secretion of LH
Correct Answer: B) Decreased GnRH secretion from hypothalamus
Q.3
Clinical Question:
A patient presents with nausea, vomiting, and muscle cramps. Lab tests reveal hyponatremia and hyperkalemia. On examination, there is hyperpigmentation of the skin. Which of the following hormones is directly responsible for the hyperpigmentation?
Options:
ACTH
Cortisol
Aldosterone
Renin
Correct Answer: A) ACTH
Q.4
Non-clinical Question:
Which of the following sarcomeres corresponds to point B on the graph?
Options:
A)
B)
C)
D)
Correct Answer: Option C
Q.5
Non-clinical Question:
If there is no net transudation across a capillary with a capillary hydrostatic pressure of 18 mm Hg, capillary oncotic pressure of 27 mm Hg, and interstitial oncotic pressure of 7 mm Hg, what should be the interstitial hydrostatic pressure?
Options:
2 mm Hg
-2 mm Hg
0 mm Hg
1 mm Hg
Correct Answer: B) -2 mm Hg
Q.6
Non-clinical Question:
The given graph shows PCo2 and PO2 of the right lung along with ventilation and perfusion ratio. Which point on the graph represents V/Q ratio if there is a complete block of the blood supply at alveolar level of right lung due to pulmonary embolism?
Options:
A
B
D
E
Correct Answer: D) E
NEET PG 2025 PSM Previous Year Questions
Question 1
Non-Clinical Question
According to the population strategy for prevention of cardiovascular disease, what is the recommended dietary allowance of cholesterol per day?
Options:
A) 100mg/1000 kcal
B) 200mg/1000 kcal
C) 300mg/1000 kcal
D) 400mg/1000 kcal
Correct Answer: A) 100mg/1000 kcal
Question 2
Clinical Question
A 50-year-old man from Chittoor, Andhra Pradesh, presents to the OPD with features of
osteoporosis. Examination reveals outward bending of both legs. Which of the following is not used in his management?
Options:
A) Fluoride supplementation
B) Make a surface running water source available
C) Change the source of water
D) Add alum and lime to water
Correct Answer: A) Fluoride supplementation
Question 3
Non-Clinical Question
Under Weekly Iron and Folic Acid Supplementation, what dose of iron and folic acid is given to girls 10-19 years of age:
Options:
A) 60mg elemental iron + 100mcg FA
B) 100mg elemental iron + 100mcg FA
C) 100mg elemental iron + 500mcg FA
D) 60mg elemental iron + 500mcg FA
Correct Answer: C) 100mg elemental iron + 500mcg FA
Question 4
Non-Clinical Question
There is a report of toxic fumes leaking from a nearby chemical factory. What should be your immediate action?
Options:
A) Close all doors and windows and seal your home with plastic/tape
B) Open all windows and try to ventilate the house
C) Stay inside and wait for further instructions
D) Immediately run outside without checking the wind direction or alerts
Correct Answer: A) Close all doors and windows and seal your home with plastic/tape
Question 5
Non-Clinical Question
The interval between a host receiving an infection and the period of attaining maximum infectivity is called
Options:
A) Communicable period
B) Incubation period
C) Generation time
D) Serial interval
Correct Answer: C) Generation time
Question 6
Non-Clinical Question
In an experimental study, which of the following is the correct sequence of steps?
1. Randomisation
2. Manipulation
3. Statistical analysis
4. Follow-up (checked)
Options:
A) 2,3,1,4
B) 1,2,3,4
C) 2,1,4,3
D) 1,2,4,3
Correct Answer: D) 1, 2, 4, 3
Question 7
Non-Clinical Question
For a population of 70,00,000 with 30% of it belonging to the slum population, how many Urban PHCs are required for the slum population according to NUHM?
Options:
A) 22
B) 42
C) 32
D) 52
Correct Answer: B) 42
Question 8
Non-Clinical Question
In a de facto census, individuals are counted based on:
Options:
A) Place of birth
B) Place on the date of enumeration
C) Place of employment
D) Usual place of residence
Correct Answer: B) Place on date of enumeration
Question 9
Non-Clinical Question
Which of the following tests is most appropriate to compare the mean hemoglobin levels between two independent groups?
Options:
A) Paired T test
B) Unpaired T-test
C) ANOVA
D) Chi-square test
Correct Answer: B) Unpaired T-test
Question 10
Clinical Question
A patient diagnosed with fever and dry cough was confirmed to have COVID-19. He was admitted to a district hospital and later died in the hospital. The death was registered 7 days later. What type of surveillance does this represent?
Options:
A) Active surveillance
B) Passive surveillance
C) Syndromic surveillance
D) Sentinel surveillance
Correct Answer: B) Passive surveillance
Question 11
Non-Clinical Question
Which of the following vaccines will you use in your PHC?
Options:
A) 1, 2
B) 2, 3
C) Only 1
D) 3, 4
Correct Answer: A) 1, 2
Question 12
Non-Clinical Question
A mosquito larva is examined under a hand lens. It showed no siphon tube, abdominal palmate hairs are present, and the larvae rest parallel to the water surface. What is the likely mosquito species?
Options:
A) Culex
B) Anopheles
C) Aedes
D) Mansonia
Correct Answer: B) Anopheles
Question 13
Non-Clinical Question
A study found that breast cancer screening increases the 5-year survival rate, but there is no change in overall mortality. What type of bias does this suggest?
Options:
A) Berksoniana bias
B) Survival bias
C) Lead time bias
D) Detection bias
Correct Answer: C) Lead time bias
Question 14
Non-Clinical Question
During a community medicine demonstration, medical students are instructed to perform the Nalgonda technique. Each student is asked to bring two material bags from the set shown below:
Bag A – Alum
Bag B – Gypsum
Bag C – Charcoal
Bag D – Lime
Which combination of bags is required to perform the Nalgonda technique correctly?
Options:
A) A and D
B) B and C
C) A and B
D) B and C
Correct Answer: A) A and D
Question 15
Clinical Question
A 3-year-old child presents with bowing of the legs. Which of the following nutritional supplementation programs specifically covers children under 6 years of age?
Options:
A) ICDS (Integrated Child Development Services)
B) Mid-Day Meal Scheme
C) Anemia Mukt Bharat
D) National Nutrition Deficiency Control Programme
Correct Answer: A) ICDS (Integrated Child Development Services)
Question 16
Non-Clinical Question
A new community-level intervention is being evaluated. Researchers allocated 20 Primary Health Centres (PHCs) to receive standard care, and another 20 PHCs to receive the new community intervention. What is the most appropriate classification of this study?
Options:
A) Quasi-experimental study
B) Cluster RCT
C) Case-control study
D) Cross-sectional study
Correct Answer: B) Cluster RCT
Question 17
Non-Clinical Question
Which of the following is the most appropriate method used in health planning to assess whether objectives and targets are being fulfilled and to evaluate the quality of outcomes?
Options:
A) Supervision
B) Monitoring
C) Evaluation
D) Planning
Correct Answer: C) Evaluation
Question 18
Non-Clinical Question
A 7-month-old child is on complementary feeding along with continued breastfeeding. The child is given a khatori of semi-solid millet food. What is the recommended frequency and amount per day?
Options:
A) ½ to 1 khatori, 3 times per day
B) ½ to 1 khatori, 4 times per day
C) ½ to 1 khatori, 5 times per day
D) ½ to 1 khatori, 6 times per day
Correct Answer: A) ½ to 1 khatori, 3 times per day
NEET PG 2025 Psychiatry Previous Year Questions
Question 1
A 35-year-old man was arrested for attacking a coworker. During interrogation, he appears dishevelled and expresses paranoid delusions, stating he was not in the right state of mind. Which of the following is the most appropriate next step?
Options:
A) Release him as he was not in the right state
B) Arrange a psychiatric consultation to assess fitness for trial
C) Proceed to trial
D) Convict him
Correct answer: B) Psychiatric consultation to assess fitness for trial
Question 2
Clinical question
A 68-year-old woman with metastatic breast cancer presents with severe dyspnea. The oncology team determines that chemotherapy and radiotherapy would provide no benefit. However, the patient’s daughter insists on “doing everything,” including ICU admission and ventilator support. Which of the following is the most appropriate next step?
Options:
A) Admit to the ICU and proceed with aggressive management
B) Discharge her as there is no further care that can be provided, and admit her to hospice
C) Start placebo treatment to relieve anxiety
D) Gather a family meeting to assess expectations and patient preferences
Correct answer: D) Gather a family meeting to assess expectations and patient preferences
Question 3
Clinical question
A schizophrenia patient on haloperidol who was responding well for the last 2 years now presents with orofacial dyskinesia, choreiform, tic-like movements, and possible dystonia. What is the most probable diagnosis and appropriate treatment?
Options:
A) Tardive dyskinesia – Valbenazine
B) Akathisia – Propranolol
C) Perioral tremor – Amantadine
D) Acute dystonia – Ropinirole
Correct answer: A) Tardive dyskinesia – Valbenazine
Question 4
Clinical question
A 34-year-old man is brought to the casualty and appears confused. After extensive efforts by a social worker, it was discovered that he is from a nearby village and ended up in the current location after a massive earthquake at his place. He has no recollection of his identity or how he ended up in the current location. Which of the following is the most likely diagnosis?
Options:
A) Dissociative amnesia
B) Dissociative personality disorder
C) Dissociative fugue
D) Transient global amnesia
Correct answer: C) Dissociative fugue
Question 5
Clinical question
A 20-year-old girl underwent a traumatic experience two weeks ago after witnessing a road traffic accident and the death of her father. She now experiences flashbacks of the event. Which of the following is the most likely diagnosis?
Options:
A) Post-traumatic stress disorder
B) Dissociative disorder
C) Acute stress disorder
D) Major depressive disorder
Correct answer: C) Acute stress disorder
Question 6
Clinical question
An individual comes to the OPD to talk about his friend Mr. K. Mr. K is extremely perfectionistic and often misses deadlines because of this. He has been described as “rigid” since adolescence and is unable to discard items even without sentimental value. Mr. K denies having any problems. Which of the following best describes his personality?
A patient sitting outside his home believes that whenever a bird is chirping, he has to follow the bird. He believes that he is getting these instructions from God and that he will be harmed if he does not comply. What is the most likely diagnosis?
Options:
A) Sudden delusional idea
B) Delusional perception
C) Delusional reference
D) Visual hallucination
Correct answer: B) Delusional perception
NEET PG 2025 Radiology Previous Year Questions
Q.1
Clinical Question:
A 45-year-old male presented with difficulty swallowing, weight loss, and a chest X-ray showing associated bronchiectasis. The patient undergoes the contrast study shown below. What is the investigation of choice to confirm the diagnosis?
Options:
Manometry
CECT chest
Upper GI endoscopy
Esophagogram
Correct Answer: A) Manometry
Q.2
Clinical Question:
A 50-year-old male presents with right flank pain. A contrast-enhanced CT scan of the abdomen reveals the findings as shown below. Based on the clinical presentation and CT image, what is the most likely diagnosis?
Options:
Gall bladder cancer
Renal carcinoma
Retroperitoneal tumor
Left lobe liver abscess
Correct Answer: B) Renal carcinoma
Q.3
Clinical Question:
A newborn is admitted to the NICU in the first 24 hours of birth with severe dyspnea/respiratory distress. A chest x-ray is done, which is shown below. Which of the following is the most likely diagnosis?
Options:
Congenital diaphragmatic hernia
Congenital Pulmonary airway malformation
Loculated pneumothorax
Congenital lobar emphysema
Correct Answer: A) Congenital diaphragmatic hernia
Q.4
Clinical Question:
A 50-year-old male presents with a right-sided neck swelling, which is pulsatile in nature and is compressible, refilling on removal of pressure. A CT-angiogram was performed and is shown below. Which of the following is the most likely diagnosis?
Options:
Carotid body tumour
Carotid aneurysm
AV fistula
Hemangioma
Correct Answer: A) Carotid body tumour
Q.5
Clinical Question
Identify the correct features of the investigation shown in the given image.
Options:
Invasive and can be a therapeutic treatment for bladder calculi
Non-invasive and used to diagnose ureteropelvic junction obstruction
Non-invasive and gold standard for diagnosing bladder cancer
Requires percutaneous access to the renal pelvicalyceal system
Correct Answer: B) Non-invasive and used to diagnose ureteropelvic junction obstruction
Q.6
Clinical Question:
A 32-year-old female presents with recurrent headaches, and an MRI brain was done as shown below. What is the most likely diagnosis?
Options:
Glioma
Ependymoma
Meningioma
Pilocytic astrocytoma
Correct Answer: C) Meningioma
Q.7
Clinical Question:
An 8-year-old presents to the orthopedics OPD with complaints of a painless limp for the past 1 week. An X-ray is done and is shown below. Which of the following is the most likely diagnosis?
Options:
Developmental Dysplasia of the Hip
Slipped Capital Femoral Epiphysis
Perthes disease
D) Tuberculosis hip
Correct Answer: C) Perthes disease
NEET PG 2025 Surgery Previous Year Questions
Question 1
Clinical question
A 65-year-old male with a stab injury to the abdomen presents to the casualty. Examination reveals abdominal tenderness and guarding. Which of the following is the next best step in management?
Options:
A) Peritoneal wash
B) Emergency laparotomy
C) Ultrasound of the abdomen
D) CT abdomen
Correct answer: Emergency laparotomy
Question 2
Clinical question
A 25-year-old with a 5-year history of unilateral varicose veins on the left leg presents to the surgery OPD as shown below. Identify the correct statement regarding this condition.
Options:
A) The most common cause is pelvic tumours
B) Graded as C6
C) Recommended treatment is sclerotherapy in all cases
D) It can lead to eczema and pigmentation
Correct answer: D) It can lead to eczema and pigmentation
Question 3
Clinical question
Identify the stage of breast cancer depicted in the image below.
Options:
A) T4b
B) T4d
C) T4c
D) T3
Correct answer: B) T4D
Question 4
Non-clinical question
The fistula marked in the image given below is of which type according to the Park classification?
Options:
A) Transsphincteric
B) Intersphincteric
C) Suprasphincteric
D) Extrasphincteric
Correct answer: A) Transsphincteric
Question 5
Non-clinical question
Identify the type of knot shown in the image.
Options:
A) Surgeon’s knot
B) Granny’s knot
C) Square knot
D) Slip knot
Correct answer: A) Surgeon’s knot
Question 6
Non-clinical question
Identify the type of suture material shown in the image
Options:
A) Monofilament
B) Polyfilament
C) Organic
D) Braided
Correct answer: A) Monofilament
Question 7
Clinical question
A 25-year-old patient had an RTA and was initially conscious but later became unconscious and subsequently died. On postmortem examination, multiple petechial haemorrhages were seen in the corpus callosum, but no significant findings were seen on CT brain. What is the most likely diagnosis?
Options:
A) Subarachnoid hemorrhage
B) Diffuse axonal injury
C) Subdural hematoma
D) Extradural hematoma
Options: B) Diffuse axonal injury
Question 8
Non-clinical question
Identify the type of bile duct injury shown in the image based on the Strasberg classification.
Options:
A) Type A
B) Type B
C) Type C
D) Type D
Correct answer: A) Type A
Question 9
Clinical question
A patient with jaundice, anorexia, and weight loss for 2 months. The gall bladder is palpable, soft, and non-tender. What is the most likely diagnosis?
Options:
A) Hepatocellular carcinoma
B) Gall bladder cancer
C) Pancreatic head cancer
D) Choledocholithiasis
Correct answer: C) Pancreatic head cancer
Question 10
Clinical question
A 40-year-old had the following structure resected. Which of the following complications can be seen 4 days later?
Options:
A) Deviation of the angle of the mouth
B) Carpopedal spasm
C) Neck hematoma
D) Migratory thrombophlebitis
Correct answer: B) Carpopedal spasm
Question 11
Non-clinical question
What is true about the procedure shown in the image?
Options:
A) Done in circumferential burns
B) The image shows a skin graft
C) Done for quick healing
D) Incisions on the upper limb are done to avoid major vessels
Correct answer: A) Done in circumferential lesions
Question 12
Clinical question
A 7-year-old boy presents with progressive non-retractable foreskin and tense, white preputial skin. What is the diagnosis?
Options:
A) Recurrent balanoposthitis
B) Urethral meatus stenosis
C) Paraphimosis
D) Balanitis xerotica obliterans
Correct answer: D) Balanitis xerotica obliterans
Commonly Asked Questions about NEET PG PYQs
1. Why should I practice NEET PG Previous Year Questions (PYQs)?
Practicing PYQs helps you understand the exam’s structure, focus areas, and level of difficulty. It also sharpens problem-solving skills and improves time management.
2. How many years of NEET PG PYQs should I solve?
It’s best to solve at least the last 5–7 years of PYQs. This gives you a clear view of recurring patterns and important subjects.
3. Are PYQs alone enough to crack NEET PG?
No. PYQs are a valuable revision tool, but should be combined with standard textbooks, conceptual study, and mock tests for complete preparation.
4. When should I start solving PYQs?
You can start early after finishing basic concepts, but they’re especially useful during revision phases. Multiple revisions of PYQs enhance recall and confidence.
5. Do NEET PG questions repeat from previous years?
Exact questions rarely repeat, but concepts and themes often do. Practicing PYQs ensures you don’t miss out on these recurring areas.
6. How do PYQs improve performance on exam day?
By solving PYQs in a timed setting, you get familiar with the exam format, manage stress better, and reduce last-minute surprises.
7. Where can I download previous years’ questions from?
Instead of searching multiple platforms for PYQs, get it all in one place with DocTutorials. Our QBank of 12,000+ MCQs, including PYQs, gives you exactly what you need to master the exam.
8. Will I get solutions for the NEET PG question papers?
With DocTutorials V5 QBank, all 12,000+MCQs & IBQs come with clear, exam-oriented explanations for both correct and incorrect options, integrated with concepts and PYQs—ensuring deep conceptual clarity, better pattern recognition, and fewer repeat mistakes
Making the correct career choice after earning an international medical degree is important to Indian and OCI graduates intending to…
Maharashtra NEET PG Counselling: Overview, Eligibility, and Registration Process
Securing a postgraduate medical seat in India can be competitive. Postgraduate medical education is popular in Maharashtra, and the state has reputable government and private colleges with strong academic and clinical exposure.
Admissions to MD, MS, and PG Diploma seats are based on counselling by the Maharashtra Common Entrance Test Cell. The merit-based process involves the NEET PG rank, domicile, reservation, and seat availability in the various rounds.
Continue reading to know all the details of the Maharashtra NEET PG Counselling, such as eligibility, necessary dates, and registration process.
Overview of Maharashtra NEET PG Counselling
The State Common Entrance Test Cell of Maharashtra is in charge of M.D, M.S, and PG Diploma admissions under the state and private quota under the Maharashtra NEET PG counselling, while the medical counselling committee is in charge of the All India Quota.
Ace Your NEET PG Prep With DocTutorials NEET PG Online Live Power Pack
The NEET PG for MD, MS, and PG Diploma seats is conducted by the State Common Entrance Test Cell, Maharashtra. The CET Cell regulates counselling for 50% state quota seats in government and corporation medical colleges, and for all seats in private and minority colleges.
The remaining government college seats are allocated under the All India Quota (AIQ), which is administered separately by the Medical Counselling Committee at the national level. All recognised postgraduate medical courses affiliated to Maharashtra University of Health Sciences (MUHS), Nashik, and other state universities are included in the state counselling process.
The CET Cell annually publishes a comprehensive information brochure, seat plan, and counselling plan. Maharashtra has a reservation policy that includes categories for OBC, SC, ST, and EWS. Only those who have qualified in NEET PG and wish to appear in the Maharashtra state merit list are eligible to participate in the counselling process.
Eligibility Criteria for NEET PG Counselling in Maharashtra
Maharashtra NEET PG counselling requires a valid NEET PG score, an MBBS in an NMC-recognised Indian college, an internship, and registration by the National Medical Commission or the Maharashtra Medical Council.
Maharashtra follows standard NEET PG eligibility criteria with a few state-specific conditions:
Candidates must have a valid NEET PG score.
Candidates must possess an MBBS degree from an NMC-recognised Indian college.
Candidates must complete a 12-month internship.
Candidates must hold a permanent or provisional MBBS certificate.
Candidates must register with the National Medical Commission or the Maharashtra Medical Council, which is also mandatory.
Applicants with an MBBS obtained from foreign countries are not eligible to apply for Maharashtra NEET PG seats.
Choice filling is restricted to individuals on the official state merit list. No special age restriction exists; however, NMC norms must be satisfied, and in-service doctors must practice according to the in-service quota (where necessary).
Maharashtra NEET PG Counselling: Registration Process and Important Dates
Registration for Maharashtra NEET PG counselling is conducted online through the State CET Cell. Candidates need to register, pay fees, and may upload documents before locking their preferences.
Applicants should apply online on the State Common Entrance Test Cell, Maharashtra portal, within the stipulated time, which is most often announced in October or November.
Registration involves the applicant creating an account, paying the counselling fee, providing the essential documents, and completing a form before the stipulated deadline. Once the choice locking is done, the CET Cell releases the seat matrix and draws the provisional allotment list.
Selected candidates are then expected to report to their assigned college to be admitted in accordance with the actual counselling schedule.
The table below is a close reference of the counselling schedule of Rounds 1 and 2 in Maharashtra (2025) according to the CET Cell notification:
Event
Round 1 Dates (2025)
Round 2 Dates (2025)
Seat Matrix Publication
25 Nov 2025
15 Dec 2025
Online Choice Filling
25–27 Nov 2025
15–17 Dec 2025
Provisional Selection List
28 Nov 2025
19 Dec 2025
Reporting & Verification at College
29 Nov–3 Dec 2025
20–24 Dec 2025
For exact dates, always visit the CET Cell website. Missing a deadline (e.g., filling out a choice or reporting a choice) may result in the loss of a seat. Notices and counselling updates (e.g., updated schedules or new rounds) are also published by the CET Cell.
Maharashtra NEET PG Counselling Fees and Security Deposit
Financial preparation is a necessary component of the Maharashtra NEET PG counselling. This section describes the non-refundable application fees and the organised security deposit to attend the seat allocation rounds.
Refer to the table below for the fee structure for different categories:
Fee Type
Amount (₹)
Applicable To
Remarks
Application / Registration Fee
₹3,000
All candidates
Non-refundable; payable during online registration
Security Deposit – Government College
₹25,000
General category candidates
Refundable after completion of admission formalities
Note: The allotted college retains the security deposit and may forfeit it if the student fails to adhere to admission rules. Applicants are required to keep fee receipts to verify them when reporting.
Maharashtra NEET PG Counselling: Seat Matrix and Participating Colleges
The State Common Entrance Test Cell, Maharashtra, releases a seat matrix before each round. In 2025, Maharashtra offered 2,510 MD/MS seats (1,522 government and 988 private) and 16 PG Diploma seats. Applicants are advised to study the round-wise matrix and then complete the selections.
Before every round of counselling, the CET Cell publishes a list of available seats per college, per course, and per category (General, SC and ST, OBC, EWS, in-service, etc.). For 2025, Maharashtra provided 1,522 MD/MS in government colleges, 988 in private/minority colleges, and 16 seats for the PG Diploma, for a total of 2,510 MD/MS.
Participating institutions include the government, corporations, and the central government, as well as aided and recognised statewide medical colleges in the minor/private category.
Applicants are advised to use the official PDFs of the seat matrices available on the CET Cell website to make informed choices. The broad distribution can be summarised as:
The figures are renewed annually. Seats of every college are further subdivided (e.g., Institute Quota, EWS, orphans, PWD). The round-wise official seat matrix is the most reliable source of the precise counts and should be well researched before filling options.
Step-by-Step Maharashtra NEET PG Counselling Process
To navigate the Maharashtra NEET PG counselling, one needs to have a thorough idea of the centralised admission process. The process establishes an online profile and secures college choices with admission to the allotted institute.
The NEET PG Maharashtra Counselling has a Centralised Admission Process (CAP). The applicants will be required to go through several steps online. To maintain transparency, the authority releases provisional lists at each level.
Students should also keep their login details secure and double-check any data they submit, as the CET Cell usually does not accept correction requests once the forms have been submitted.
Online Registration: Visit the CET Cell portal and enter your NEET PG roll number, personal details, and then fill the application form with your academic, internship, and category details.
Fee Payment: Submit the non-refundable registration fee and a refundable security deposit online to confirm the applicant’s participation in the Maharashtra medical PG counselling process.
Document Upload: Scanned copies of academic, identification, and category certificates in the prescribed format should be uploaded for verification.
Common State Merit List (CSML): The merit list is published by the CET Cell, which is dependent on the NEET PG scores, domicile, and category. Only listed candidates can proceed further.
Choice Filling: When registering through the NEET PG Counselling Maharashtra portal, shortlist and bind the first- and second-preferred courses by ranking the preferred MD/MS or PG Diploma and college.
Seat Allotment: Allocation of seats is done automatically based on merit rank, preferences, reservations, and the seat matrix. The results are made available online.
Reporting & Verification: The allotted candidates are required to report to the college with their original documents and pay tuition fees to ensure admission.
Status Retention Form: All candidates who are content with their seat may fill out this form to complete the admission and avoid additional counselling rounds.
NEET PG Maharashtra Counselling: Document Verification and Reporting
The process of Maharashtra’s medical pg counselling relies on proper documentation. The section gives a comprehensive list of the required certificates and evidence that applicants will have to submit online and present in person at the stage of college reporting.
If you fail to report physically to present the original documents, it can cause instant cancellation of allocated seats during NEET PG Maharashtra Counselling. It is highly recommended that all candidates maintain several copies of attested photocopies of their files along with their original files.
Misspellings, dates or absent signatures of official certificates might lead to serious delays or disqualification. This typically includes:
Caste/Category certificate (if applicable) issued by the competent authority
Domicile certificate (when one applies under the Maharashtra quota)
Nationality certificate (if required)
No Objection Certificate (NOC) from the employer in case the candidate is in service.
Work experience certificate for in-service candidates.
Applicants are to have both the original and an attested copy of the photocopies. In the verification process, the college will verify the eligibility based on the NEET PG brochure rules.
Once they have been checked, the college decides that the admission is true and accepts the original documents (later to be returned according to the rules).
Maharashtra reserves 20% of the government state quota seats for in-service doctors in rural or tribal areas. These candidates will get incentive marks of merit and special preferential treatment in allotment.
Maharashtra reserves around 20% of state quota seats at the government colleges, which are reserved for the in-service doctors in government practice on rural or tribal postings. Such applicants are awarded incentive marks depending on their service, which enhances their merit standing.
In-service doctors with incentive marks are allotted seats first, according to policy, and the remaining seats are subsequently made available to those who do not have incentive marks. Every in-service applicant should satisfy the eligibility requirements of the NEET PG, and most commonly fulfils the Maharashtra domicile requirements.
In case a candidate quits government service after gaining admission, they might need to lose the seat and face penalties as per regulations.
Unfilled seats after the CAP rounds are filled by the online Stray Vacancy Round. The candidates are required to re-register and provide new preferences, where the allotment will be done based on merit. It is the last state counselling round; candidates who have passed AIQ/DNB are not eligible; however, in-service candidates can attend.
Any vacated seats remaining in colleges and courses after completion of the regular (CAP) rounds are again offered in the Stray Vacancy Round (also known as the special stray round). This is also done online by the CET Cell, Maharashtra.
The procedure is the same: the qualified candidates apply, complete new sets of preferences, and are allotted. Please remember that the stray round is the last option for gaining a state/allocated seat. Unless a candidate participates or secures a seat, they can apply to special rounds either through MCC or private management quotas.
In-service candidates could also participate in the stray round. The CET Cell clearly announces all reporting and status retention timelines. There are no more state counselling rounds that year, after the stray round allotment.
FAQs about Maharashtra NEET PG Counselling
Can NRI or OCI candidates participate?
Yes. Applicants of NRI/OCI may use the state counselling process to secure NRI seats in private colleges as long as the required NRI eligibility documents are provided.
What happens after seat allotment?
The candidates have to download the allotment letter, report to the assigned college within the stipulated deadline, undergo document verification, and pay the stipulated fees. Any failure to report results in the cancellation of the seat.
Is a Maharashtra domicile mandatory?
One must present a domicile certificate to claim a 50% of the State Quota seat unless the candidate has attained an MBBS degree in a recognised medical college in Maharashtra.
What is the Status Retention Form?
It is a statement made by candidates who are happy with their assigned seat. Submitting it confirms admission and eliminates them from subsequent counselling rounds.
Can I modify preferences in Round 2?
The rule of preference is based on the annual brochure. Generally, Round 1 decisions are forwarded, but new options can be introduced in case more seats are available.
Is the registration fee refundable?
No. The registration fee (around ₹3,000) is non-refundable. The security deposit is, however, refundable according to seat acceptance regulations.
What if I miss document verification?
Any failure to submit the original documents by the deadline will lead to automatic cancellation, and the seat will go to the next round.
How many seats are available?
It offers approximately 2,500 MD/MS seats (1,522 government and 988 private in 2025) with a certain number of diploma seats as well, allocating them to various categories of reservations.
Who is eligible to apply?
The applicants should have an MBBS degree awarded in a recognised college, a completed internship, an appropriate medical registration, and a valid NEET PG rank. Participation can only be among the Maharashtra merit list.
Is there a penalty for withdrawal?
Yes. Late withdrawal or halfway quitting may result in forfeiture of the security deposit and penalties up to ₹20 lakh according to the state bond rules.
Conclusion
The Maharashtra medical PG Counselling provides a clear-cut and merit-driven gateway to some of the most esteemed medical institutions nationwide. Applicants should make sure that they frequently check the official CET Cell portal for important updates about the seat matrix and merit lists.
Together with counselling awareness, proper academic preparation is crucial. For further guidance, DocTutorials can be your study partner. We offer crisp videos, clinical Qbank, exam-focused notes, flashcards, and mind maps, and much more. This helps aspirants gain complete clarity over complex medical concepts.
Join DocTutorials today and explore our NEET PG course to excel in your medical career!
Preparing for the NEET PG 2026 can be an overwhelming journey because of its vast syllabus and the pressure to…
Can I Take NEET PG Coaching from MBBS 1st Year?
NEET PG (National Eligibility cum Entrance Test for Postgraduate) is a national-level test that MBBS students must pass to secure admission to postgraduate medical programs in India, such as MD, MS, and PG Diploma programs.
Once the MBBS is completed, all students who wish to specialise in a specific field require an excellent NEET PG score. This article covers all the essential information for NEET PG preparation during the first year of MBBS. Keep reading to learn more.
Why is the MBBS 1st Year a Great Time to Begin Preparation?
You can start NEET PG coaching from the 1st year of MBBS. Early preparation, when done wisely, helps focus on understanding concepts rather than just memorising for exams, without the pressure of studying MBBS subjects.
You can start NEET PG coaching from the 1st year of MBBS. In fact, this can be very helpful if done properly. Starting early does not mean studying all the time or putting pressure on yourself.
It simply means that while studying your MBBS subjects, you also keep NEET PG in mind. You focus on understanding concepts clearly rather than memorising them solely for exams.Starting preparation early has several benefits, such as:
You build strong basics from the beginning.
You learn concepts slowly and clearly.
You get more time for revision.
You feel more confident later.
How to Prepare for NEET PG in the MBBS 1st Year?
In your first year of MBBS, focus primarily on your college studies, as subjects such as Anatomy, Physiology, and Biochemistry form the foundation for NEET PG. Use standard textbooks, set realistic goals, study for short periods consistently, take breaks, and maintain proper sleep.
Here are a few tips for NEET PG preparation in MBBS 1st Year:
Focus Mainly on MBBS Studies
The most important rule for a first-year student is to never ignore MBBS studies. Your college syllabus should always be your first priority. NEET PG preparation in the first year should go hand in hand with MBBS, not run counter to it. When you study Anatomy, Physiology, or Biochemistry properly for college, you are already preparing for NEET PG.
Use Standard Textbooks
The importance of standard MBBS textbooks is quite high during the first year. They elaborate on subject matter and help construct proper ideas. Here are the standard textbooks for the 1st year MBBS:
Lippincott Illustrated Reviews: Biochemistry (South Asian Edition)
Denise R. Ferrier; Ritu Singh, Rajeev Goyal
Biochemistry
Harper’s Illustrated Biochemistry
Kathleen Botham, Peter J. Kennelly, Owen McGuinness, P. Anthony Weil, Victor Rodwell
Physiology
Principles of Physiology
Debasis Pramanik
Physiology
Review of Physiology
Soumen Manna
Physiology
Crisp Complete Review of Integrated Systems Physiology
S. Krishna Kumar
Physiology
Guyton and Hall Textbook of Medical Physiology (South East Edition)
John E. Hall, Michael E. Hall; Mario Vaz, Anura Kurpad, Tony Raj
Physiology
Textbook of Physiology
A.K. Jain
Set Realistic Goals that Match Your Limits
Do not plan too much within a short period. Trying to study many subjects at once may soon burn you out. The set goals should be practical and achievable so you can study without stress.
Follow the SMART Goal Method
Make your goals specific, measurable, achievable, relevant, and time-bound (SMART). Clear goals bring direction to your study routine and prevent confusion. When you have the correct idea of what to study, it becomes easier and more manageable.
Take Regular and Purposeful Breaks
Regular and purposeful breaks are beneficial because they allow your brain to rest and be better positioned to remember. Constant studying with no breaks may decrease concentration. Breaks in between sessions make your brain fresh and enhance productivity.
Make Sleep a Non-Negotiable Habit
Sleep is essential for learning and memory. A well-rested mind understands and remembers better. Get enough sleep, 6-7 hours without interruption each day, and make it a part of your training.
Use Limited and Reliable Study Resources
Learn with limited and trusted study materials. Excessive use of books or other platforms results in confusion. A better understanding with fewer resources is always more useful.
Use Coaching Only for Concept Clarity
If you join NEET PG coaching in the first year, use it as a support tool, not a pressure point. Coaching is not about covering the syllabus; it should help you get a better grasp of the topics.
Start MCQ Practice Slowly
MCQs are important for NEET PG, but in the first year, they should be used carefully. Solve basic MCQs related to the subjects you are currently studying. The goal is to understand:
How questions are framed
How concepts are applied
Study Regularly but for Short Hours
The first year does not necessitate long study hours. Even one to two focused hours daily are enough. Learning a bit each day helps build discipline and reduce pressure. Regularity is more important than the number of hours of study.
Avoid Comparing Yourself With Others
Comparing your progress with friends can increase stress and self-doubt. Everyone has a different pace. Focus on your own growth and try to improve a little by little each day.
Communicate When You Feel Overwhelmed
If you feel stressed or exhausted, talk to someone you trust. Sharing your feelings with a friend, senior, or mentor can help reduce mental burden. Asking for help is a sign of strength.
Use College Resources Effectively
Medical colleges are also a rich source of resources that can assist with NEET PG preparation. One of the greatest strengths is the teachers. They will be able to answer tough questions and clarify your queries.
The college library is useful too. It provides access to standard textbooks, reference books, and journals. Group discussions can be beneficial too. It gives you the opportunity to observe different thinking patterns and makes learning easier.
Common Mistakes to Avoid During NEET PG Preparation
Many students make mistakes when starting NEET PG preparation early, which can lead to unnecessary stress. Common errors include studying without a plan, skipping revisions, ignoring past questions, avoiding MCQs or tests, preparing in isolation, and constantly comparing progress with others.
Many students make mistakes when they start NEET PG preparation early. Awareness of these errors can help you avoid a lot of stress. Some common mistakes include:
Studying without a clear plan or direction
Not revising topics regularly
Ignoring the previous year’s questions
Avoiding MCQ practice and grand tests
Preparing in isolation without peer or mentor support
Trying to study too many subjects at the same time
Neglecting college examinations
Using too many books and resources
Constantly comparing progress with friends or seniors
FAQs about Can I take the NEET PG coaching from an MBBS 1st year?
Is it too early to start NEET PG preparation in the MBBS 1st year?
No. If approached in a calm, structured way, with a strong focus on understanding basic concepts, early preparation can be helpful.
How many hours should a first-year student study for NEET PG? One to two focused hours daily, along with regular MBBS academic studies, are more than sufficient at this stage.
In the first year, should NEET PG coaching be the central focus?
No. The most important thing in the first year should always be core MBBS subjects and college academics.
Are MCQs important in the first year? Yes, but the focus should be on basic MCQs that help understand and apply concepts rather than on scoring.
Does starting early reduce stress later? Yes. Starting early helps build confidence gradually and significantly reduces pressure during the final preparation phase.
What are the common challenges faced during NEET PG preparation, and how can they be overcome? Common challenges during NEET PG preparation include difficulty in time management, stress, and inconsistency. These can be managed with a structured study plan, proper guidance, a healthy routine, and regular breaks.
Is clinical exposure important during NEET PG preparation? Yes, clinical exposure helps apply theory to practice, improves clinical reasoning, and enhances understanding of patient management. It further benefits both NEET PG preparation and future practice.
Can NEET PG preparation be started during MBBS? Yes, preparation can begin during MBBS. Starting early helps build strong concepts gradually and reduces pressure during internship.
Who all are eligible for NEET PG counselling? Candidates must qualify for NEET PG, hold a valid MBBS degree, have medical registration, complete internship on time, and meet domicile or category requirements if applicable.
How many rounds of NEET PG counselling will be conducted? NEET PG counselling includes four rounds under the All India Quota (AIQ): Round 1, Round 2, the AIQ Mop-up Round, and the AIQ Stray Vacancy Round.
Conclusion
Starting NEET PG preparation in the 1st year of MBBS is a smart decision. This is the right time to build strong basic concepts, develop consistent study habits, and begin light, stress-free preparation.
NEET PG preparation requires a strategic approach. Rely on trusted textbooks and MCQ resources, practice regularly with mocks to build speed and confidence, and maintain proper sleep and rest to manage stress.
For a systematic approach, DocTutorials provides clear videos, a clinical Qbank, exam-centred notes, flashcards, and mind maps that guarantee understanding of complex medical concepts.
Join DocTutorials today and start your NEET PG preparation journey the right way!
Achieving the dream of becoming a doctor is not easy. You need to be determined and have the right mindset…
What is the Best Time to Start NEET PG Preparation?
Enter Mobile Number
Enter your mobile number to access study materials
Enter valid phone number
📱 OTP via SMS
2QfAj5
Enter the code exactly as shown (case sensitive)
We'll send you a verification code
Verify OTP
OTP sent to
Complete Registration
Academic Details
🎓 Please provide your academic information
Processing...
No internet connection. Please check your network.
✓ Session Active
The NEET PG is one of the most competitive medical examinations for MBBS graduates and those seeking to transition to postgraduate specialist training. With 19 subjects in the syllabus, every medical student is left with one question: When should I start preparing for NEET PG?
This guide breaks down the NEET PG preparation timeline and proposes specific study plans to students at various phases of the medical career. Continue reading to know more!
Being too early in NEET PG preparation will cause burnout, whereas being too late will result in panic. Strategically, the third year of MBBS is the ideal starting point.
The NEET PG examination is a test of clinical skill and endurance. Many students mistake it for a sprint and exhaust themselves before the actual race starts. Others do not realise the depth of the syllabus (approximately 700 topics covering 19 subjects) and feel they are rushing in the last few months.
It is subjective, though statistically and strategically, toppers and educators have cited the third year of MBBS as the most effective starting point. The students have already gotten beyond the overload of anatomy and physiology and are not yet daunted by the oppressive clinical responsibilities of the internship.
Starting, however, is different at various stages. For a first-year student, it is about constructing concepts. As a post-intern, it involves tough MCQs. It is the initial step in a successful rank to understand this distinction.
Why is the MBBS Third Year Considered Ideal for NEET PG Preparation?
The MBBS third year is the golden period to start NEET PG preparation, as it is when subjects are manageable and clinical exposure is increasing.The reduced pressure during exams allows students to adopt a relaxed yet strategic approach that balances university requirements with competitive exam demands.
By beginning to prepare for NEET PG at this stage, students can combine preparation for university examinations with the requirements of competitive examinations. If you are a third-year student, now is the best time to start.
Here’s why the third year stands to be the golden phase:
Manageable Subjects: It has 3 major subjects, namely, ENT, Ophthalmology, and PSM (Community Medicine). These are scoring subjects. Learning them guarantees a significant portion of the marks.
Clinical Exposure: Students begin to attend postings. This is the ideal moment to correlate what they observe at the wards with what they read in the preparation notes.
No Exam Pressure: In contrast to the last year, when the tension of the professional tests can be immense, there is an easier, absorption-oriented course of study in the third year.
1. Phase 1 (Months 1-4): Finish 3rd Year Subjects
Devote the time to ENT, Ophthalmology, and PSM.
Resource: Take short video lectures and make your own notes.
Goal: By the time you reach your university exams, you should be in a position to answer MCQs that are of NEET PG level in these three subjects without straining.
One must have forgotten much about Anatomy and Biochemistry. It is high time to go over them with Rapid Revision modules or QRP (Quick Revision Programs).
Do not go through the whole textbook again. Review concepts using notes and videos.
3. Phase 3 (Months 9-12): Touch Base with Final Year Subjects
Start with Medicine or Surgery. Although it may not be complete, a glimpse into the systems (e.g., CVS, CNS) will make the final year much smoother.
Subject-Wise Strategy for Third Year
Subject
Weightage
Strategy
PSM
High
Frequently overlooked but high-ranking. Focus on Epidemiology and Biostatistics.
ENT
Moderate
Visual-heavy. Focus on diagrams and instruments.
Ophthalmology
Moderate
Clinical images are key. Study diseases like Cataract, Glaucoma, and Diabetic Retinopathy in depth.
How to Prepare for NEET PG during the Final Year?
Final-year NEET PG preparation demands integrating university learning with exam strategy, focusing on major subjects. Both concepts and clinical skills will be strengthened through smart study, MCQ practice, and the use of standard textbooks.
The last year is also referred to as a marathon on sprint speed. The big four: Medicine, Surgery, OBGYN, and Paediatrics. They are the foundation of the NEET PG Examination (they constitute about 50-60 per cent of the examination, comprising 10 subjects and their corresponding basics).
A common mistake that final-year students make is treating university preparation and NEET PG preparation as separate entities, which is incorrect. Here’s what you can do instead:
Read for the Ward, not just the Book: When you are on Surgery, read about the topic concerning the case you observed. Provided that you have a Hernia case, learn the anatomy of the inguinal canal, the categories of repairs, and the complications. This covers Anatomy, Surgery, and clinical skills simultaneously.
The Retrograde Method: Rather than picking up a chapter and reading it from beginning to end, what you can do is to answer 10 MCQs on the topic. You will probably make mistakes, but it will also train your brain to search for certain answers as you go through the text.
Standard Books are Key: For Medicine (Harrison’s/Davidson’s) and Surgery (Bailey & Love), use regular textbooks on essential subjects. On less important topics, use coaching notes.
Time Management in the Final Year
Weekdays: Pay attention to the topic of your current clinical posting.
Weekends: Saturday is dedicated to revising a short subject (e.g. Dermatology, Radiology) and Sunday to a Subject-Wise Test.
Grand Tests (GTs): Start taking GTs once a month. There is no cause to be worried about that score; you must be concerned about your stamina in sitting for 3.5 hours.
How to do NEET PG Preparation During MBBS Internship?
The preparation for the NEET PG internship is not easy, but it can be done with smart tips.Change focus parameters on thorough reading, Qbank training, and flaky topic modification.Make the most out of limited study hours using early morning, short breaks, and duty-based learning.
One must not panic while starting the preparation during an internship. A high percentage of toppers begin their serious preparation during their internship. However, the strategy should not be comprehensive reading but high-yield targeting.
The students will be subjected to 12-hour shifts, night shifts, and the fatigue that accompanies them. They cannot study for 10 hours a day, but might get 3-4 hours on a comparatively light day.
The Qbank is your Best Friend: Even when there is no time to watch a 2-hour video lecture, they can always find time to answer 10 MCQs on an app when it’s time to report to a patient or take a lunch break.
Focus on Memory-based Subjects: Other subjects, such as Biochemistry and Microbiology, are memory-based. Have flashcards or online notes on a mobile phone at all times to review them constantly.
Duty-Based Learning:
Casualty Posting: Learn Management of Trauma, MI, and Poisoning (Forensic Medicine).
Labour Room: Master Partograms, stages of labour, and obstetric emergencies (OBGYN).
Paediatrics Ward: Learn developmental milestones and immunisation schedules.
Time Management During Internship
Early Morning (5 AM – 7 AM): 2 hours of intense study before duty. This can potentially be the golden time if utilised efficiently.
During Duty: Solve 20-30 MCQs on your phone.
Evening (Post-Duty): You will be tired. Do not try to read heavy theory. Watch a clinical case video or review the MCQs you got wrong during the day.
What are the Recommended Study Resources for NEET PG Preparation?
MBBS textbooks are known to offer a good conceptual base, and short review guides and notes enable fast revision.Question banks and mock tests enhance the accuracy of the exams as they familiarise the students with the pattern and timing.
Standard MBBS textbooks are used to develop the basic knowledge, whereas brief review books are utilised in revision. Mock tests and question banks are used to assist the students with the exam patterns and to develop more accuracy.
Online resources and interactive techniques to assist in the exam-oriented practice and concept reinforcement.
Practice question banks and mock tests to simulate the exam pattern.
Short notes and quick revision guides will be essential during the last few months.
A combination of these in a balanced manner will guarantee strong fundamentals and examination-oriented knowledge. However, it is better to limit resources and revise them several times than to have multifarious sources in a superficial way.
FAQs about What is the Best Time to Start NEET PG Preparation
How much time is required for NEET PG preparation?
On average, 12-18 months of regular study is estimated to be adequate. This involves concept construction, numerous revisions, and frequent mock test practice.
What is the strategic window for maximum success?
The best period would be between the second year of MBBS and the final year, with intense exam-oriented study in the final year and internship. This equilibrium guarantees both the depth of knowledge and the exam preparation.
Should I focus more on clinical or pre-clinical subjects?
Clinical subjects carry more weightage in NEET PG, but both are important. Pre-clinical subjects are to be revised for the basics, whereas clinical subjects require more in-depth attention and practice.
What role do mock tests play in preparation?
The mock tests play a critical role in time management, locating weak points, and exam temperament. Consistent practice will create the simulation of the actual exam setting and increase confidence.
Does starting early guarantee success?
Early learners have a higher chance of revision and better understanding, but it takes a lot of consistent work, clever planning, and practice in exams compared to those who start late, so time alone is not the guarantee.
Does NEET PG preparation follow a different approach in each year of MBBS?
Yes. The preparation plan varies from year to year in MBBS. Early years are best used for building strong concepts, middle years for systematic subject-wise coverage, and final year or internship for revision and clinical integration.
Is it advisable to start NEET PG preparation when clinical subjects are first introduced?
Yes. The introduction of clinical subjects is an ideal phase to begin light, structured NEET PG preparation, as linking theory with clinical practice improves understanding and long-term retention.
How does an early start in NEET PG preparation make an internship more productive?
Early starters tend to join internships with most subjects already undergone once. This will enable use of the internship time to revise, do MCQs, and practice on tests, as opposed to new content under time pressure.
When should I completely stop studying new topics and focus only on revision?
Learning new topics should be cut off approximately 45-60 days prior to the exam. At this stage, the introduction of new content is unhelpful since unrevised material will hardly be retained or remembered during the examination.
How does preparation for university exams support NEET PG preparation?
University examinations foster descriptive knowledge and depth of concepts, whereas NEET PG tests require application and problem-solving. Early NEET PG preparation will allow students to overcome this gap progressively rather than experiencing a high transition at a later date.
Conclusion
The NEET PG exam preparation calls for consistency rather than intensity. over intensity. A student who studies 4 hours a day for 2 years will almost always beat a student who studies 12 hours a day for 2 months.
At DocTutorials, we provide edition notes, clinical QBanks, mindmaps, and flashcards to help you stay well-prepared through efficient studying. Join DocTutorials today and explore our NEET PG course to excel in your medical career!
If you want to prepare for NEET PG 2025, it is important to know about choice-filling in the same way as it is important to perform well in the test. The wide range of PG courses offered by various medical institutions makes it essential to understand the NEET PG choice-filling approach and process. This approach aids in planning more effectively and enhances the chances of seat allotment.
The process includes candidates selecting preferences based on the options made available by the Medical Counselling Committee (MCC), covering All India Quota (AIQ), state quotas, etc., and specifying deadlines for submission and locking.
Read below for detailed information on NEET PG choice locking, timelines, strategies, and key considerations before counselling progresses!
Importance of Choice Filling in NEET PG Counselling
The NEET PG counselling is conducted to fill the candidates’ choices, who list their preferences for colleges and courses. The choice locks the seat allotment, while if missed, it excludes the candidate from the allotment process outright. A well-selected list will maintain a balance between chances and one’s dreams, with very realistic and safe categories of choices across all rounds of counselling.
The choice filling for NEET PG is a critical juncture when candidates choose colleges and courses according to their priorities after registering and completing document verification. This process will determine seat allotment based on rank and category, along with preferences submitted online through the MCC portal. Missing the window or not locking choices would exclude a candidate from allotment, as unprocessed preferences may not be considered.
The phase of NEET PG counselling choice filling allows aspirants to add, remove, or rearrange choices without any limit on quantity, thus balancing aspirations with reality. Statutory advisories state that this should be done well in advance of the seat matrix review so that the application aligns with previous cutoffs vis-à-vis availability. A well-executed choice here will matter not just in the first round but also in mop-up and stray vacancy rounds.
Ace Your NEET PG Prep With DocTutorials NEET PG Online Live Power Pack
The enactment of the Round 1 and Round 2 dates of choice filling by MCC underscores the importance of exercising due diligence by tracking official websites for daily updates. Round 1 choice filling and locking was extended till November 20, 2025. Round 2 choice filling continued from 06 Dec 2025 to 14 Dec 2025, and Round 2 counselling results were declared on 16 Dec 2025.
The Medical Counselling Committee for NEET PG 2025 rescheduled these timelines several times to favour the candidates. Round 1 choice filling ended earlier, with deadlines up to November 20 for the Initial Submission, while Round 2 choice filling opened online from December 6, 2025. Soon after, the seat allotment results for Round 2 were released, while PwD certificate generation remained active until December 9, 2025, at 4:00 PM.
Processes at the state level, such as those in Madhya Pradesh via DME portals, follow a similar path to MCC but cater to only their state quotas. Updated news on ongoing events must be monitored on mcc.nic.in, as the dates are strict and cannot be extended beyond the announcement. Choice locking will be compulsory after the close of each round to finalise picks.
Counselling Round
Key Activity
Dates (latest)
Round 1
Choice filling and locking
Extended to Nov 20, 2025
Round 2
Choice filling start and end date
06 Dec 2025 – 14 Dec 2025
NEET PG 2025 round-2 counselling result
Round 2 counselling results declared
16 Dec 2025
PwD Portal
Certificate generation
Up to Dec 9, 2025, 4 PM
Seat Allotment
Round 2 results upload
Post choice locking
Step-by-Step Guide to NEET PG Choice Filling
The complete process of NEET PG choice filling involves logging in, creating options, rearranging, and securing choices on MCC or the state portal. It focuses on the need to ensure that every choice is scrutinised very carefully, and it’s very important to download the confirmation slip. The warning goes: once the choice is locked, it cannot be undone.
This portal is located at mcc.nic.in, where login begins with entering the NEET PG 2025 roll number, password, and captcha for signing in. Navigate to the “Choice Filling” option under the candidate corner for the concerned round. Go through each instruction regarding college preferences before proceeding.
Here is an overview of the steps involved:
Log in to mcc.nic.in or the state portal using your credentials.
Click the choice-filling link and select the round (e.g., Round 2).
Add colleges/courses using “+”, rearrange by dragging.
Review the list and save changes if needed.
Lock in your choices before the deadline, and download the confirmation.
NEET PG choice locking becomes non-reversible; any post-locking changes will then require going through either new rounds or special permissions. Printing or saving the confirmation page is applicable while reporting to the allotted colleges.
Strategies for Effective NEET PG Choice Locking
Consider using the Top-Mid-Safe strategy for NEET PG choice filling: Dream Colleges or Top Choices (10–20%), Moderate Choices (40–50%), and Safe Choices (30–40%). Avoid dummy choices, choosing based on the seat matrix, and optimising through reordering can help improve chances to secure a better seat.
The ideal strategy for NEET PG choice filling is top-mid-safe:
Dream Colleges or Top Choices (10–20%): Consists of highly preferred institutions or specialisations. May be difficult to secure.
Moderate Choices (40–50%): Fall within a realistic range. Includes colleges and courses matching your rank trends.
Safe Choices (30–40%): Institutions where there is a very high chance of securing seats.
Speciality-wise, state-wise availability and career scope, among other things, will be analysed, keeping individual interests and super-speciality prospects in mind. Avoid dummy choices—quality over quantity maximises the allotment odds.
Track real-time trends to further fine-tune lists across rounds. Rearrangements should be done frequently based on the new data emerging before the locking process. Common pitfalls include poor ordering (such as placing safe choices above dreams) or ignoring conflicts between branches/colleges.
Here is an overview of the top NEET PG choice-filling strategies:
Strategy Type
Description
Benefits
Top-Mid-Safe
Dream > Realistic > Secure seats
Balances risk
Seat Matrix Use
Check speciality/state cutoffs
Data-driven decisions
No Dummies
Meaningful preferences only
Avoids wasted slots
Reordering
Drag-drop priority
Optimises allotment chances
NEET PG Seat Matrix Insights for Choice Filling
The Medical Counselling Committee (MCC) handles the counselling process for 50% seats under the All India Quota (AIQ), including government colleges, deemed universities, and ESIC/AFMS institutes. The remaining 50% and 100% of private colleges are handled by the respective state authorities.
The NEET PG seat matrix contains information on the total number of seats – PG, quota elements, and specialities – whose allotment will decide the NEET PG choices. AIQ constitutes 50% of the seats in all government colleges, whereas the remaining are assigned to deemed, private, or DNB seats, except for what is dealt with under state quotas. Use the specialities released by MCC before recording a preference list.
Illustration showing this very simple example of seat distribution:
Type of Institution
Total Seats
AIQ Seats (50%)
State Quota Seats (50%)
Private & Deemed
Govt Colleges
12,000
6,000
6,000
0
Deemed Universities
2,000
–
–
2,000
Private Colleges
3,000
–
–
3,000
DNB Seats
1,500
Included in AIQ
Included in the State
Included
This matrix helps candidates target colleges according to quotas and reservation categories.
Note: Figures may vary.
Document Verification and Reporting for NEET PG Counselling
Students who have been allotted seats in NEET PG counselling are required to produce several documents, such as an internship certificate, a rank letter, registration certificates, and an ID. Failure to show these documents may result in a loss of seat.
The documents that students must submit when reporting to colleges after being allotted in NEET PG counselling are as follows:
Required Document
Importance
Notes
Internship Certificate
Proof of internship completion
Must be completed before joining
NEET PG Rank Letter
Confirm rank and eligibility
Original or physical copy
Provisional/Permanent NMC/SMC
Medical Council Registration
Must be presented to join
Category Certificate
For the reservation claim
SC/ST/OBC/EWS certificates
ID Proof
Identity verification
Aadhaar, PAN, Passport, etc.
Disability Certificate (PwD)
Proof of disability
Needs to be issued via MCC-authorised centres
MCC Allotment Letter
Proof of seat allotment
Needs to be downloaded after seat allotment
MBBS Mark Sheets
Additional verification of eligibility
Must be submitted for all years
MBBS Degree Certificate
Additional verification of eligibility
Original + photocopies
Proof of Fee Payment
Payment confirmation
Allotment + Tuition fee receipts
Note: Institutes may request additional documentation.
Mistakes to Avoid in NEET PG Choice Filling and Locking
Not locking in seats before deadlines, having too many dummy choices, not analysing the seat matrix, not rearranging the preferences after each round, and submitting incomplete documentation are some of the major mistakes to avoid in NEET PG choice filling.
Listed below are the common mistakes you must avoid during NEET PG choice filling:
Failure to lock the choices before the deadline, resulting in no seat allocation.
Dummy choices or irrelevant positions in the list to fill it, making you miss potential seats in better institutions.
Failure to analyse the seat matrix, leading to selections that are unrealistic or impractical.
Not rearranging preferences even as data changes with each counselling round.
Missing or incomplete documentation, resulting in forfeiture of seats.
Essentially, the timing and precision during these stages go a long way toward determining the results of the counselling.
Post NEET PG Choice Filling: What Comes Next?
Candidates must keep track of their preferred seats to check whether they have been locked. If yes, they must decide whether they wish to go forward with the allocation or wait for upgrades in further rounds. They must keep themselves informed about the formalities and payments required to join.
After the candidates lock in their choice and are allotted seats, they will receive allotment letters and must decide whether to accept the seat or take part in further rounds, if available. In mop-up rounds or stray vacancy counselling, the chances of upgradation arise again. Always keep checking official portals for notifications.
The admission procedure, joining, and tuition payment will be the final preparatory steps following the rounds of the choice filling. It is necessary to have backup options on standby should the allotment not be successful, and to consider why state or institutional counselling, if an option, should be explored.
FAQs about NEET PG 2025 Choice Filling
What is the choice filling in NEET PG?
It is the online process by which a candidate selects and orders their preferred medical colleges or specialities for counselling allotment. This process shall govern allotment chances.
Has choice filling started for NEET PG 2025?
Round 1 choice filling was completed and locked by November 20, 2025. Round 2 continued from 6 Dec 2025 to 14 Dec 2025, and the counselling results were declared on 16 Dec 2025.
Is a rank of 7000 good in NEET PG?
A rank slightly above 7000 would generally ensure good round 2 or mop-up seats in government and private colleges, but it relies largely on category and speciality choices. One should be pragmatic in expectations.
How many choices should I fill in for NEET PG counselling?
Candidates may fill out an unlimited number of choices online, but a reasonable number of prioritised choices (about 50-100) should be filed, based on the seat matrix and personal inclination. Fill in 50-100 meaningful, prioritised options to boost chances of future allotment.
Why is the choice filling important for NEET PG?
Choice filling is a critical stage because it involves selecting and prioritising the colleges and courses that are preferred. This list directly influences which seat is allotted, depending on rank and seat availability. A smart choice filling strategy can boost the chances of getting a preferred college, avoid unsuitable options, and reduce the need for unwanted upgrades or exits later.
Is it possible to change my choices after locking them in NEET PG counselling?
No, once the choices are locked, they cannot be modified. If the choices are not locked before the deadline, the system automatically locks the last saved preferences.
What happens if a candidate skips Round 1 of NEET PG counselling?
A candidate can still participate in Round 2, the Mop Up Round, or the Stray Vacancy Round. However, skipping Round 1 may limit the chances of getting preferred seats. Taking part right from the first round offers the widest range of options.
Which documents are needed while filling choices for NEET PG?
During the choice filling stage, only the NEET PG login credentials are required. However, at the time of admission, documents such as the admit card, scorecard, MBBS degree or provisional certificate, internship completion certificate, registration proof, valid ID proof, and category certificate (if applicable) are needed.
Is the security deposit refunded during NEET PG counselling?
Yes, the security deposit is refunded if a candidate does not accept any seat or after completing the admission process. However, it may be forfeited in certain situations, such as failing to join the allotted college within the specified time.
What is the purpose of the NEET PG security deposit in the choice filling process?
The security deposit serves as a commitment from the candidate. It is returned if no seat is allotted or if the candidate exits the counselling process in line with the prescribed rules and timelines.
Conclusion
Understanding NEET PG counselling choice filling is crucial for candidates willing to secure a seat for their future medical careers. Regularly monitoring the MCC portal for updates, seat matrix study, rearranging preferences after each round, and keeping realistic expectations is crucial for a favourable outcome.
Meanwhile, rely on DocTutorials to ace your NEET PG exams with our concise high-yield notes, question banks, mock tests, expert guidance, and more. Check out our NEET PG course today!